Will Breast Reduction Surgery Affect My Ability to Breastfeed? Expert Insights on Lactation and Reduction Mammaplasty
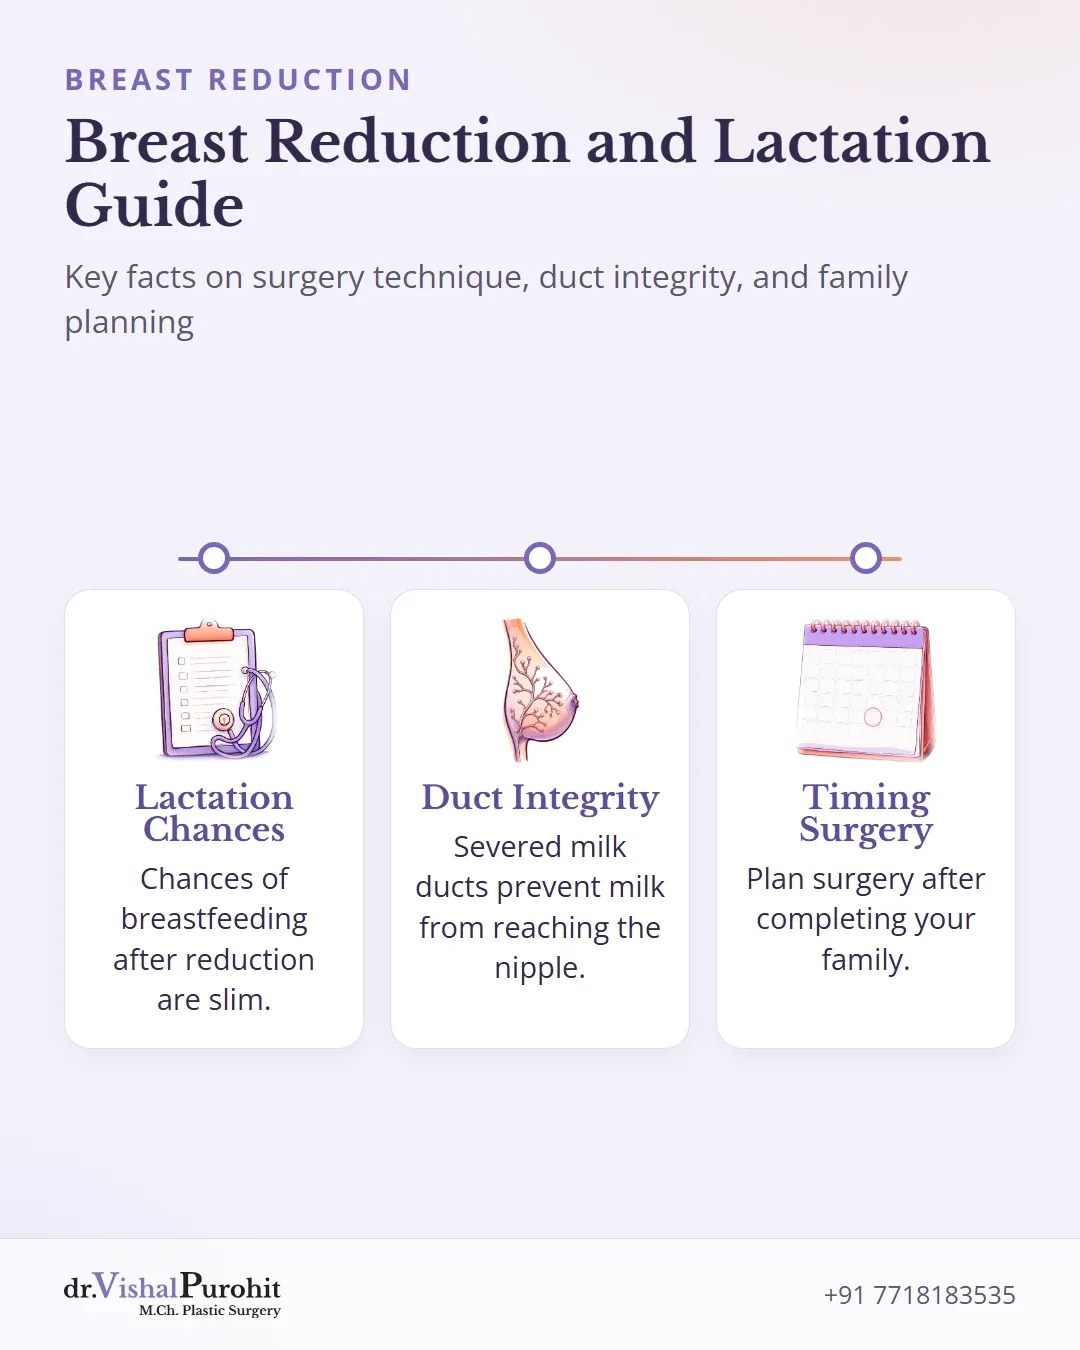
Can you still breastfeed after a breast reduction? It mostly depends on the surgery technique and how the nipple is moved.
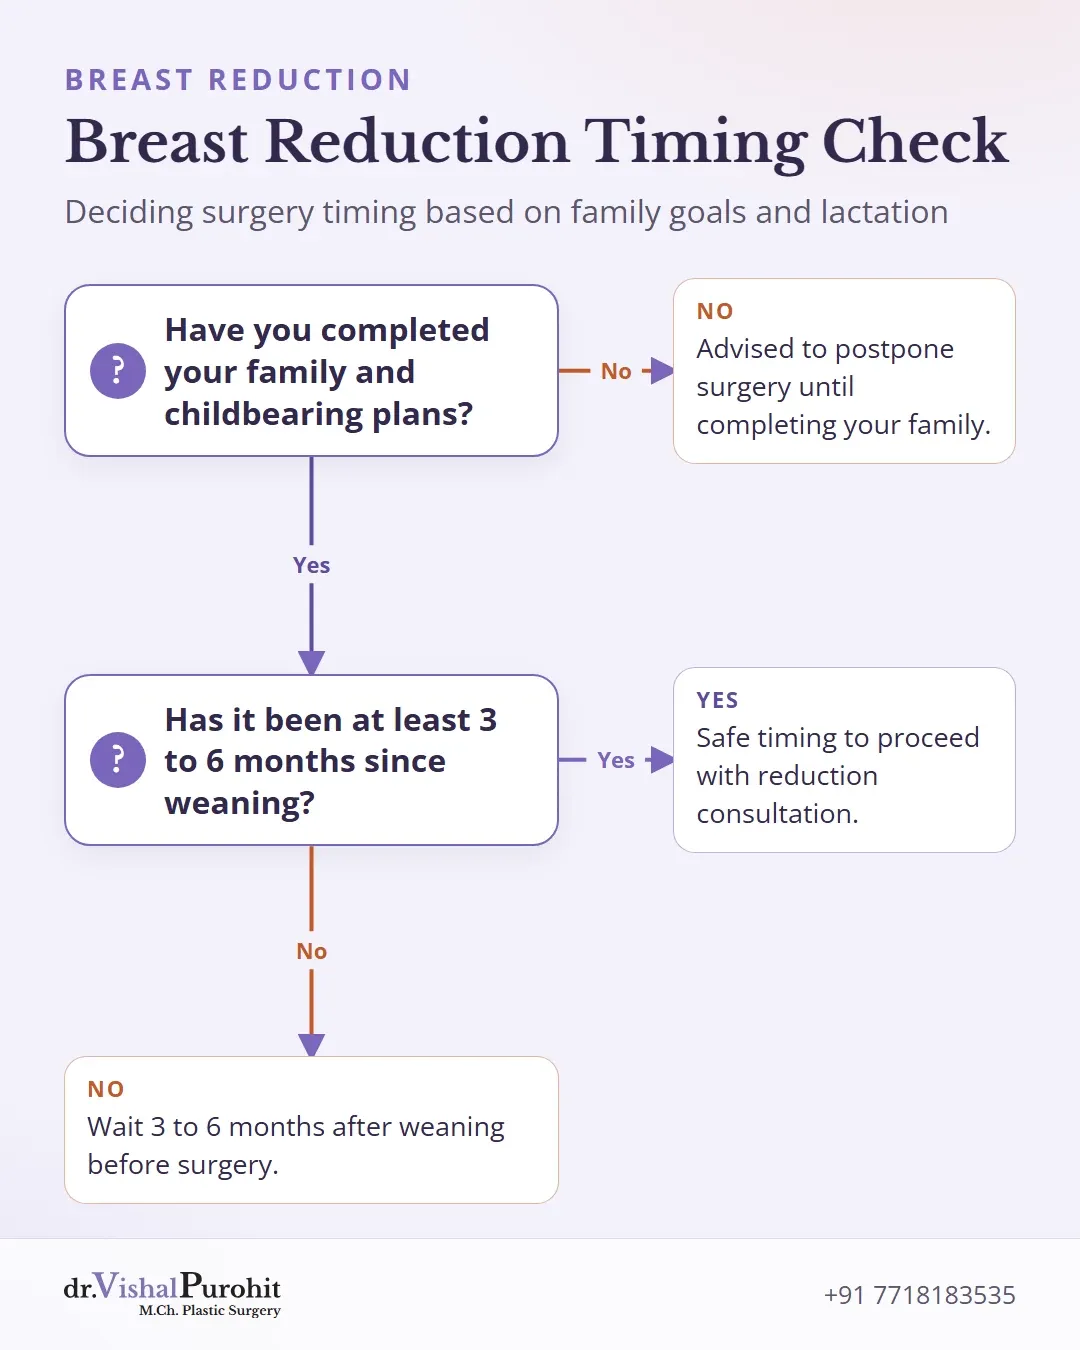
Dr. Purohit's note: In his practice, the chances of breastfeeding after breast reduction surgery are slim, and he advises having the surgery after completing your family.
Removing breast tissue can lower your milk supply or make breastfeeding harder.
Your surgeon must be careful to protect your breast structure. An M.Ch. plastic surgeon knows how to handle this.
Techniques are planned to protect the tissue and nerve supply as much as possible, though breastfeeding cannot be assured.
For women considering breast reduction in Jaipur, these surgical details are very important. They ensure your results support both your confidence and your future goals.
Every person is different. Your surgical plan should be made just for you.
The goal is to improve your life and confidence, helping you achieve a comfortable shape that fits your personal goals.
The Role of Milk Duct Integrity in Lactation
Your body uses the mammary gland to make milk. This gland has small sacs that produce milk and tubes that carry it to your nipple. This whole process is called lactation.
Breastfeeding is more likely when you have milk duct integrity. This means your tubes must stay open and connected. If a surgeon creates severed ducts, the milk cannot reach your baby.
Your ability to nurse depends on keeping the breast lobules, ducts and the tissue near the nipple intact1. Cutting these paths can limit your milk flow. In Dr. Vishal Purohit’s practice in Jaipur, he advises surgery after completing the family.
Nipple-Areola Complex (NAC) Positioning and Its Impact on Milk Flow
The Nipple-Areola Complex is your nipple and the dark circle around it. It must stay connected to your milk glands.
Key points
- The nipple-areola complex must remain connected to milk glands during repositioning.
- Moving the nipple too far can disrupt underlying milk pathways.
- Surgeons carefully plan placement to preserve tissue connections and appearance.
During reconstructive surgery, your surgeon might move your nipple higher. This involves careful nipple repositioning to protect underlying tissue.
How far they move it matters. If it moves too far, the connection to the glands can break.
Good NAC positioning creates a natural look, but careful planning is still needed to preserve whatever milk pathways remain intact.
Surgeons plan this move very carefully. In Dr. Purohit’s practice, the new nipple position is placed about 19 to 22 cm from the sternal notch, and the areola is resized to about 38 to 42 mm in diameter.
One described marking approach in the literature places “the new nipple position” about “1.5-1.75 cm below the most projected area of the breast after final shaping” — a technique-specific marking rule, not a universal standard.
Your surgeon will individualize this to your anatomy and chosen pedicle. Dr. Purohit’s preferred pedicle is the superomedial pedicle, though the inferior pedicle is also used.
Comparing Surgical Techniques for Breastfeeding Preservation
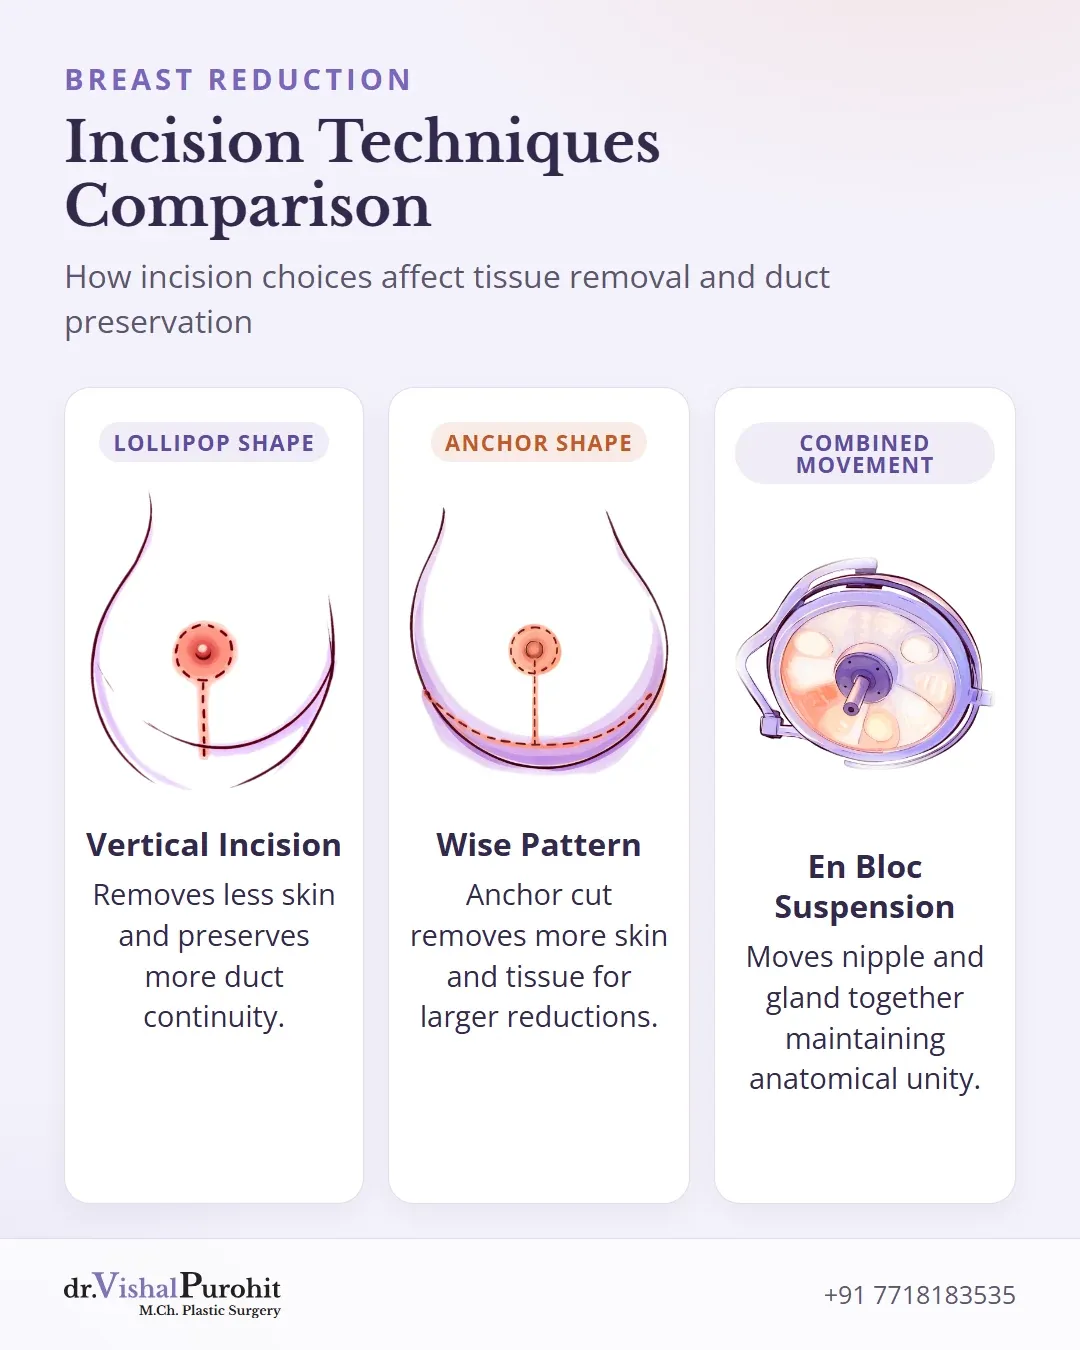
Your surgeon picks a breast reduction method based on your body and goals. This Surgical Technique Selection changes how they handle your milk ducts. In Dr. Vishal Purohit’s practice in Jaipur, surgery is advised after completing your family.
Some incision types focus on shape. Others focus on keeping the nipple connected to the gland.
The table below compares common methods and how they affect nursing:
| Surgical Technique | Description | Impact on Breastfeeding |
|---|---|---|
| Vertical incision | A “lollipop” shape cut that removes less skin. | Often described as offering “better projection and upper pole fullness” (“better projection and upper pole fullness”) while preserving more duct continuity in selected cases. |
| Wise pattern | An anchor-shaped incision that removes more skin. | A standard approach for larger reductions; comparative scarring and projection outcomes vary by study and technique (“better scarring along with better projection” has been reported for vertical patterns in some series — discuss tradeoffs at consultation). |
| En bloc suspension | A technique that moves the nipple and gland together. | This works well because it “maintains the unity of the nipple-areola and mammary gland” En bloc suspension2. |
Vertical (Lollipop) Incision Technique
The vertical incision is an option if you want a natural look and smaller scars. The surgeon makes a cut around the nipple and one line moving down.
This method removes less skin than other types of surgery. While some techniques aim to minimise duct disruption, Dr. Vishal Purohit advises having the procedure after completing your family.
Some surgeons use a superior dermoglandular flap3 to move the nipple. This keeps the nipple connected to the breast tissue.
The pedicled transposition keeps the nipple attached and is designed to preserve blood flow and the 4th lateral intercostal nerve branch for sensation.
Inverted-T (Wise Pattern) Technique
The Wise pattern is a common choice for a significant reduction. It uses an anchor-shaped cut. This cut wraps around the nipple and goes down the breast.
This method removes more skin and tissue than a lollipop incision. It lets your surgeon reshape the breast more fully.
This process may move the nipple further from its original spot. This can cause more duct disruption, which means the milk paths are cut. In Dr. Vishal Purohit’s practice in Jaipur, he advises surgery after completing the family.
Some surgeons use a Rotation of the Wise or vertical pattern (“Rotation of the Wise or vertical pattern”) to remove extra areola skin. This helps create a balanced look and manages the internal tissue.
Post-Surgical Lactation Success Rates and Expectations
Can you breastfeed after surgery? It depends on the method used and how much tissue is removed. In Dr. Vishal Purohit’s practice, he advises undergoing the procedure after completing the family, especially when considering how long breast reduction results last alongside future bodily changes.
Here is what you should know about the functional outcome and your goals:
Older Numbers
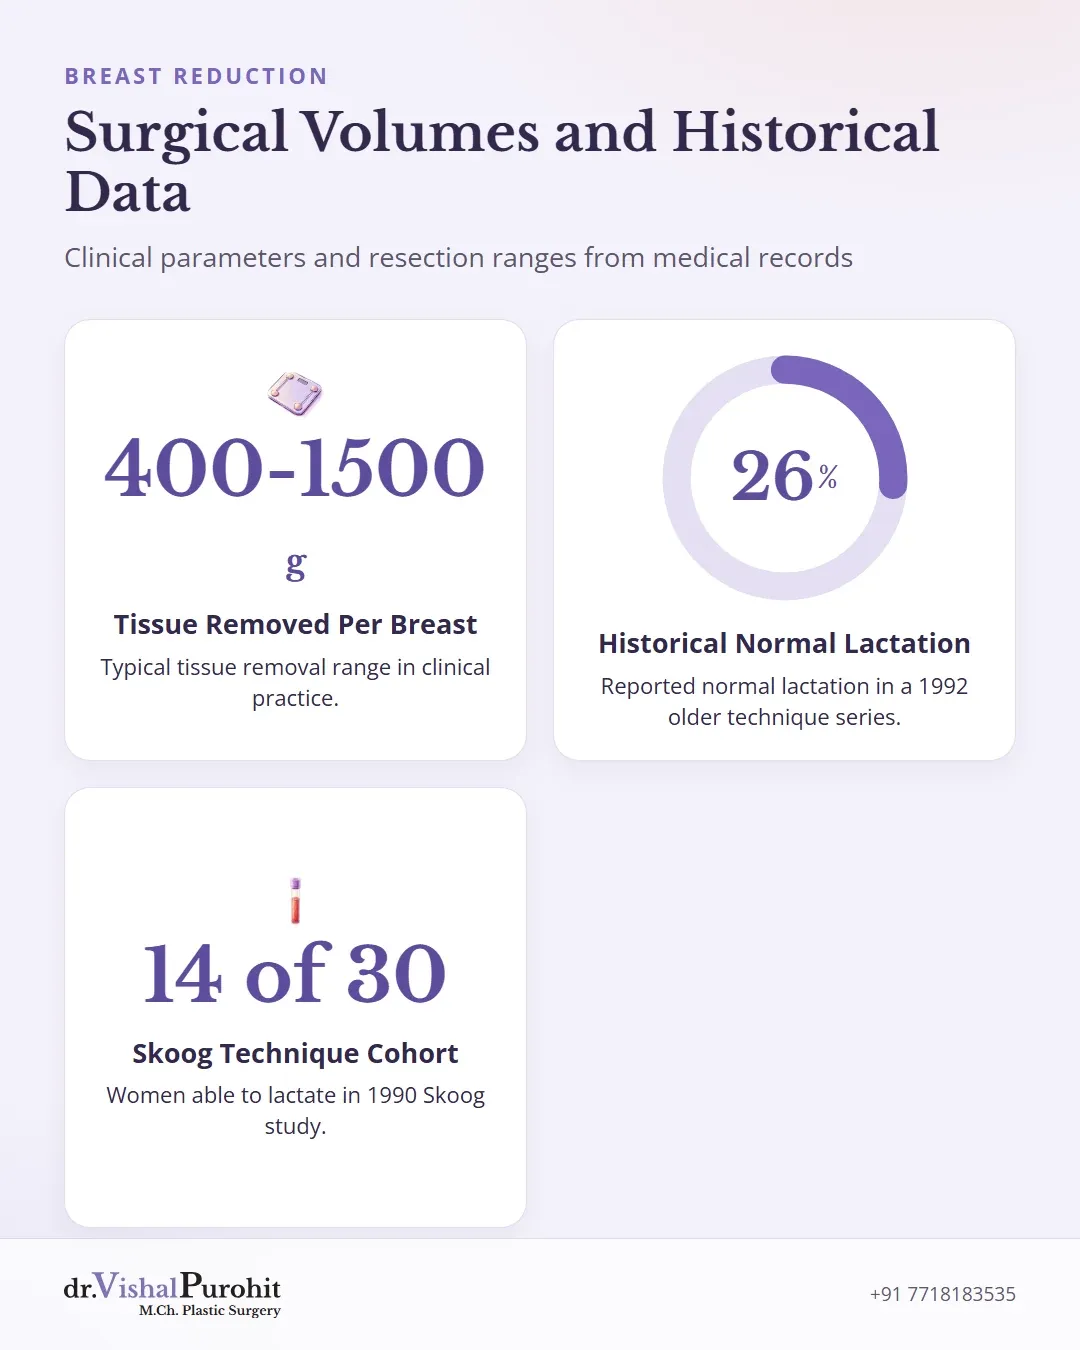
The 26% normal lactation4 figure comes from a 1992 series using older pedicle techniques, and the 14 of 30 who could lactate5 comes from a 1990 Skoog-technique series. They show that technique matters — they are not modern overall success rates.
Modern Techniques
Pedicle-preserving methods used today report higher success in selected patients, but lactation cannot be promised. Discuss future pregnancy plans before surgery.
Tissue Removal
Larger resections (one older series noted reduced lactation with reductions of over 500 grams) were associated with lower success ("lactation was regularly decreased in those patients who had a large reduction"). Thresholds vary by technique and era, so treat 500 g as a historical signal, not a cutoff. Typically, 400 to 1,500 grams are removed per breast in Dr. Purohit's practice.
Preserving the nerve pathways that trigger milk letdown closely mirrors the healing of nipple sensation after breast reduction.
Frequently Asked Questions
Will breast reduction surgery affect my ability to breastfeed in the future?
Under Dr. Vishal Purohit’s practice in Jaipur, patients are advised that because the chances of breastfeeding afterwards are slim, he recommends undergoing breast reduction after a woman has completed her family. While pedicled techniques keep the nipple attached and are designed to preserve sensation, prospective patients should not rely on preserving functional lactation.
Which surgical pedicle technique better protects future milk production?
The superomedial pedicle is Dr. Vishal Purohit’s preferred pedicle, though the inferior pedicle is also used. While pedicle-based techniques keep the nipple attached to an underlying tissue column, Dr. Purohit notes that functional lactation remains unlikely regardless of the pedicle chosen. In contrast, free nipple grafting, which is offered for very large breasts, completely eliminates any possibility of lactation. For women desiring future children, Dr. Purohit advises completing their family before undergoing reduction mammaplasty.
Can milk production decrease after breast reduction surgery?
Glandular tissue and milk ducts are altered or excised during the procedure. Dr. Vishal Purohit counsels patients during pre-operative consultations that surgery is advised after completing their family, rather than expecting to rely on functional lactation or supplemental nursing.
How long should I wait after breastfeeding before having breast reduction surgery?
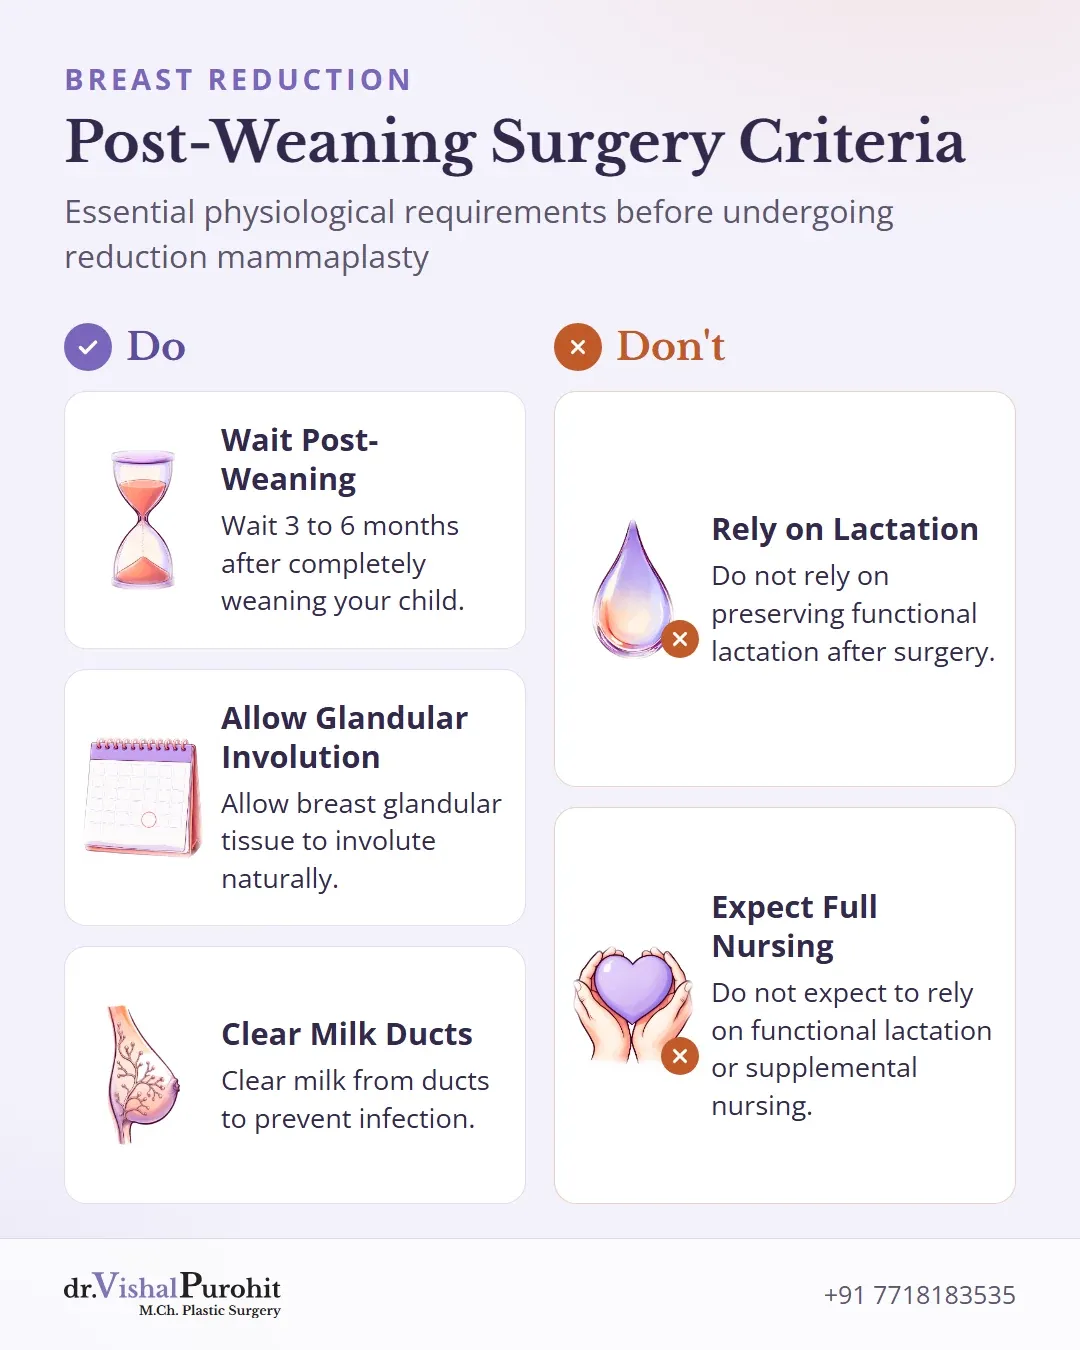
Women should wait at least 3 to 6 months after completely weaning their child before undergoing breast reduction surgery with Dr. Vishal Purohit in Jaipur. This waiting period allows breast glandular tissue to involute naturally, stabilizes prolactin hormone levels, and clears milk from ducts to prevent infection. As an M.Ch. plastic surgeon, Dr. Purohit ensures safe, sterile surgical conditions.