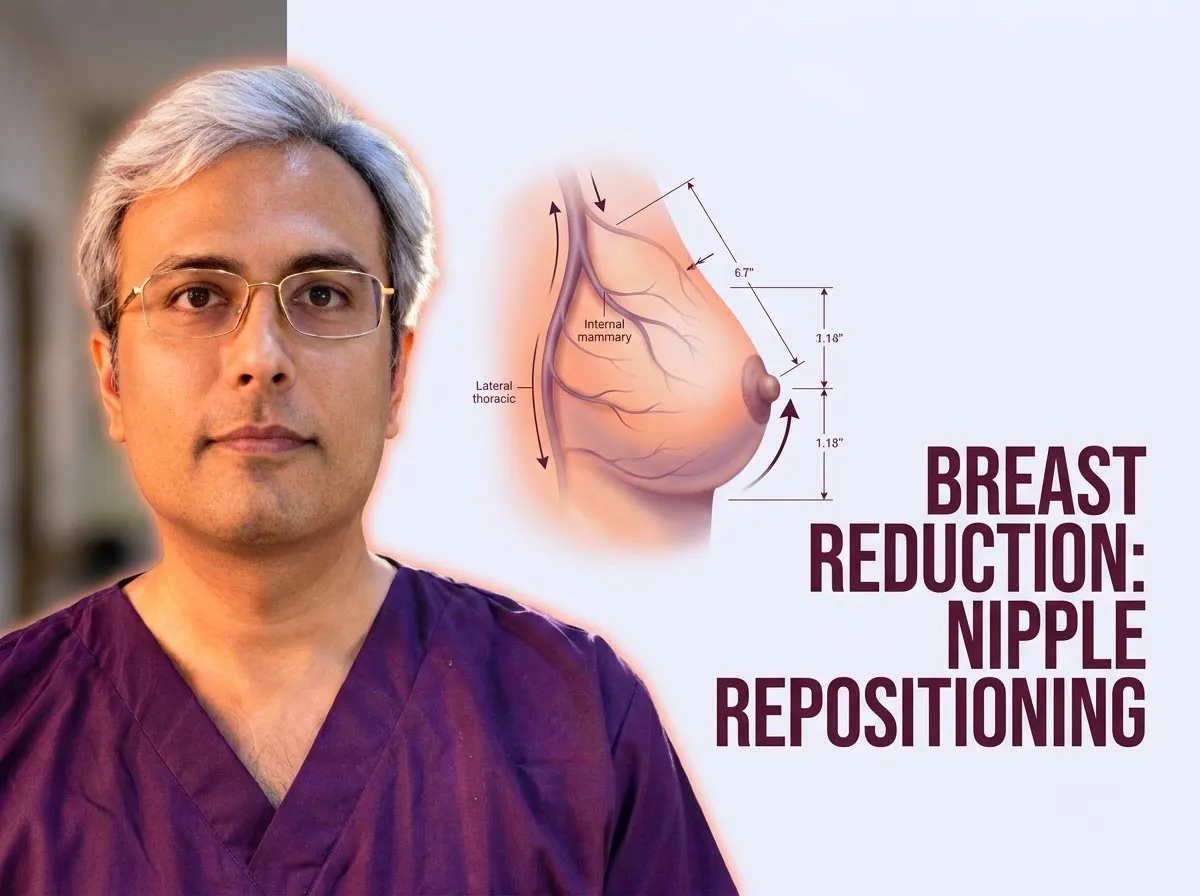
Nipple Repositioning in Breast Reduction Surgery: A Comprehensive Clinical Guide
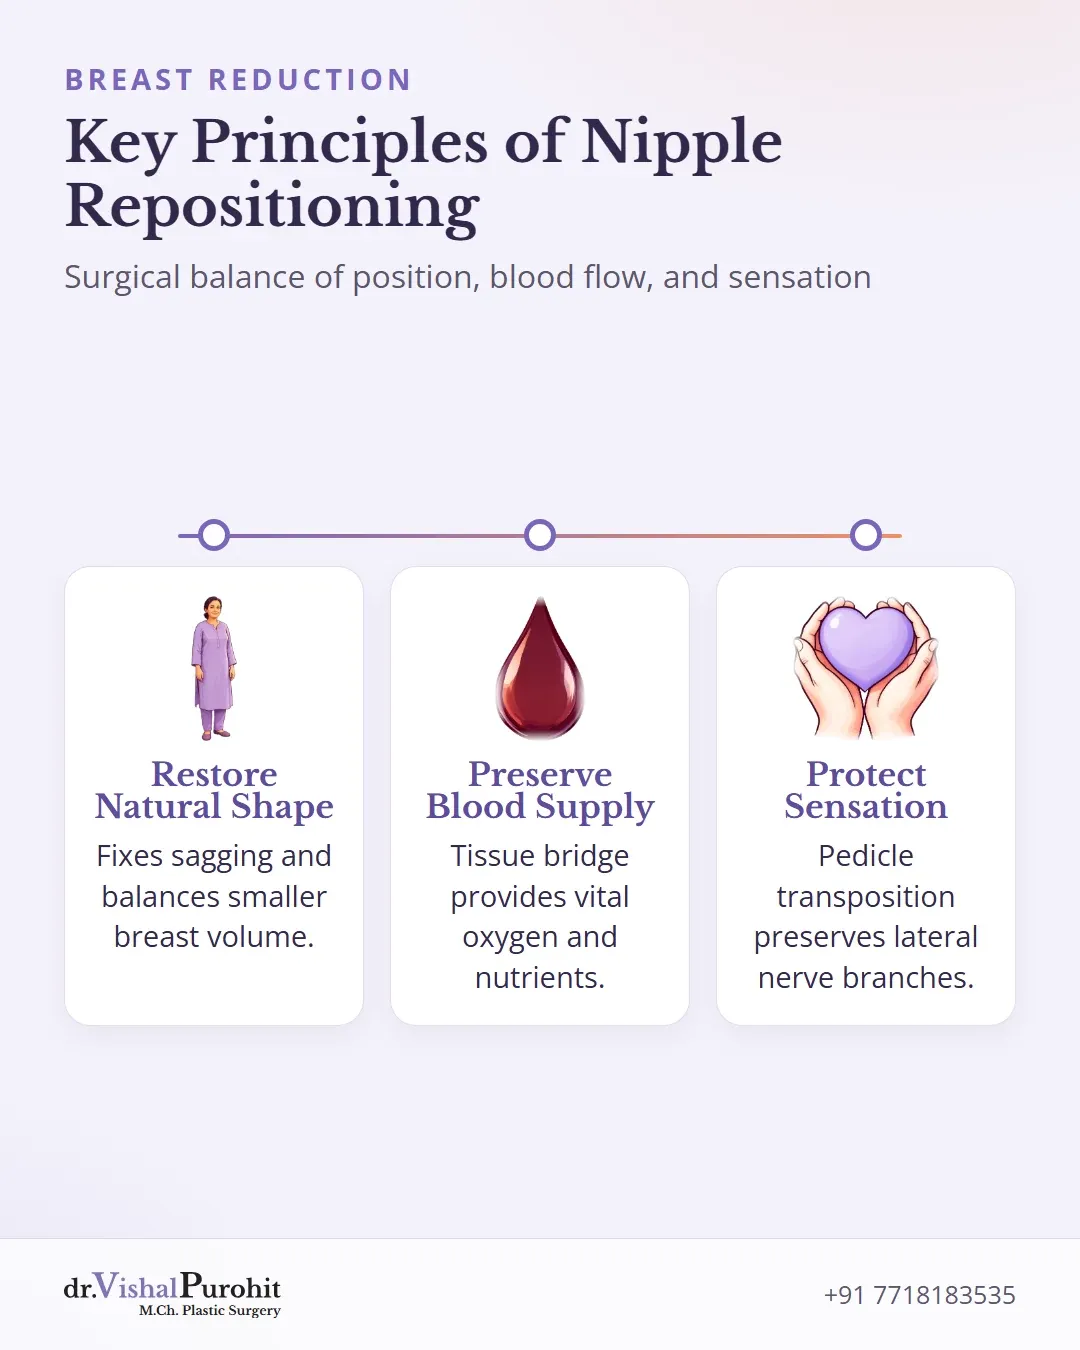
Nipple repositioning is a key part of breast reduction. It fixes sagging and restores the natural shape of the breast.
Instead of just removing size, surgeons move the nipple to a better spot. This keeps the breast looking youthful and balanced.
Moving the nipple fits it to your new, smaller shape. This creates a refined look and a better overall silhouette.
This process blends safety with a creative touch. It helps patients feel better and regain their self-esteem.
If you want to improve your look and quality of life, seek expert help. Consulting a specialist in breast reduction surgery in Jaipur can give you a plan made for your unique body.
Nipple repositioning is more than a technical step. It is the main way to restore your confidence.
The goal is to help you look and feel beautiful. This approach balances medical skill with your personal needs.
Determining Vertical Displacement Distance for Natural Projection
Surgeons use anatomical landmarks to find the right spot for your nipple.
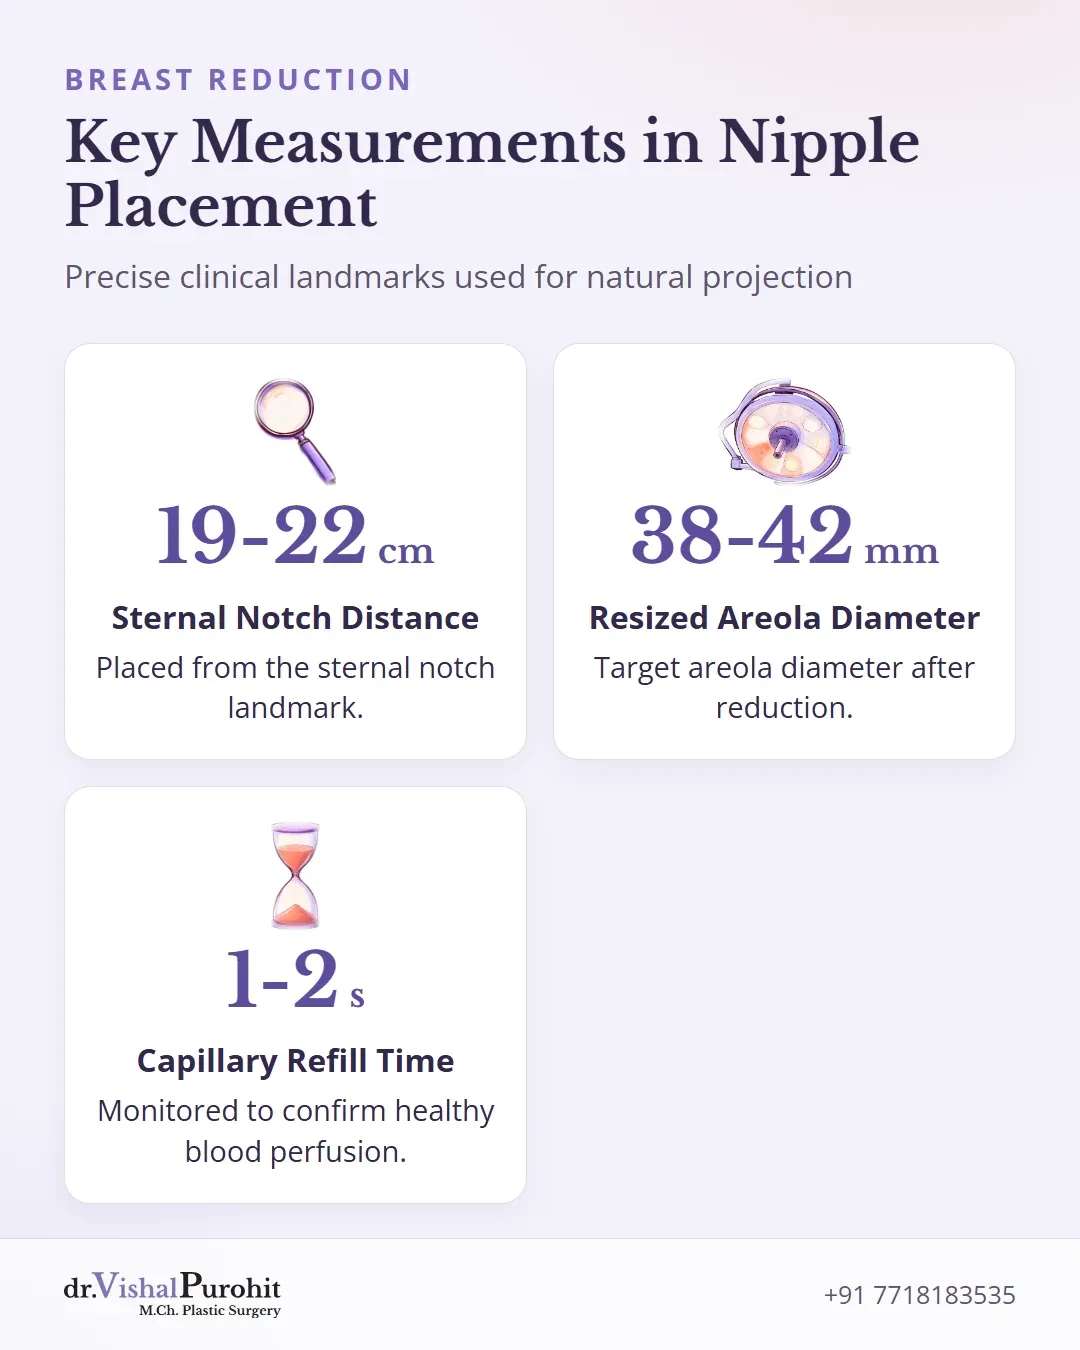
Dr. Purohit's note: In Dr. Vishal Purohit's practice in Jaipur, key measurements include placing the new nipple position about 19 to 22 cm from the sternal notch, resizing the areola to about 38 to 42 mm in diameter, and using the inframammary fold, the natural crease where your breast meets your chest.
To fix breast ptosis (sagging), the surgeon finds the vertical displacement. This is the distance your nipple needs to move up.
The goal is a youthful projection that looks natural. Some surgeons mark the spot based on the “vertical deficiency of the upper pole volume” upper-pole marking principle1. This means they check how much fullness is missing from the top.
Surgeons often support the breast while marking. This helps “prevent excessively high NAC position postoperatively” NAC positioning study2. This planning ensures your new shape fits your body perfectly.
Preserving Vascularity: The Role of Pedicle Selection
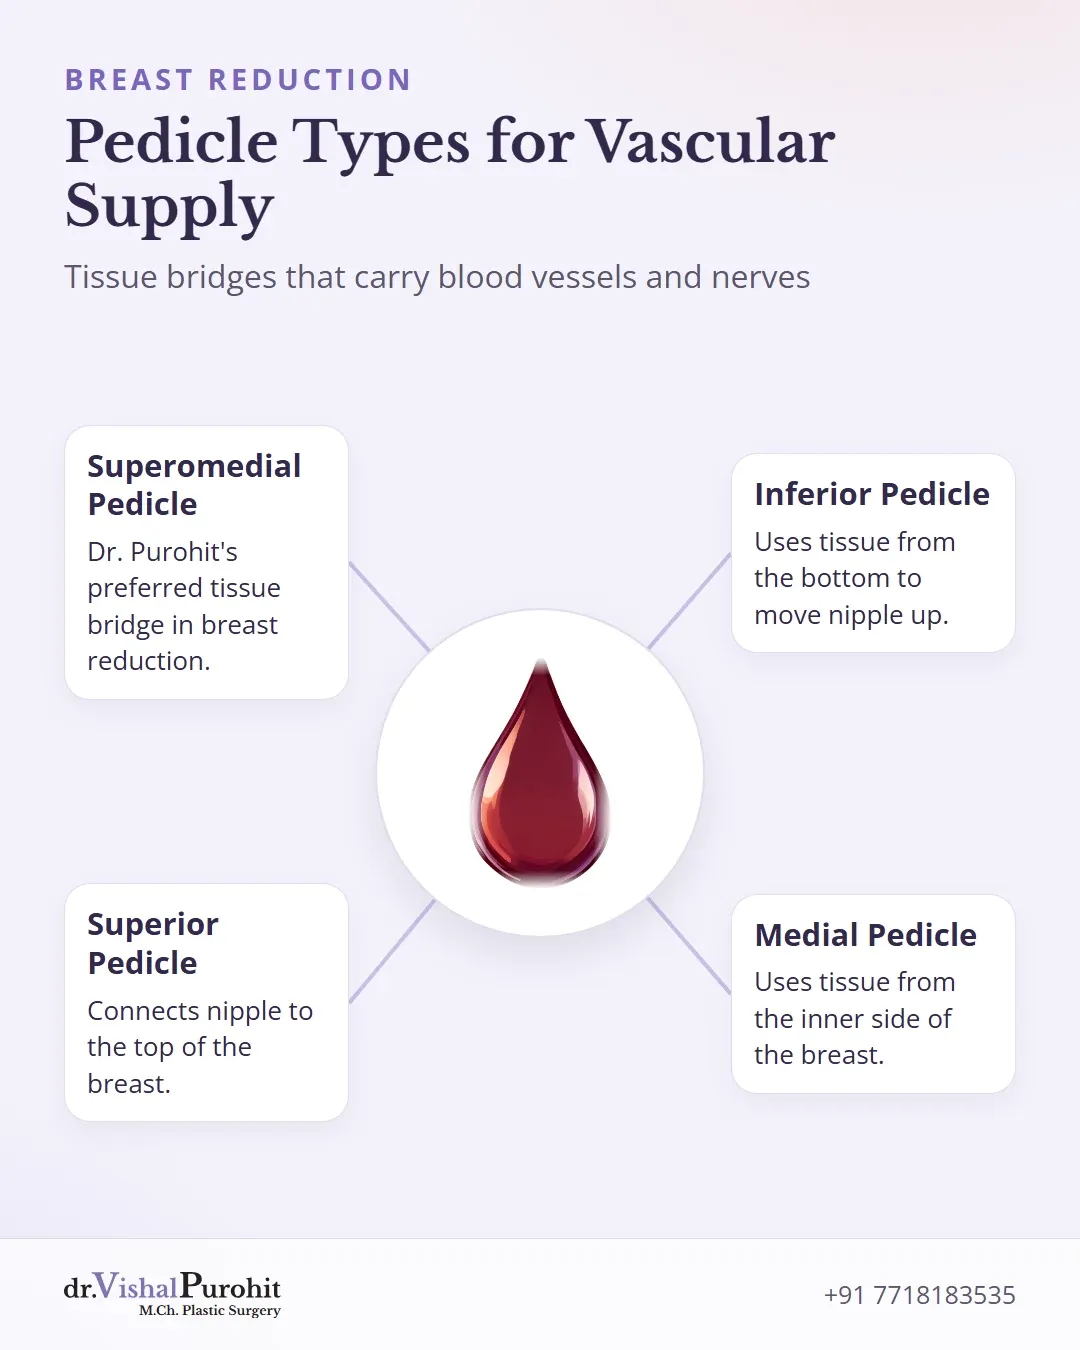
Your surgeon must protect your blood supply to keep the nipple healthy. They use a tissue bridge called a Pedicle Type.
This bridge gives the nipple oxygen and nutrients. Without good vascularity, you risk nipple necrosis, which happens when tissue dies.
The choice of pedicle depends on your body and the different incision types used. Surgeons plan the bridge to “incorporate maximal blood supply” pedicle blood-supply planning3.
Here are the common types of tissue bridges:
- Superomedial pedicle: The superomedial pedicle is Dr. Vishal Purohit’s preferred pedicle in breast reduction surgery in Jaipur.
- Superior pedicle: This bridge connects the nipple to the top of the breast. It is safe for large reductions and shows “no statistically significant increase in NAC necrosis rates” no statistically significant increase in NAC necrosis rates4.
- Inferior pedicle: This bridge uses tissue from the bottom of the breast to move the nipple up, and is also used by Dr. Purohit.
- Medial pedicle: This bridge uses tissue from the inner side of the breast.
Vascular Safety
Your surgeon picks the right path to avoid "vascular kinking" pedicle handling3. This ensures blood vessels do not pinch or fold.
Aesthetic Balance
This careful planning protects both your health and your beauty.
Grafting Alternative
For very large breasts, free nipple grafting is offered.
Optimizing the Nipple-Areola Complex (NAC) Diameter
When breasts get smaller, the dark circle around the nipple often looks too big. Your surgeon uses areola reduction to fix this.
This makes sure your NAC diameter (the width of the nipple and areola) fits your new breast volume. In Dr. Vishal Purohit’s practice in Jaipur, the areola is resized to about 38 to 42 mm in diameter.
This proportionality is key to aesthetic symmetry. It means both breasts look balanced and natural.
| Goal | How it is Achieved | Expected Result |
|---|---|---|
| Balanced Scale | The surgeon uses a template to “outline the prospective areola” areola templating technique5 to match your size. | A nipple area that looks natural for smaller breasts. |
| Visual Harmony | Removing skin so the areola is resized to about 38 to 42 mm in diameter in Dr. Purohit’s practice (compared to literature where “areola measured 5.5 cm in diameter and were symmetrically placed”6). | Both sides match in width and position. |
| Skin Refinement | Using precise cuts and stitches to remove extra tissue. | A smooth, round areola that boosts your confidence. |
Advanced Suture Techniques for NAC Attachment
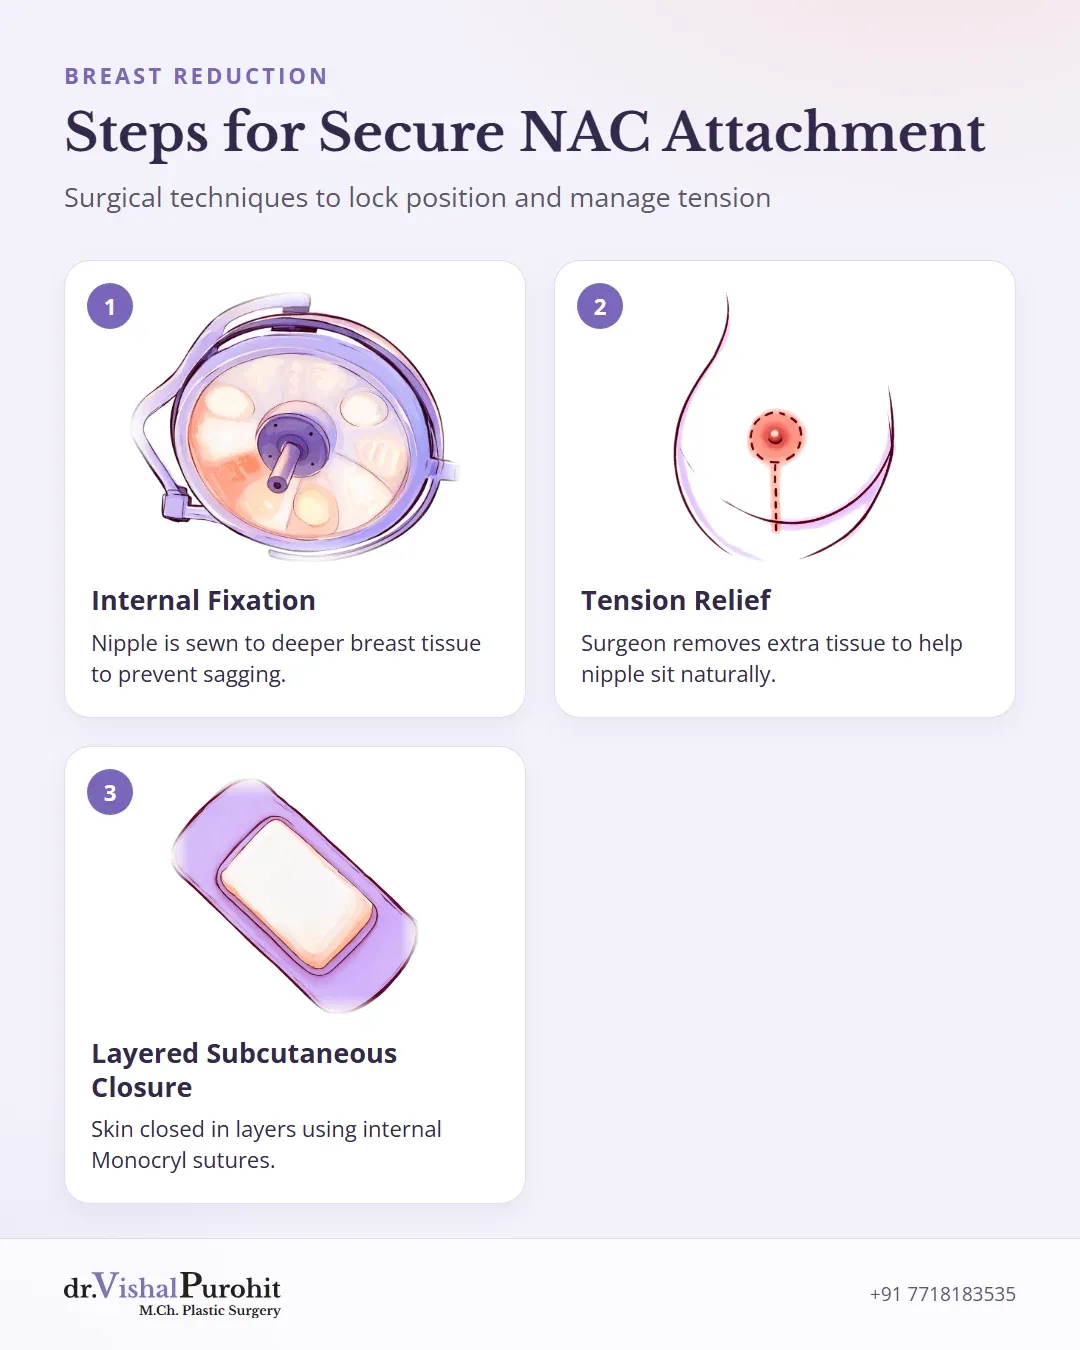
Once your nipple is in the right spot, your surgeon uses a surgical suture technique to lock it. In his practice in Jaipur, Dr. Vishal Purohit closes the skin with subcutaneous (buried) stitches in layers using internal Monocryl sutures. This prevents nipple sagging and keeps your new shape firm.
Key points
- Surgeons use layered internal sutures to secure the nipple-areola complex to deeper breast tissue.
- Careful tension management prevents pulling and ensures the nipple sits naturally.
- Internal tethering and absorbable support stitches keep the breast shape lifted during healing.
The surgeon uses internal fixation by sewing the nipple to deeper breast tissue. For example, some methods use “eight Vicryl 4/0 sutures placed around the circumference of the areola” areola fixation method7 to secure the area.
Surgeons must manage tissue tension to avoid a droopy look. If the skin is too tight, it can pull the nipple out of place.
To fix this, the surgeon may remove extra tissue to “relieve tension” tension-relief suturing7 around the site. This helps the nipple sit naturally, whether you have lollipop and anchor incisions.
Some advanced methods use tethering, which works like an internal bra. Specialized loops reshape the breast and support the nipple.
Other techniques place an “absorbable suture around the areola” internal-support technique8 for temporary support. These stitches eventually dissolve, while your body creates scar tissue to keep the nipple lifted.
Clinical Outcomes: Sensation Preservation and Nerve Impact
Moving the nipple affects your nerves. This nerve impact happens because surgery “will certainly divide a variable number of innervating nerve fibres” sensory innervation anatomy9.
Dr. Vishal Purohit uses pedicled transposition to keep the nipple attached, designed to preserve the 4th lateral intercostal nerve branch for sensation. This helps with nipple sensation changes.
The sensation preservation rate depends on the method used. For example, “half of the total number of patients reported altered sensation in the nippleareola region” sensation outcomes series9.
Keeping a strong link between the nipple and gland is key. This improves your breast sensitivity. You may also wonder how much smaller breasts can be after surgery.
Sensory recovery depends on how you heal. Dr. Purohit protects key paths, like the lateral neurovascular pedicle10, with the superomedial pedicle being his preferred technique.
Focusing on nerve health leads to better reconstructive outcomes. It helps you feel confident and natural.
Frequently Asked Questions
How is the nipple-areola complex safely repositioned during breast reduction?
The nipple-areola complex (NAC) is repositioned higher onto the breast mound while remaining attached to a living tissue ‘pedicle’ (superomedial or inferior pedicle; the superomedial pedicle is Dr. Vishal Purohit’s preferred pedicle) containing its intact neurovascular and blood supply, performed by Dr. Vishal Purohit in Jaipur. The pedicle carries blood and nerve fibers to the new apex. As an M.Ch. plastic surgeon, Dr. Purohit preserves nipple vitality with loupe-magnified precision.
What is the difference between a pedicle flap and a free nipple graft?

A pedicle flap keeps the nipple continuously connected to its original blood vessels and nerves to preserve sensation, although the chances of breastfeeding afterwards are slim. A free nipple graft completely severs the nipple and re-implants it like a skin graft for very large breasts. Free nipple grafts sacrifice lactation and natural sensation. Dr. Vishal Purohit offers both pedicle techniques and free nipple grafting depending on individual assessment.
Can the size of an enlarged areola be reduced during the procedure?
Yes, enlarged or stretched areolas are routinely resized to about 38 to 42 mm in diameter during breast reduction surgery with Dr. Vishal Purohit in Jaipur. Excess outer areolar pigment is excised, and the border is secured with deep dermal purse-string sutures. As an M.Ch. plastic surgeon, Dr. Purohit ensures symmetrical, natural areolar dimensions.
How does Dr. Vishal Purohit monitor nipple blood flow during and after surgery?
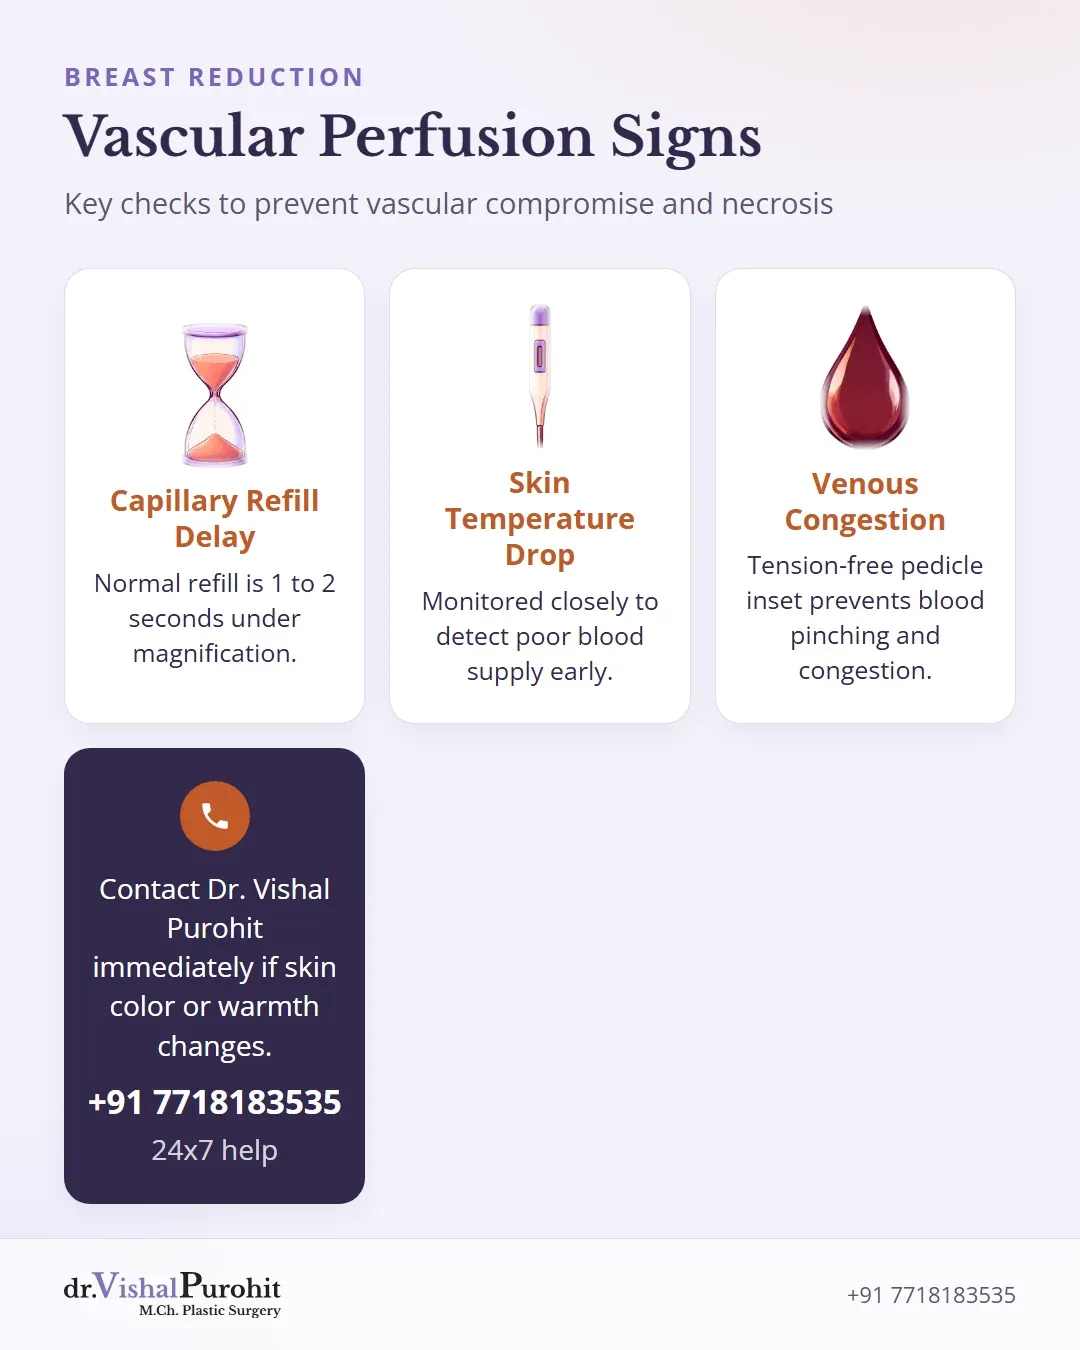
Dr. Vishal Purohit in Jaipur monitors capillary refill time (1 to 2 seconds), skin temperature, and dermal bleeding characteristics under surgical loupe magnification intraoperatively and during hospital rounds. Gentle, tension-free pedicle inset ensures robust microvascular perfusion without venous congestion. Dr. Purohit’s careful vascular monitoring is designed to protect the nipple.
A great result takes a careful balance. Your surgeon moves the nipple for a youthful look.
They also protect your blood supply and nerves. This makes sure your breasts look natural and stay healthy.
Every body is different. Because of this, precise anatomical planning is essential.
You should always talk to an M.Ch. plastic and reconstructive surgeon to plan your procedure.
Ready to feel confident in your skin? Book a professional consultation in Jaipur today.
If you would like to discuss your condition or book a consultation, contact Dr. Vishal Purohit in Jaipur at +91 7718183535. Our specialist team is here to guide you through every step of your care. For the full picture, explore our complete guide to breast reduction in Jaipur or learn more about our surgical center for breast reduction in Jaipur.