One of the first questions I hear during a consultation isn’t about the surgery itself—it is about the aftermath. “Doctor, will everyone know I had surgery? Will I have a big scar on my chest?”
When planning incisions, an M.Ch gynecomastia surgeon in Jaipur follows the natural contour of the areola to keep any mark as inconspicuous as possible.
This is a valid fear. You are choosing surgery to feel confident going shirtless, so trading “man boobs” for a visible, jagged scar defeats the purpose.
As a specialist in Gynecomastia Surgery in Jaipur, my goal is not just to remove the gland, but to leave the scar as small and as well hidden as possible. In this guide, I will explain the reality of scarring and the incision techniques we use to keep scars discreet.
The Reality: Does Surgery Leave Scars?

In plastic surgery, there is a saying: “Only a ghost leaves no tracks.” Technically, any time an incision is made in the skin, a scar is formed.
The scar changes and settles during the healing process, and Dr. Vishal Purohit reviews it at each follow-up visit.
Dr. Purohit’s note: In his practice, scar treatment is needed only in a few patients; firm scar massage and silicone sheets or gel are started if signs of a hypertrophic scar appear.
However, there is a difference between a scar and a visible scar.
The goal of aesthetic male breast reduction is to place incisions where they are naturally camouflaged by the body’s anatomy. Historically, gynecomastia was treated by subcutaneous mastectomy through circumareolar, Webster-type or inframammary incisions, which removed the gland well but often left unacceptable scars2.
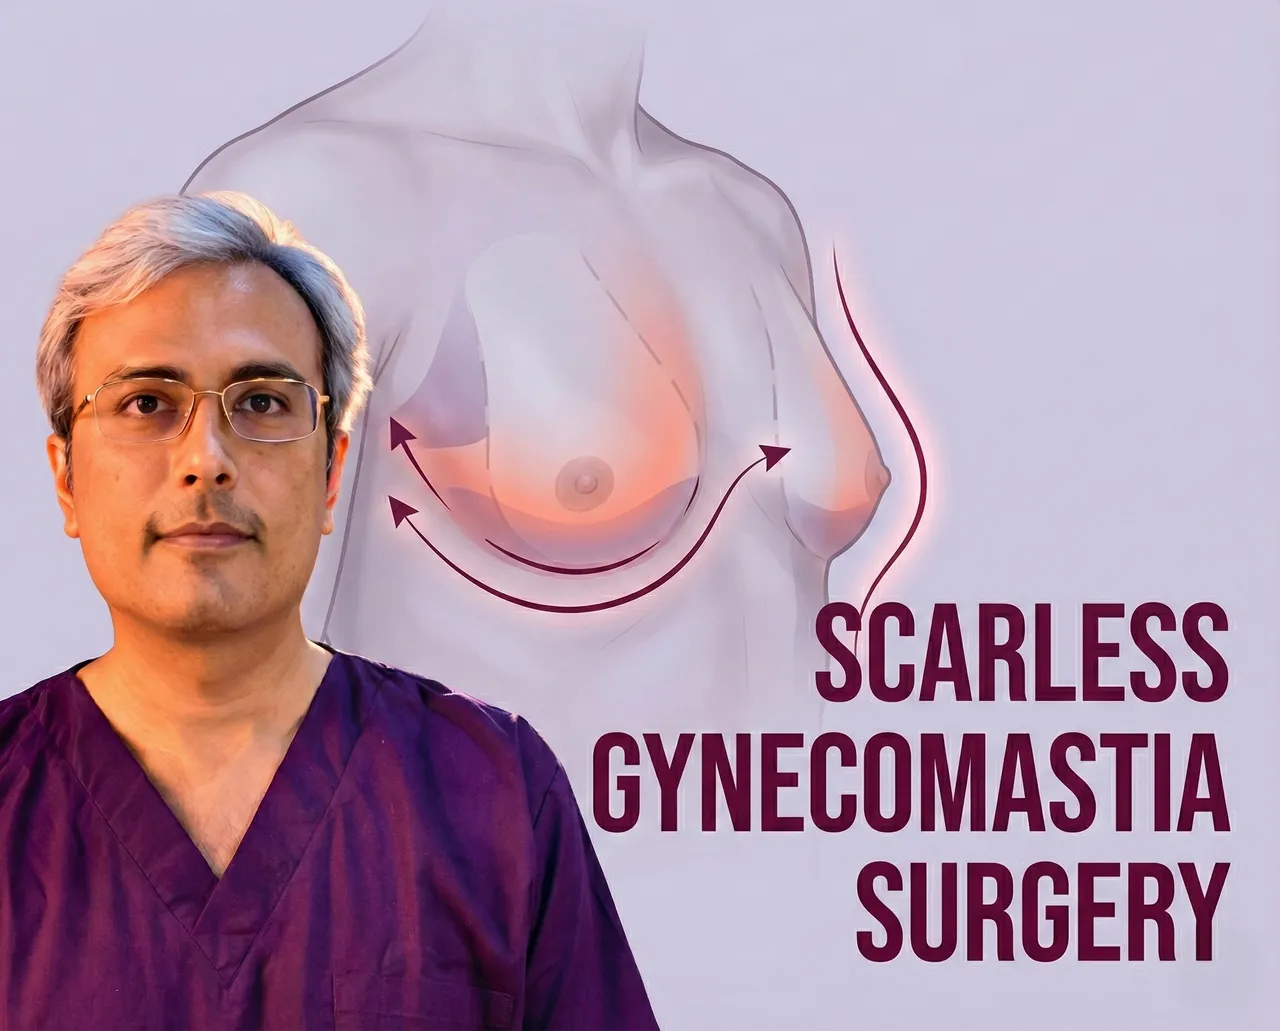
Today, Dr. Vishal Purohit performs gland excision through an inconspicuous hemi-periareolar incision along the lower half of the areola border, combined with liposuction1. An inconspicuous scar does not mean that no line remains: a fine line is present, and how it heals varies from person to person.
The specific location of the incision depends largely on the gynecomastia surgical technique used. Gynecomastia surgery may involve:
- Liposuction
- Excision of tissue
- A combination of both3
For liposuction entry points, Dr. Vishal Purohit uses two small openings on each side at the outer edge of the pectoralis major muscle along the anterior axillary line.
Male Chest Reduction Incision & Scar Profile Comparison
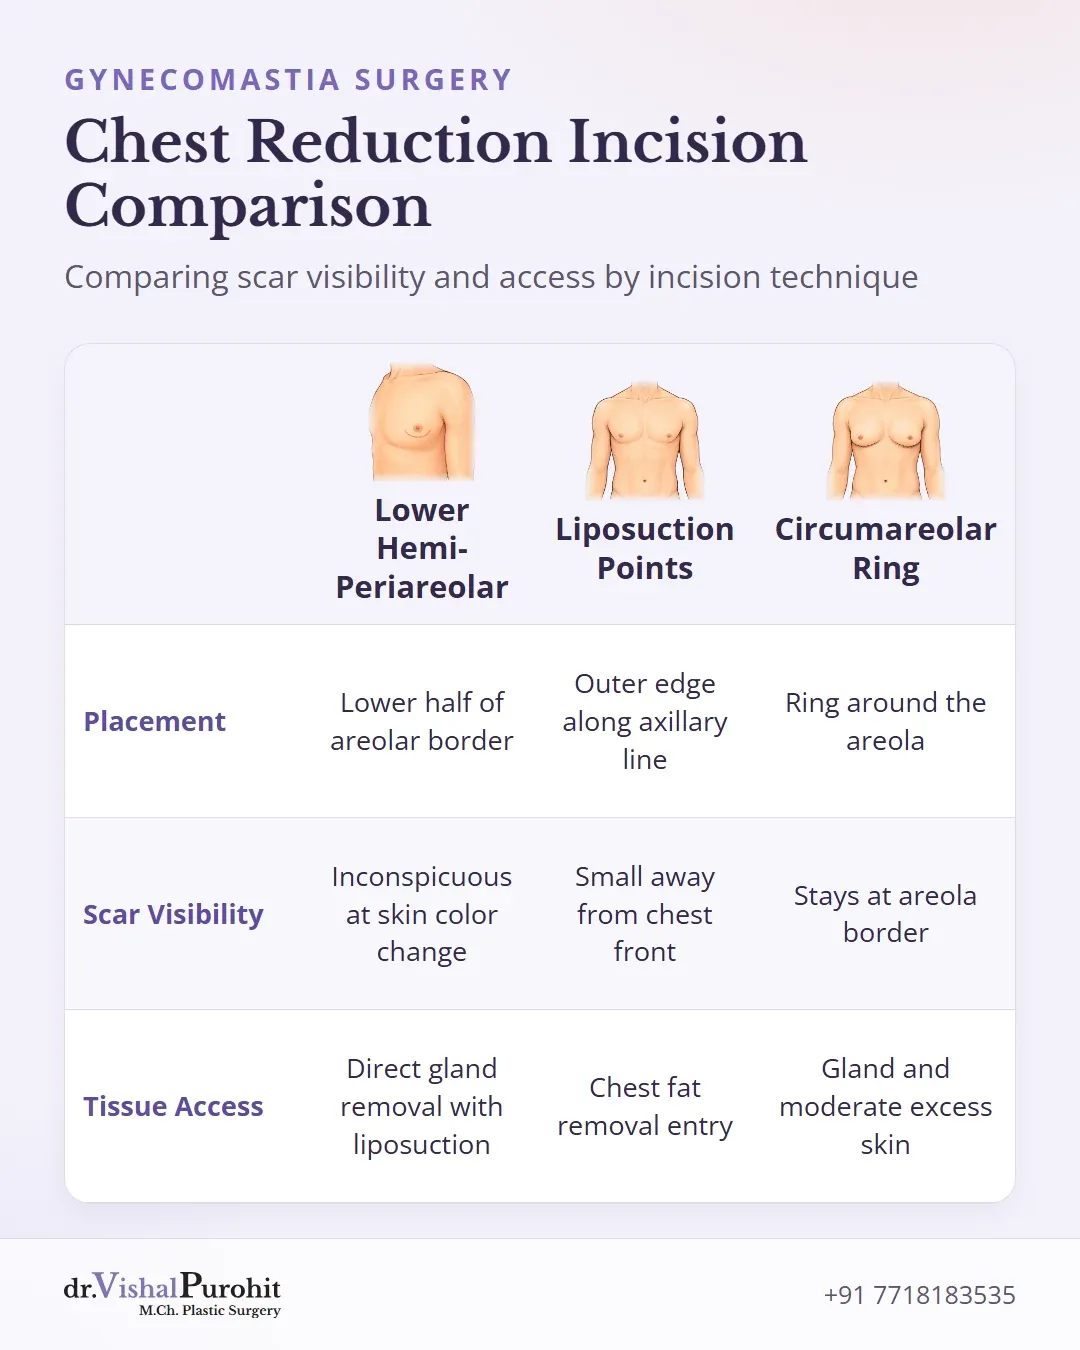
| Incision Technique | Incision Placement | Scar Visibility | Tissue Access Capability |
|---|---|---|---|
| Lower hemi-periareolar (Webster-type) | Along the lower half of the areolar border | Inconspicuous, at the colour change between areola and chest skin1 | Direct removal of the gland, usually combined with liposuction4 |
| Liposuction entry points | Two small openings on each side at the outer edge of the pectoralis major muscle along the anterior axillary line56 | Small, away from the front of the chest | Liposuction of the chest; some techniques also remove the gland through a 3-mm puncture7 |
| Circumareolar (around the areola) | A ring around the areola, used when excess skin is removed | Scar stays at the areola, but excessive skin removal can widen it or cause rippling1 | Gland removal plus a moderate amount of excess skin4 |
| Long chest scar or free nipple graft | Across the chest | The most visible option; free nipple grafts can lose pigment1 | Extreme excess skin, for example after massive weight loss8 |
Strategic Incision Placement: Minimising Visible Scars
No surgeon can promise a scar that leaves no trace. The aim is a scar placed where the body’s anatomy hides it well, so that it is hard to notice once healed.
For Gland Excision (The Webster Incision)
When removing the firm glandular tissue, Dr. Vishal Purohit uses a hemi-periareolar incision.
Incision Location
In Dr. Vishal Purohit’s Jaipur practice, the gland is removed through an inconspicuous incision along the lower half of the areolar border (the darker skin surrounding the nipple), combined with tumescent liposuction.
Natural Camouflage
The scar sits where the darker areolar skin meets the lighter chest skin, which is why this placement is used for an inconspicuous scar1. Because male skin is thicker, wide periareolar incisions are avoided, to lower the risk of widened, thick or puckered scars2.
Clinical Efficacy
Liposuction alone usually will not fully correct a significant proportion of gynecomastia cases, and recurrence may be higher when the gland is not removed7. In a study of 30 men with grade I/II gynecomastia, liposuction and gland removal through a single 1-cm incision at the lower outer areolar border gave good aesthetic outcomes9.
For Liposuction (Fat Removal)
- Location: In Dr. Vishal Purohit’s practice, these are placed as two small openings on each side. Published techniques also describe small stab incisions along the anterior axillary line at the level of the breast crease56, with reported sizes ranging from a 3-mm puncture7 to a 5-mm stab incision5.
- The Camouflage: These entry points sit on the side of the chest rather than the front.
Scars by Grade: What to Expect
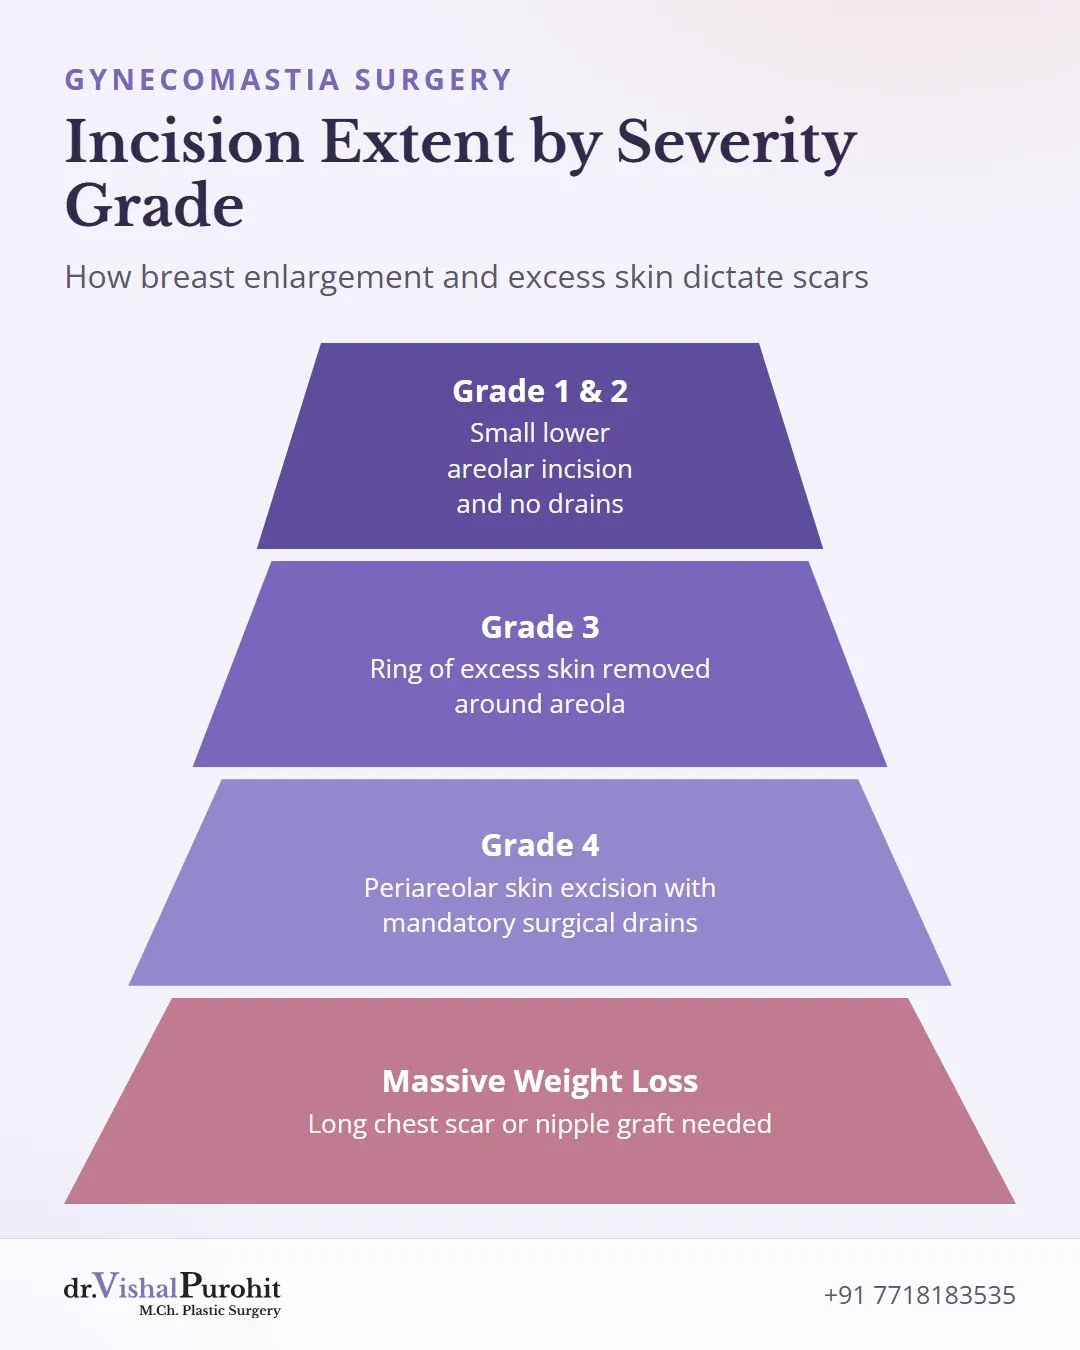
The extent of scarring depends heavily on the severity of the condition. The Simon classification grades gynecomastia by size and by whether there is excess skin10:
Key points
- Scarring depends on the severity of gynecomastia and whether excess skin must be removed.
- Lower grades typically leave small scars at the lower areolar border without needing drains.
- Higher grades require skin removal that may result in circumareolar scars or longer chest scars.
- Grade I: small, no excess skin
- Grade IIa: moderate, no excess skin
- Grade IIb: moderate, with excess skin
- Grade III: marked, with excess skin
A four-grade version of the same scale is also widely used11, and it is the one used below.
-
Grade 1 & 2 (Minor to Moderate, no excess skin): For these grades, liposuction combined with gland excision through a small lower hemi-circumareolar incision is recommended4. This is the incision Dr. Purohit uses, and lower grades usually do not need drains.
-
Grade 3 (Moderate Enlargement with Excess Skin): A ring of skin around the areola may be removed in the same operation, so the scar still stays at the areola4. Standard circumareolar surgery in this group can lead to thick scars and a widened areola12, so the amount of skin removed is planned carefully.
-
Grade 4 (Marked Enlargement with Excess Skin): Severe gynecomastia usually needs some form of skin removal1. The periareolar pattern can be used in almost all such patients except the most extreme cases1. In his practice, Dr. Vishal Purohit removes excess skin when needed, but the areola is not reduced.
-
The Trade-Off: After massive weight loss, a good chest contour cannot be restored without leaving a significant scar8. A long scar across the chest, or the loss of pigment seen with free nipple grafting, is the price of a flat chest in these cases1. In Dr. Vishal Purohit’s Jaipur practice, grade 4 surgery can take up to about 4 hours, and grade 4 is the only grade in which drains are placed.
Why Not Just Liposuction? (Avoiding Bad Scars)
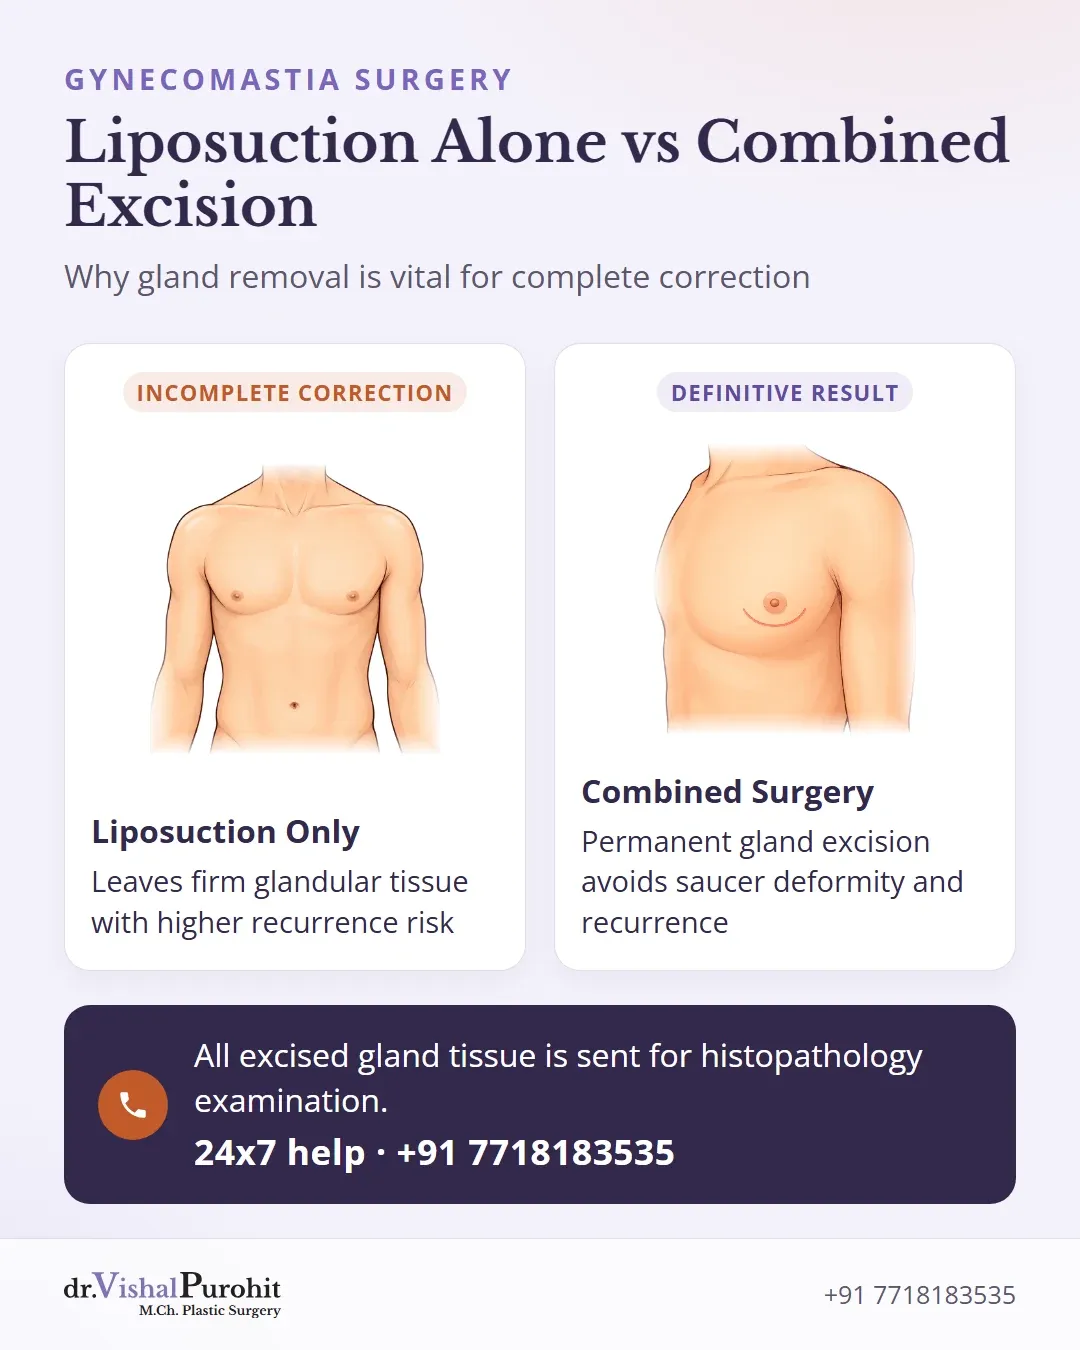
Some patients ask for “liposuction only” to avoid the small areolar scar. When the chest is mostly fat, liposuction alone may be enough; when the gland is dense, removing it gives better results13.
Myth: Liposuction alone will always correct gynecomastia and avoid surgical scars.
Fact: If the gland is dense, liposuction alone usually will not fully correct the chest, and true recurrence is biologically not possible once the gland is surgically removed.
Dr. Vishal Purohit notes that once the gland is removed surgically, true recurrence is biologically not possible, and any fullness afterwards represents residual tissue7.
Removing fat first allows the gland to be excised through a smaller incision, which keeps the scar small4. Careful dissection prevents a saucer deformity, leaving enough tissue under the areola to avoid a sunken look1.
Gland removal also allows the tissue to be examined: where there is any concern about malignancy, direct excision is preferred so the tissue can be sent for pathology1. In Dr. Vishal Purohit’s Jaipur practice, all excised tissue is always sent for histopathology.
Post-Op Protocol: How to Minimise Scarring
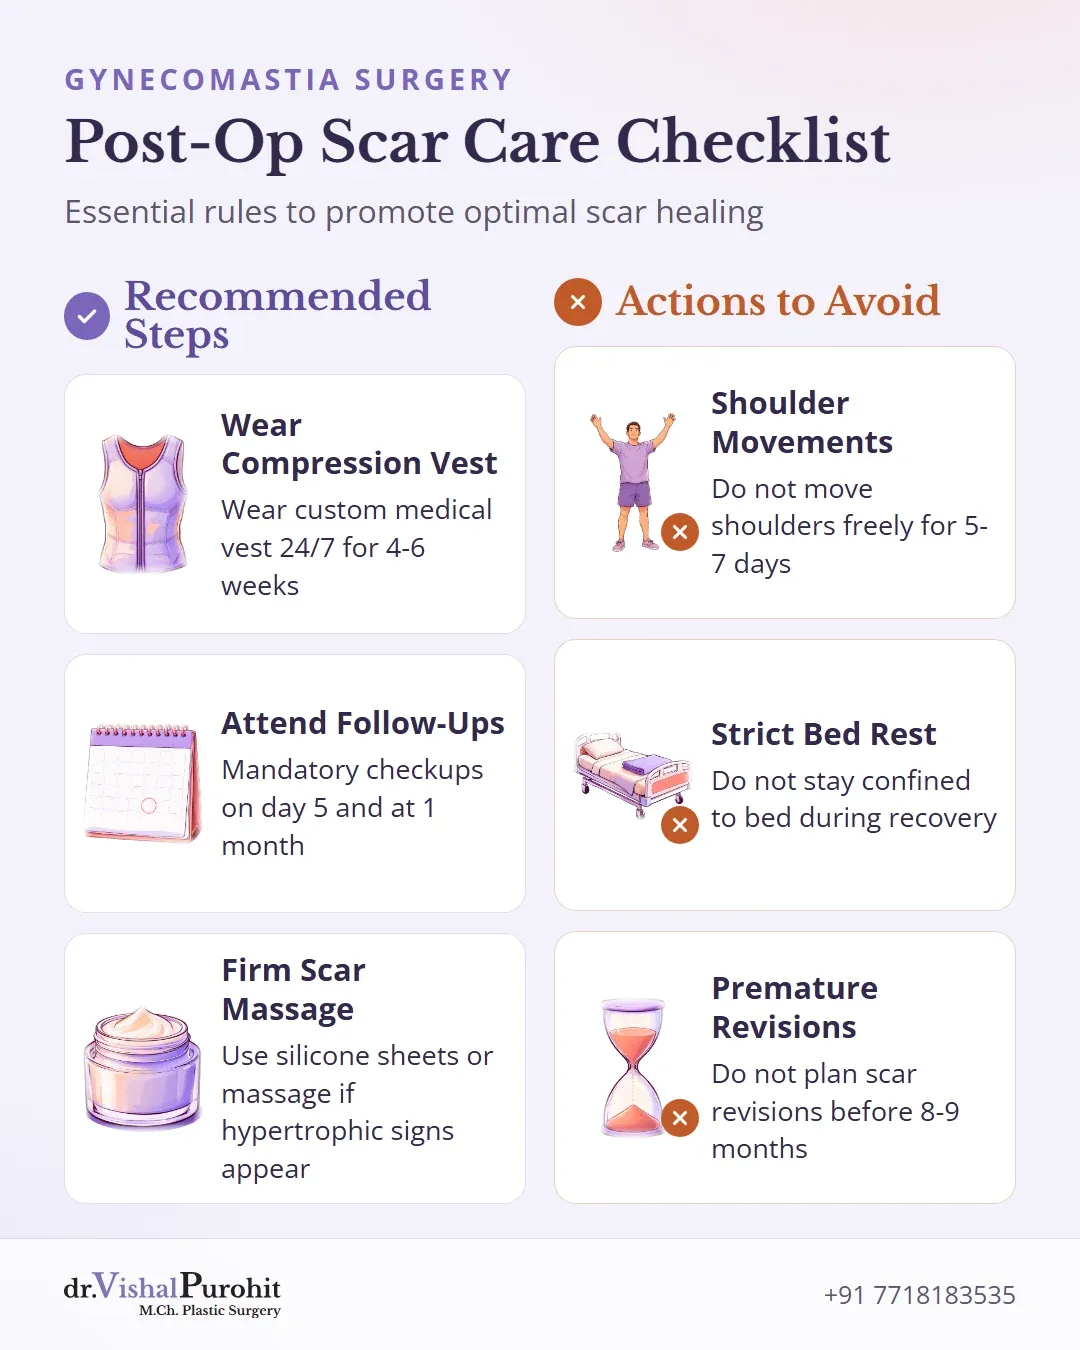

Good surgical technique is only part of the result; how the wound heals matters too. Patients follow Dr. Purohit’s recovery instructions closely, especially when addressing concerns about scars and nipple appearance.
- Tension-free closure: Closing wounds under excessive tension can worsen scarring and distort the nipple1, which is why skin removal is planned with care.
- Compression vest: In Dr. Vishal Purohit’s Jaipur practice, a custom medical-grade compression vest is worn 24/7 for 4 to 6 weeks, and shoulder movement is strictly restricted for the first 5 to 7 days. Bed rest is never advised.
- Follow-up visits: Mandatory visits on day 5 (first pressure-garment release and dressing removal or change if needed) and at 1 month let Dr. Purohit check the incision. Help is available 24x7.
- Silicone Gel Sheets: In Dr. Purohit’s practice, scar treatment is needed only in a few patients; firm scar massage and silicone sheets or gel are started if signs of a hypertrophic scar appear14.
- If a scar heals poorly: Unfavourable scarring is a recognised risk of the operation and is discussed before consent15. Widened scars and rippling can be improved with a minor revision1. If a patient is not satisfied, Dr. Purohit plans a revision or touch-up with a gap of 8 to 9 months after the first surgery.
Expert Gynecomastia Surgery & Male Chest Contouring in Jaipur
Are you dealing with enlarged male breast tissue or stubborn chest fullness? Schedule a confidential clinical evaluation with Dr. Vishal Purohit, M.Ch. plastic and cosmetic surgeon in Jaipur.
Understanding the causes, grades, and treatment of gynecomastia helps determine the right approach for your chest anatomy.
During your consultation, you can discuss personalized options for gynecomastia surgery in Jaipur, including surgical techniques, recovery expectations, and pricing.
This is educational information, not medical advice.