

Most articles about eyelid surgery safety spend their word count on reassurance. This one won’t. If you are considering blepharoplasty, what you need is an accurate map of what can go wrong — the common annoyances, the correctable setbacks, and the one rare emergency that you must be able to recognise yourself.
Blepharoplasty is among the most predictable operations in aesthetic surgery. It is also performed on tissue less than a millimetre thick, sitting directly over the eye. Both things are true at once, and understanding the second is what makes the first reliable.
For the full picture of the procedure itself, see our complete guide to blepharoplasty.
The Most Common Complication Is Not the One People Worry About
Ask a patient what they fear and they will usually say scarring or infection. Ask a surgeon and the answer is dry eye.
In a single-surgeon review of 892 upper and lower blepharoplasty cases published in JAMA Facial Plastic Surgery, dry eye symptoms were reported in 26.5% of patients and chemosis — a boggy swelling of the conjunctiva — in 26.3%. Both are usually temporary. Neither is rare.
The mechanism is straightforward. Eyelid surgery temporarily alters how completely and how often you blink, and the tear film depends on both. Symptoms include grittiness, burning, light sensitivity, and — counter-intuitively — watering, because a dry eye reflexively over-produces tears.
The study also identified who is most at risk. Patients who developed incomplete lid closure after surgery had roughly double the rate of dry eye symptoms compared with those who did not. Chemosis was substantially more frequent when a canthopexy was performed alongside the blepharoplasty. Pre-existing scleral show and pre-existing dry eye were themselves predictors.
This is why the pre-operative eye examination matters more than any intra-operative refinement. A patient with a marginal tear film before surgery will have a worse one afterwards.
Management: preservative-free lubricating drops, night-time ointment, and in some cases temporary taping or punctal plugs. Most cases resolve within weeks to a few months as blink dynamics normalise. Persistent cases are managed jointly with an ophthalmologist.
Surgical Safety Profile & Complication Prophylaxis Protocols
| Potential Complication | Incidence Rate | Preventative Surgical Protocol | Corrective Action If Required |
|---|---|---|---|
| Lagophthalmos (Incomplete Closure) | Under 2% chronic | Conservative skin pinch test; sparing anterior lamella | Lubrication, massage; full-thickness skin graft rarely |
| Ectropion (Lower Lid Eversion) | Under 1.5% | Prophylactic canthopexy or canthoplasty in lax lids | Taping, steroid injection; lateral tarsal strip revision |
| Retrobulbar Hematoma | Extremely rare (under 0.05%) | Meticulous bipolar electrocautery; blood pressure control | Surgical emergency: immediate lateral canthotomy |
| Infection | Under 0.5% | Sterile laminar airflow OT; pre-op antiseptic prep | Topical and oral targeted antibiotics |
| Hypertrophic Scarring | Under 1% | Precise tension-free subcuticular wound closure | Silicone gel, sun protection, fractional laser |
The Rare Emergency: Retrobulbar Haemorrhage
This is the section to read twice.
Bleeding behind the eyeball raises pressure inside the bony orbit. Because the orbit cannot expand, that pressure compresses the optic nerve and its blood supply. Without decompression within hours, vision loss can be permanent.
The largest dataset on this comes from a survey of American Society of Ophthalmic Plastic and Reconstructive Surgery members covering 269,433 blepharoplasty cases. Across those cases there were 149 orbital haemorrhages, 48 associated with temporary visual loss and 12 with permanent visual loss. That works out to roughly one haemorrhage per 1,800 procedures and permanent visual loss in the region of one per 22,000.
Two findings from that survey change how you should behave after surgery.
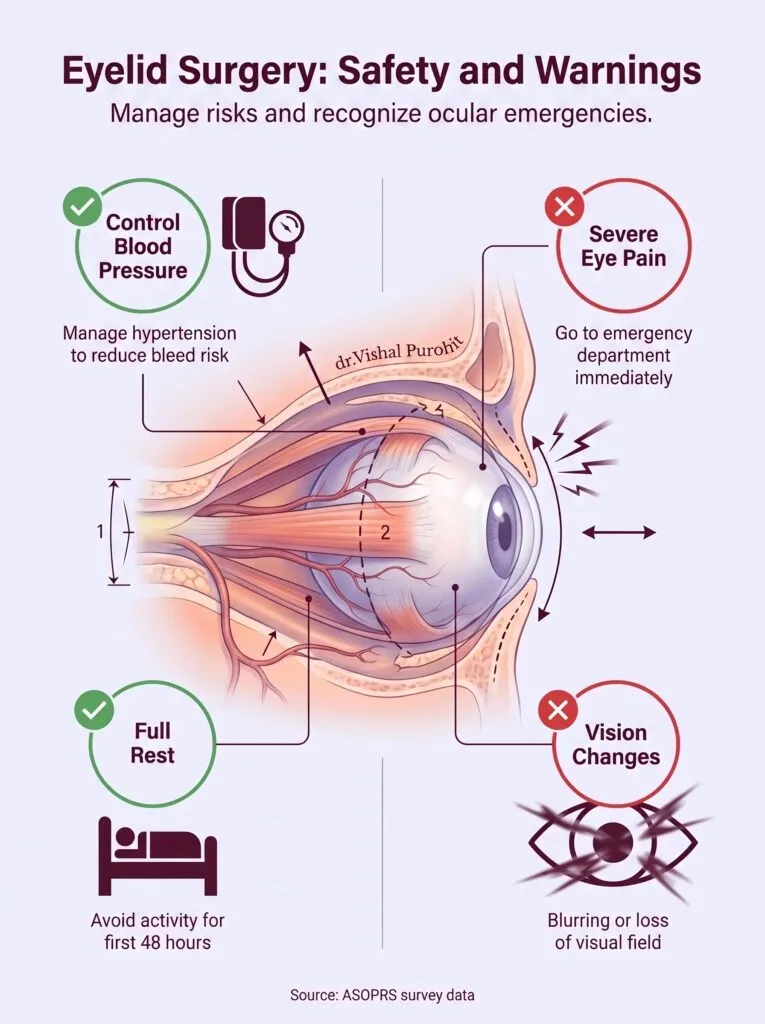
Timing. The majority of bleeds occurred within the first three hours after surgery, and risk fell substantially after 24 hours. This is why we do not send you straight home to an empty house, and why the first night matters.
Contributing factors. The recurring associations were hypertension, peri-operative aspirin use, post-operative vomiting, and increased physical activity. Every one of those is modifiable. Controlling your blood pressure, disclosing every medication and supplement, taking anti-nausea medication seriously, and genuinely resting for the first 48 hours are not polite suggestions — they are the intervention.
Warning signs: go to an emergency department immediately
Do not wait for a clinic appointment. Do not send a message and wait for a reply. If you experience any of the following, this is a same-hour emergency:
-
Severe, escalating pain behind or around the eye, particularly pain out of proportion to what you were told to expect
-
Any change in vision — blurring, dimming, loss of part of the visual field
-
The eye feeling pushed forward, or a marked increase in firmness and tightness
-
Pain on moving the eye, or new double vision
-
Rapidly increasing tightness and swelling on one side only
Later-onset bleeds have been documented more than a week after surgery, so the instruction stands for the whole recovery period. Our guidance on when to seek medical attention after eyelid surgery covers this in more detail — but the five signs above are the ones to memorise.
Complications by Category
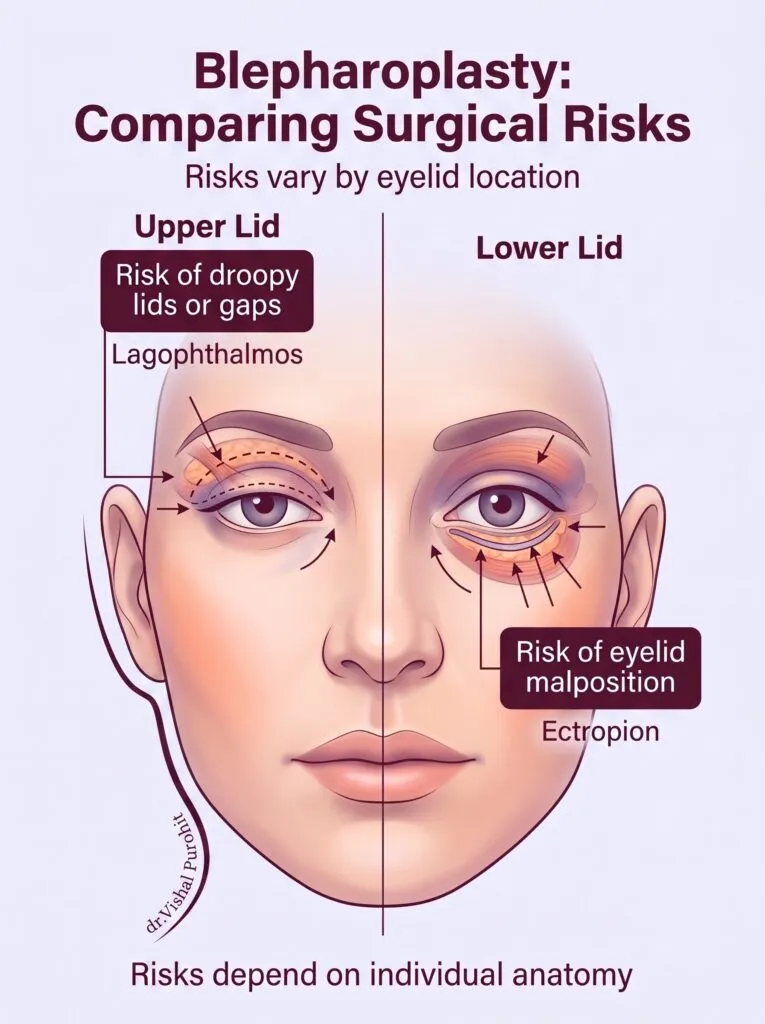
Upper and lower blepharoplasty carry meaningfully different risk profiles. Grouping them together, as most patient literature does, obscures the point.
The frequency column reflects published series and is not a prediction for any individual. Your own risk depends on your anatomy, your health, and what is being done.
Note what is absent from this table. Seroma — a pocket of clear fluid under the skin — is a complication of operations that create dead space, such as abdominoplasty. Eyelid skin lies directly on muscle with no such space, and seroma is not a recognised blepharoplasty complication. If you find it listed on a clinic website, that page was written by someone working from a generic complications list.
Who Should Not Have This Surgery, or Not Yet
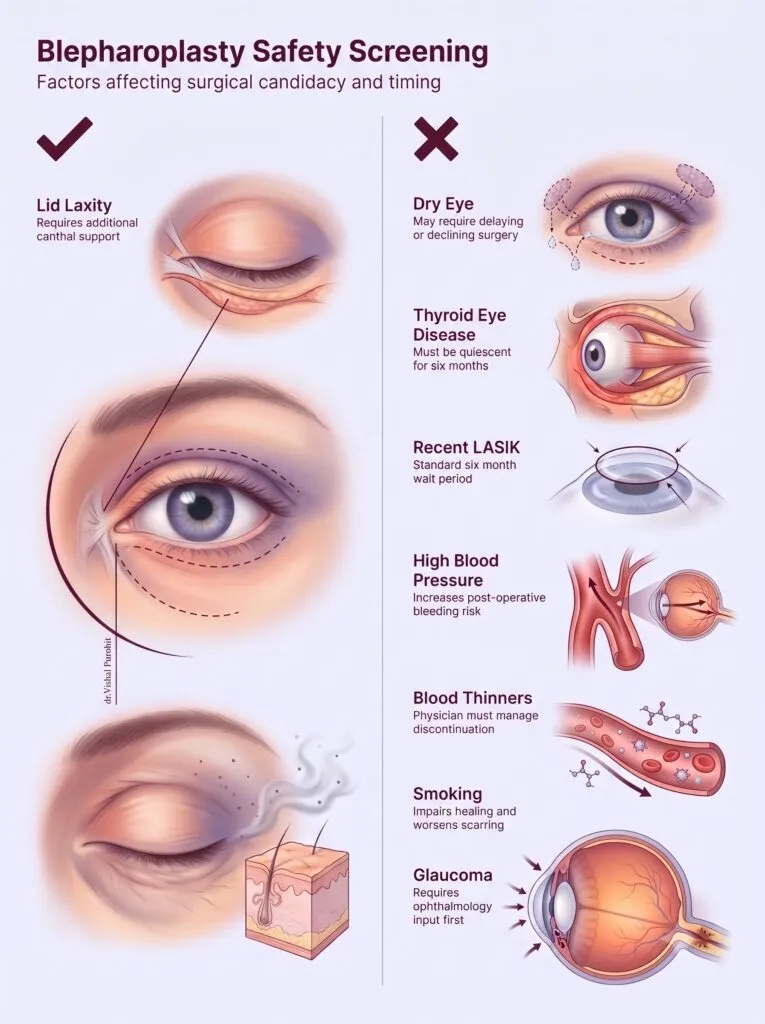
Risk reduction happens in the consultation room far more than in the operating theatre. Several conditions make blepharoplasty inadvisable, or require it to be modified or delayed:
-
Significant dry eye or Sjögren’s syndrome. Surgery reliably makes an already fragile tear film worse. This needs ophthalmological assessment first, and sometimes means declining surgery.
-
Thyroid eye disease. Active disease must be quiescent, typically for at least six months, before any elective eyelid surgery. Proptosis also alters what is technically achievable.
-
Recent LASIK or other corneal refractive surgery. Corneal nerve sensation is reduced afterwards and tear production suffers. A wait of around six months is standard practice.
-
Lower lid laxity or a negative vector midface. A prominent eye with a recessed cheek is the classic setup for post-operative lid malposition. It does not preclude surgery, but it mandates canthal support.
-
Uncontrolled hypertension. A direct contributor to post-operative bleeding.
-
Anticoagulants, antiplatelet agents, and supplements. Aspirin, clopidogrel, warfarin, DOACs — and also fish oil, vitamin E, ginkgo, garlic, and ginseng. Stopping prescribed anticoagulants is a decision for your physician, not your surgeon acting alone.
-
Smoking. Impairs healing and worsens scarring.
-
Glaucoma, previous eye surgery, or a history of retinal detachment. All require ophthalmology input before proceeding.
Anaesthesia carries its own small risk profile, which will be discussed separately with the anaesthetist. Most upper blepharoplasty is performed under local anaesthesia with or without sedation; lower lid and combined procedures more often use general anaesthesia.
Understanding the underlying facial anatomy helps explain why these factors matter so much.
Scarring: A Realistic Account
Upper eyelid incisions are placed within the natural crease, where they are genuinely difficult to detect once mature. Lower lid incisions are either just beneath the lash line or hidden entirely on the inner surface of the lid (the transconjunctival approach), which leaves no external scar at all.
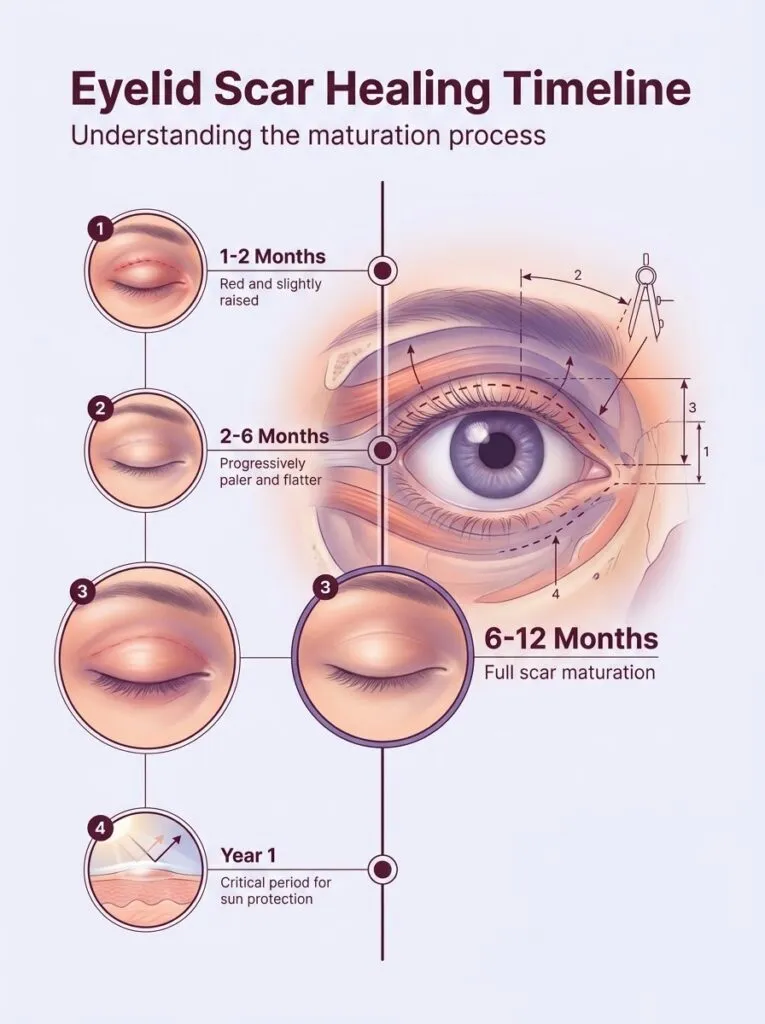
Scars do not, however, look good at six weeks. The sequence is: red and slightly raised for the first one to two months, then progressively paler and flatter. Full scar maturation takes 6 to 12 months. Judging your result before that is judging an unfinished process.
Lateral extensions beyond the orbital rim — needed when there is substantial skin excess — are the portion most likely to remain faintly visible. Patients with deeper skin tones have a somewhat higher tendency towards post-inflammatory pigmentation along the incision, which is manageable but worth anticipating and discussing before surgery.
Sun protection during the first year has more effect on the final appearance than anything applied in the first month.
Recovery: A Realistic Timeline
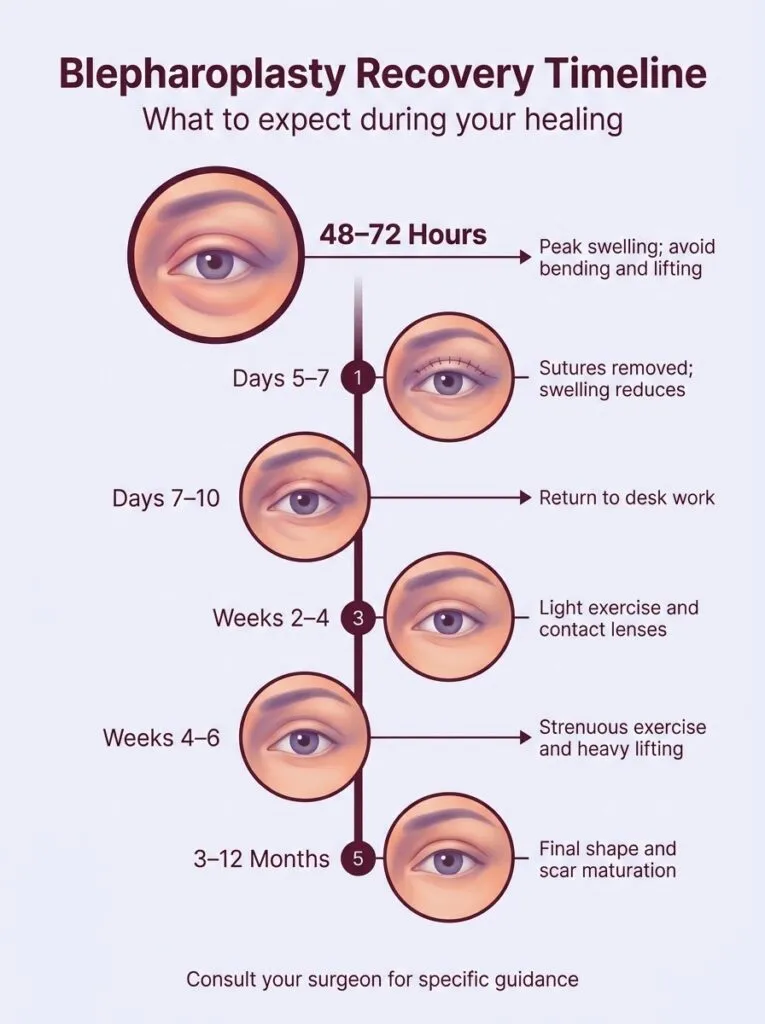
Throughout the first two weeks: avoid aspirin and NSAIDs unless your surgeon specifically approves them, avoid alcohol, do not rub the eyes, and take anti-nausea medication seriously if you feel sick — vomiting spikes venous pressure at exactly the wrong moment.
Frequently Asked Questions
What are the recognized clinical risks associated with blepharoplasty?
Recognized risks include temporary dry eyes (10-15%), bruising, swelling, minor asymmetry, and rare lagophthalmos (temporary difficulty fully closing lids during early edema), documented by Dr. Vishal Purohit in Jaipur. Serious complications like retrobulbar hematoma or infection remain below 0.1% in accredited surgical facilities. As a board-certified plastic surgeon, Dr. Purohit employs meticulous bipolar hemostasis to guarantee patient safety.
How is lagophthalmos (inability to close eyes) prevented during surgery?
Dr. Vishal Purohit in Jaipur prevents lagophthalmos by performing precise pre-operative pinch caliper tests while the patient is awake, ensuring at least 20 mm of functional eyelid skin remains to guarantee complete, effortless eyelid closure. Preserving the orbicularis oculi muscle prevents lid retraction. Dr. Purohit’s conservative resection principles maintain corneal protection permanently.
How does Dr. Vishal Purohit manage post-operative dry eyes?
Post-operative dry eyes are managed proactively with preservative-free carboxymethylcellulose drops during daytime, nocturnal ophthalmic lubricating gels, and moisture-chamber eye shields prescribed by Dr. Vishal Purohit in Jaipur. Normal tear film dynamics regenerate fully as eyelid swelling subsides over 2 to 4 weeks. As an M.Ch. plastic surgeon, Dr. Purohit monitors corneal surface health at all post-op visits.
What surgical safety standards are maintained at Kalpana Aesthetics?
Blepharoplasty is performed under high-magnification surgical loupes in certified, sterile operating theaters using micro-instruments and dedicated local anesthesia with conscious sedation by Dr. Vishal Purohit in Jaipur. Prophylactic ocular protection shields safeguard the globes throughout surgery. Dr. Purohit provides 24/7 direct clinical emergency coverage for complete peace of mind.
References
-
Hass AN, Penne RB, Stefanyszyn MA, Flanagan JC. Incidence of postblepharoplasty orbital hemorrhage and associated visual loss. Ophthalmic Plast Reconstr Surg. 2004;20(6):426–432. doi:10.1097/01.iop.0000143711.48389.c5
-
Prischmann J, Sufyan A, Ting JY, Ruffin C, Perkins SW. Dry eye symptoms and chemosis following blepharoplasty: a 10-year retrospective review of 892 cases in a single-surgeon series. JAMA Facial Plast Surg. 2013;15(1):39–46. doi:10.1001/2013.jamafacial.1
-
Ayintap E, Aytogan H. Comparison of eyelid contour symmetry after ptosis repair via centralized versus temporally biased levator suturing techniques. BMC Ophthalmol. 2025;25:486. doi:10.1186/s12886-025-04318-y
-
Mejia JD, Egro FM, Nahai F. Visual loss after blepharoplasty: incidence, management, and preventive measures. Aesthet Surg J. 2011;31(1):21–29.
-
Codner MA, Wolfli JN, Anzarut A. Primary transcutaneous lower blepharoplasty with routine lateral canthal support: a comprehensive 10-year review. Plast Reconstr Surg. 2008;121(1):241–250.
-
Korn BS, Kikkawa DO, Schanzlin DJ. Blepharoplasty in the post-laser in situ keratomileusis patient: preoperative considerations to avoid dry eye syndrome. Plast Reconstr Surg. 2007;119(7):2232–2239.
About the author. Dr. Vishal Purohit is a plastic and cosmetic surgeon practising in Jaipur at Kalpana Aesthetics.
Medical disclaimer. This article is for general information and does not constitute medical advice. Complication rates cited are drawn from published surgical literature and describe populations, not individuals; your own risk depends on your anatomy, medical history, and the specific procedure planned. Always discuss your case with a qualified surgeon before making any decision about surgery.
To discuss your suitability for eyelid surgery, contact Dr. Vishal Purohit in Jaipur at +91-7718183535.
Expert Blepharoplasty & Eyelid Rejuvenation in Jaipur
Are heavy, drooping upper eyelids or prominent under-eye bags making you look tired, aged, or obstructing your visual field? Schedule a detailed periorbital examination with Dr. Vishal Purohit, board-certified M.Ch plastic surgeon in Jaipur.
- Comprehensive Master Guide: Explore our foundational clinical overview on What is Blepharoplasty? Eyelid Surgery Explained.
- Surgical Procedures & Consultations: Visit our specialized Blepharoplasty Surgery in Jaipur suite to review surgical approaches, recovery milestones, and book your clinical evaluation.