
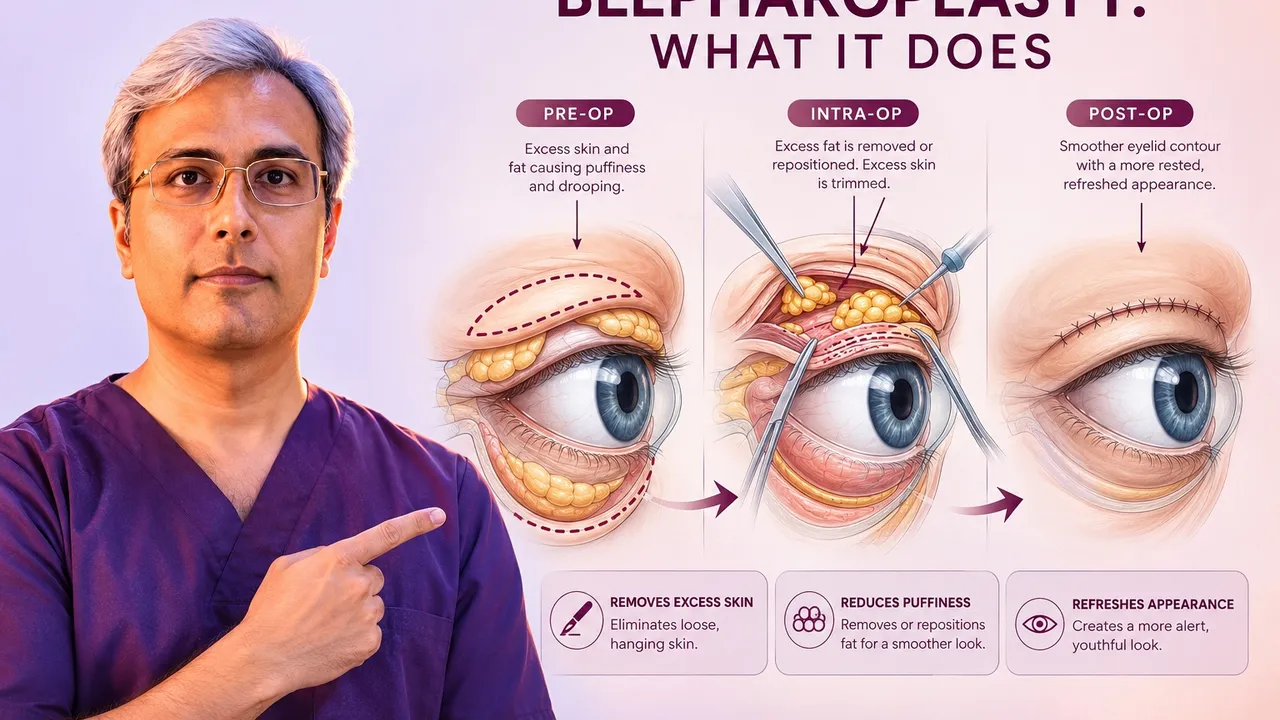
Blepharoplasty is surgery on the eyelids. It can address heaviness in the upper lids that shadows your vision, and it can soften the bags and hollows that make the lower lids look tired.
But “eyelid surgery” is really two different operations. Upper blepharoplasty and lower blepharoplasty involve different tissue planes, different incisions, different risks, and different recoveries. Most of the confusion I see in consultation comes from the two being discussed as one procedure.
This article walks through the anatomy underneath both, so that when we sit down together you already know what the terms mean.
Considering eyelid surgery in Jaipur? Call +91-7718183535 to arrange a consultation, or read the full guide to blepharoplasty first.
First: droopy skin and a droopy lid are not the same problem
This distinction decides which operation you actually need, so it comes before anything else.
Dermatochalasis is excess upper eyelid skin. As skin loses elasticity, it folds down over the lash line, and in advanced cases it obstructs the upper part of your visual field. The lid margin itself sits where it should. Removing the redundant skin — a blepharoplasty — corrects it.
Ptosis is a low-sitting lid margin. Here the levator aponeurosis, the thin tendon that lifts the upper lid, has stretched or detached from the tarsal plate. The problem is the lifting mechanism, not the skin. Removing skin will not raise the margin; the lid needs the aponeurosis tightened, or in severe cases with poor levator function, suspension to the frontalis muscle.
The two often coexist. A patient can have hooded skin and a low margin, and correcting only the skin leaves them looking half-treated. This is why I measure margin-to-reflex distance and levator function at the first visit rather than simply pinching skin.
Brow position is the third variable. When the brow descends, the upper lid looks heavier than it is. Operating on the lid alone in that situation can pull the brow down further. The periorbital region behaves as one connected unit, and the brow has to be assessed alongside the lid.
Eyelid Structural Anatomy & Surgical Layers
| Anatomic Layer | Anatomic Structures | Functional Role | Surgical Relevance in Blepharoplasty |
|---|---|---|---|
| Anterior Lamella | Skin & Orbicularis Oculi Muscle | Blink reflex and active eye closure | Conservative skin excision prevents lagophthalmos |
| Middle Lamella | Orbital Septum & Preaponeurotic Fat | Fibrous retaining barrier for orbital fat | Incised to access, debulk, or transpose fat pads |
| Deep Retractors | Levator Aponeurosis & Müller’s Muscle | Elevates upper lid to open eye | Preserved or tightened during concurrent ptosis repair |
| Posterior Lamella | Tarsal Plate & Palpebral Conjunctiva | Structural skeleton & smooth mucosal lining | Protected to prevent lid distortion or corneal irritation |
The structures that matter
The tarsal plate
Each eyelid contains a plate of dense fibrous tissue — not cartilage, though it feels like it — that gives the lid its shape and stiffness. The upper tarsus is taller, roughly 10 mm at its centre; the lower is about 4 mm. It is the scaffold the lash line hangs from, and the anchor point for the levator aponeurosis above and the lower lid retractors below.
Preserving the tarsus is non-negotiable. Almost every technical decision in eyelid surgery is made around it.
The canthal tendons
The tarsal plate gives the lid rigidity, but it does not hold the lid in position. That job belongs to the medial and lateral canthal tendons, which anchor each end of the lid to the orbital rim.
The lateral canthal tendon is the one that matters most in lower blepharoplasty. If it has loosened with age, the lower lid loses its snap against the globe. Operate on a lax lid without addressing that laxity and you invite the lid to drift downward afterwards — scleral show, or in the worst case ectropion. Testing canthal laxity before surgery is more predictive of a good outcome than almost anything else I check.
Where laxity is present, the tendon is reinforced or repositioned — a canthopexy or canthoplasty — as part of the same operation.
The orbicularis oculi
This is the sphincter muscle that closes the eye. It runs in concentric bands around the orbit and is responsible for blinking, for the pump that moves tears toward the drainage system, and for protecting the cornea.
In lower lid surgery the muscle is often lifted, redraped and re-fixed rather than simply removed, because its tone contributes to lid support. Over-resection weakens closure and worsens dry eye.
The orbital septum and the fat pads
Behind the orbicularis lies the orbital septum, a thin fibrous sheet that holds orbital fat inside the socket. With age the septum weakens and the fat bulges forward. That bulge is what you see as under-eye bags — not extra fat, in most cases, but the same fat pushed forward.
The upper lid has two fat pads; the lower lid has three. Below the orbital rim sits a separate cushion, the suborbicularis oculi fat, which contributes to the lid–cheek transition.
The lid–cheek junction
The tear trough and the hollow beside it are largely a matter of where the orbital rim ligaments tether skin down. Understanding this is why modern lower blepharoplasty often repositions fat rather than removing it — more on that below.
Upper blepharoplasty
The incision
The incision sits in the natural upper lid crease. Once healed, it is hidden when the eye is open, and visible only as a fine line when the eye is closed.
The critical decision is how much skin to leave, not how much to take. A minimum of about 20 mm of skin between the brow and the lash line is needed for the lid to close comfortably. Take more than that and the patient is left unable to shut the eye fully — a difficult problem to reverse. I would rather leave a patient slightly under-corrected and revise later.
What is removed, and what is kept
Skin is the main target. A strip of orbicularis may be taken if the lid is very full. Fat is treated conservatively: the medial pad is often the only one that genuinely needs reducing, and aggressive upper lid fat removal is a common cause of the hollow, skeletonised look that reads as “operated on” rather than rested.
If the levator aponeurosis has stretched, it is repaired through the same incision at the same sitting.
Lower blepharoplasty
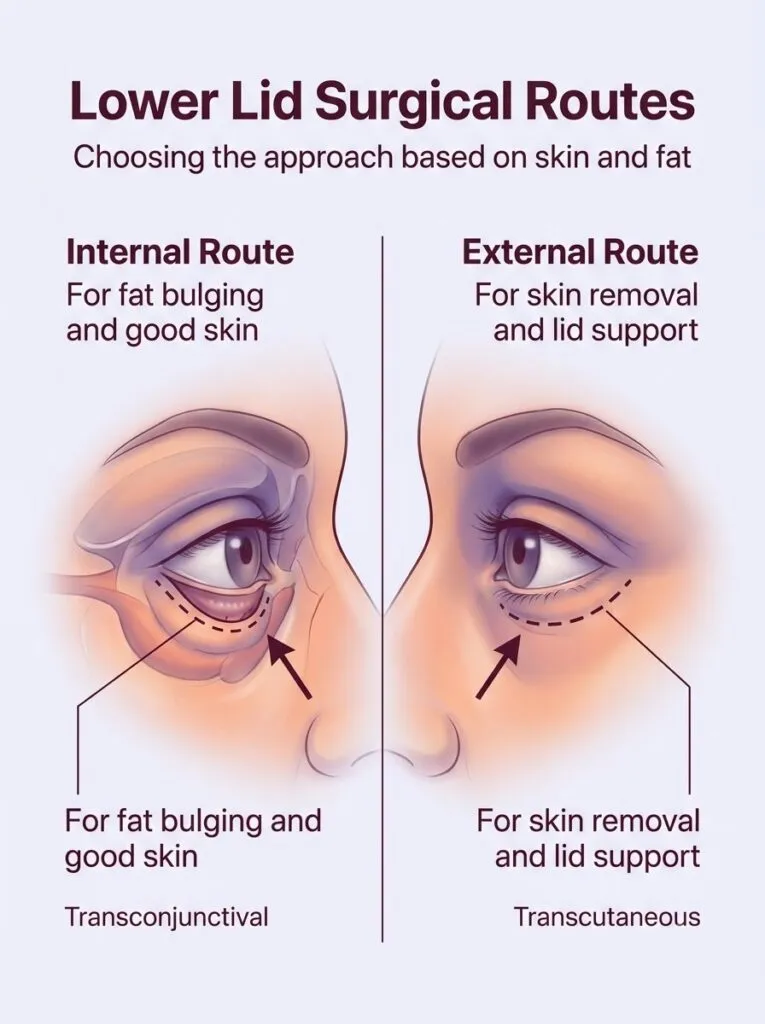
Two routes in
Transconjunctival — the incision is made on the inside of the lower lid. There is no external scar, and because the orbicularis and its supporting structures are left undisturbed, the risk of the lid pulling downward afterwards is lower. It suits patients whose main issue is fat bulging with good skin quality.
Transcutaneous — a subciliary incision just below the lash line, which allows excess skin to be removed as well as fat addressed. It is the route for patients with genuine skin redundancy, and it is usually combined with canthal support.
Neither is universally better. The choice follows the anatomy.
Repositioning rather than removing fat
The older approach was to excise the bulging fat. It flattened the bag but often left a hollow above the cheek, because the fat was doing volumetric work as well as causing the bulge.
The alternative is to release the tethering at the orbital rim and redrape that same fat downward over the rim, filling the tear trough with it. Combined with attention to the lid–cheek junction, this produces a smoother transition than excision alone.
Not everyone is a candidate. Where volume loss dominates, fat grafting or filler may serve better than repositioning.
How much skin can safely come off
Very little, if the lid is not supported. Traditional teaching limits subciliary skin excision to roughly 2–4 mm precisely because over-resection is the classic route to ectropion.
More can be taken safely, but only when the suspension system is deliberately reinforced. In a ten-year series of extended lower blepharoplasty with canthoplasty and muscle fixation, an average of 10 mm was excised with one case of ectropion across 93 patients. The lesson is not “more skin is fine” — it is that skin excision and lid support are a single decision, not two.
What I assess before agreeing to operate
This is the part of the process that most determines the result, and the part patients hear least about.
-
Dry eye history and tear film. Blepharoplasty transiently worsens dry eye. A patient with pre-existing dryness, or a history of LASIK, needs that established and managed first.
-
Canthal laxity. Snap-back and lid distraction testing. Laxity changes the operative plan.
-
Margin-to-reflex distance and levator function. To separate ptosis from dermatochalasis, as above.
-
Brow position. Assessed with the patient’s brow at rest, not raised.
-
Globe position and vector. In a negative vector face — where the eye sits forward of the cheek — the lower lid is inherently less well supported and standard techniques carry more risk.
-
Thyroid status. Undiagnosed thyroid eye disease changes everything about the plan.
-
Bleeding risk. Anticoagulants, antiplatelets, and supplements that affect clotting.
-
Photographs and asymmetry mapping. Almost everyone is asymmetric before surgery. Documenting it prevents disappointment afterwards.
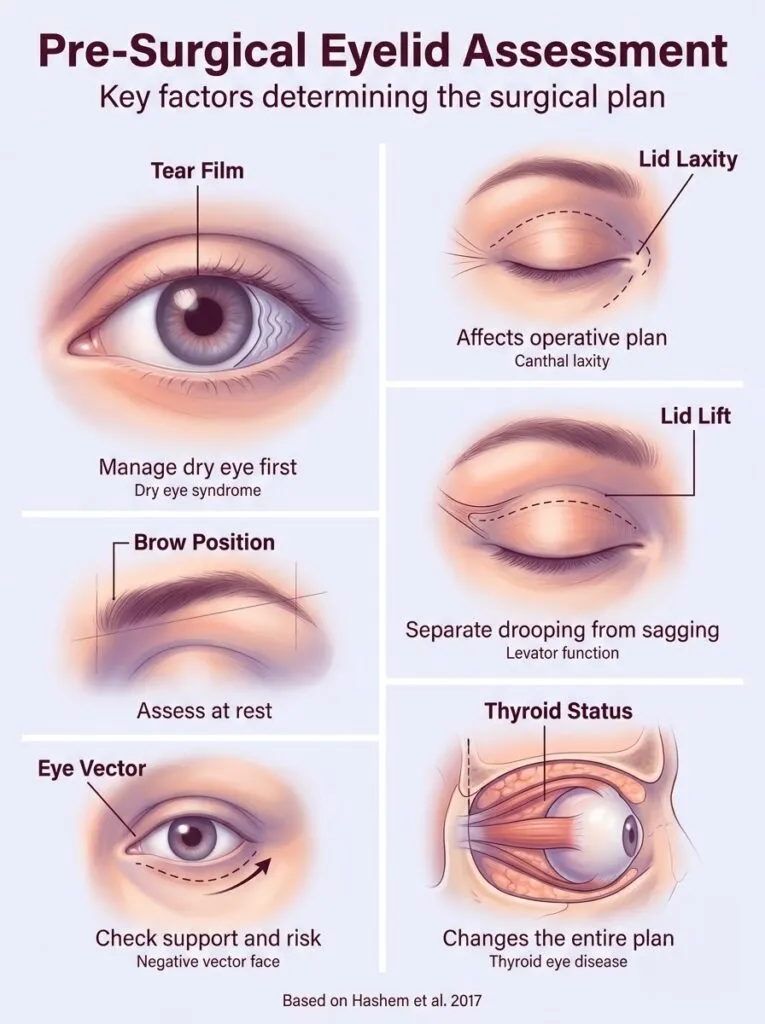
A graded, evidence-based approach to matching technique to findings has been set out in the plastic surgery literature, and it is broadly the framework I work within.
Risks, named honestly
Every operation carries risk. I would rather you read them here than discover them later.
Retrobulbar haemorrhage. Rare, and the reason eyelid surgery is taken seriously. Bleeding behind the globe raises orbital pressure and can threaten vision. It presents in the first hours as increasing pain, proptosis and visual change, and it is a surgical emergency. This is why I give explicit post-operative instructions about what to watch for and how to reach me immediately.
Lower lid malposition. Scleral show, lid retraction or ectropion, usually from over-resection of skin or unrecognised canthal laxity. Often settles with massage and time; sometimes needs revision.
Chemosis. Swelling of the conjunctiva. Common enough after lower lid surgery to be worth expecting, uncomfortable, and self-limiting with treatment.
Dry eye and incomplete closure. Usually temporary. Managed with lubricants. Persistent lagophthalmos after over-aggressive skin removal is the version to avoid.
Asymmetry. Faces are asymmetric to begin with, and healing is not perfectly symmetric either.
Scarring. Upper lid scars usually settle to an inconspicuous line in the crease. Subciliary scars are generally good but take longer to fade.
Under- or over-correction, and the possibility of revision surgery.
There is a fuller discussion in my article on the common risks and safety realities of eyelid procedures.
Recovery: a realistic timeline
-
Day 0–3. Swelling and bruising increase, peaking around 48–72 hours. Cold compresses, head elevated. Vision may be blurred from ointment. Expect to do nothing.
-
Day 4–7. Sutures removed, usually in this window. Swelling starting to turn the corner.
-
Day 7–14. Most patients are comfortable in public with light make-up by around two weeks. Bruising fades to yellow.
-
Week 2–4. Back to desk work and light activity. Screen time may still tire the eyes. No heavy lifting or straining.
-
Week 4–6. Exercise resumed gradually. Scars still pink.
-
Month 3–6. Scars soften and pale. Fine residual swelling settles, particularly in the lower lids.
-
Month 6–12. Final result.
Air travel is usually reasonable after about two weeks, but check with me based on your specific procedure. Contact lens wear typically resumes at two to three weeks.
Results vary considerably between individuals. Upper blepharoplasty results commonly last well over a decade; lower lid fat correction tends to be long-lasting, but neither stops the ageing process — they reset the starting point.
Aesthetic judgement
Technique keeps the eye safe. Judgement decides whether it looks like you.
The goal is not a standard eyelid. Crease height, lid show, and the degree of fullness that suits a face vary with ethnicity, gender, and personal preference, and the operation should follow the face rather than a template. I discuss this at length in defining your aesthetic goals.
Frequently asked questions
Will the scars be visible after blepharoplasyty?
Scars from blepharoplasty performed by Dr. Vishal Purohit are typically well-hidden and become virtually undetectable once fully healed. For upper eyelid surgery, the precise incisions are placed directly within the natural crease of the lid. For lower eyelid surgery, incisions are made either just below the lower lash line or entirely inside the eyelid (the transconjunctival approach). As a board-certified plastic surgeon in Jaipur, Dr. Purohit utilizes meticulous microsurgical techniques to ensure optimal scar healing over the 3-to-6 month maturation period.
How soon can I see and blink normally after eyelid surgery?
You will be able to see and blink normally immediately following eyelid surgery, though your vision may temporarily blur for the first 24 hours due to protective eye ointments. Most of Dr. Vishal Purohit’s patients in Jaipur comfortably resume reading and using screens within 2 to 3 days. While mild swelling during the first week can make the eyelids feel slightly stiff, normal blinking mechanics are completely preserved.
How long do the results of blepharoplasty last?
The cosmetic improvements from blepharoplasty are exceptionally long-lasting, typically enduring for 10 to 15 years for the upper eyelids and often permanently for the lower eyelids. While the surgery permanently removes targeted fat and excess skin, it does not stop the natural aging process. Over time, forehead skin may naturally descend, but the under-eye fat bags removed at Dr. Purohit’s Jaipur clinic rarely return.
When will the puffiness completely go after blepharoplasty?
Yes, the chronic puffiness or under-eye “bags” caused by herniated fat pads are permanently eliminated during lower blepharoplasty. Dr. Vishal Purohit carefully excises or repositions these excess fat deposits to create a smooth, youthful contour. While patients will experience temporary post-surgical swelling for the first 7 to 14 days, this is part of the healing process and completely subsides, revealing a refreshed, bag-free appearance.
Is upper eyelid surgery covered by insurance?
Upper eyelid surgery is generally only covered by health insurance if it is deemed a medical necessity—specifically, if severely drooping eyelid skin (ptosis) obstructs your peripheral vision. If the blepharoplasty is performed purely for cosmetic rejuvenation, insurance providers in India will not cover the cost. During a consultation in Jaipur, Dr. Vishal Purohit can evaluate your eyelids to determine if your case might qualify for functional, reconstructive coverage.
What anaesthesia is used in eyelid surgery?
Blepharoplasty is most frequently performed safely and comfortably under local anesthesia combined with oral or intravenous sedation. This approach numbs the eye area completely while keeping the patient relaxed. If a patient prefers to be completely asleep, or if Dr. Vishal Purohit is combining the eyelid surgery with other facial procedures like a facelift, general anesthesia can be administered in his state-of-the-art Jaipur surgical facility.
About the author
Dr. Vishal Purohit is a plastic, cosmetic and reconstructive surgeon practising in Jaipur, Rajasthan. [Add qualifications, years in practice, hospital affiliations, society memberships and medical council registration number here — this section carries significant weight for both patients and search engines.]
Medically reviewed: 26 July 2026.
Consultation
To discuss whether eyelid surgery is appropriate for you, call +91-7718183535 or visit the clinic in Jaipur.
Expert Blepharoplasty & Eyelid Rejuvenation in Jaipur
Are heavy, drooping upper eyelids or prominent under-eye bags making you look tired, aged, or obstructing your visual field? Schedule a detailed periorbital examination with Dr. Vishal Purohit, board-certified M.Ch plastic surgeon in Jaipur.
- Comprehensive Master Guide: Explore our foundational clinical overview on What is Blepharoplasty? Eyelid Surgery Explained.
- Surgical Procedures & Consultations: Visit our specialized Blepharoplasty Surgery in Jaipur suite to review surgical approaches, recovery milestones, and book your clinical evaluation.