
Most articles about eyelid surgery tell you what it achieves. Far fewer tell you where it stops. That second half matters more, because almost every disappointed patient I meet was disappointed by a gap between what they expected and what the operation was ever able to deliver.
This guide covers both sides honestly: the changes blepharoplasty reliably produces, the concerns it does not address at all, who is and is not a suitable candidate, what the risks are, and how long results actually last.
Dr. Vishal Purohit is a plastic and cosmetic surgeon practising at Kalpana Aesthetics, Jaipur. For a broader overview of the operation itself, see the full guide to blepharoplasty.
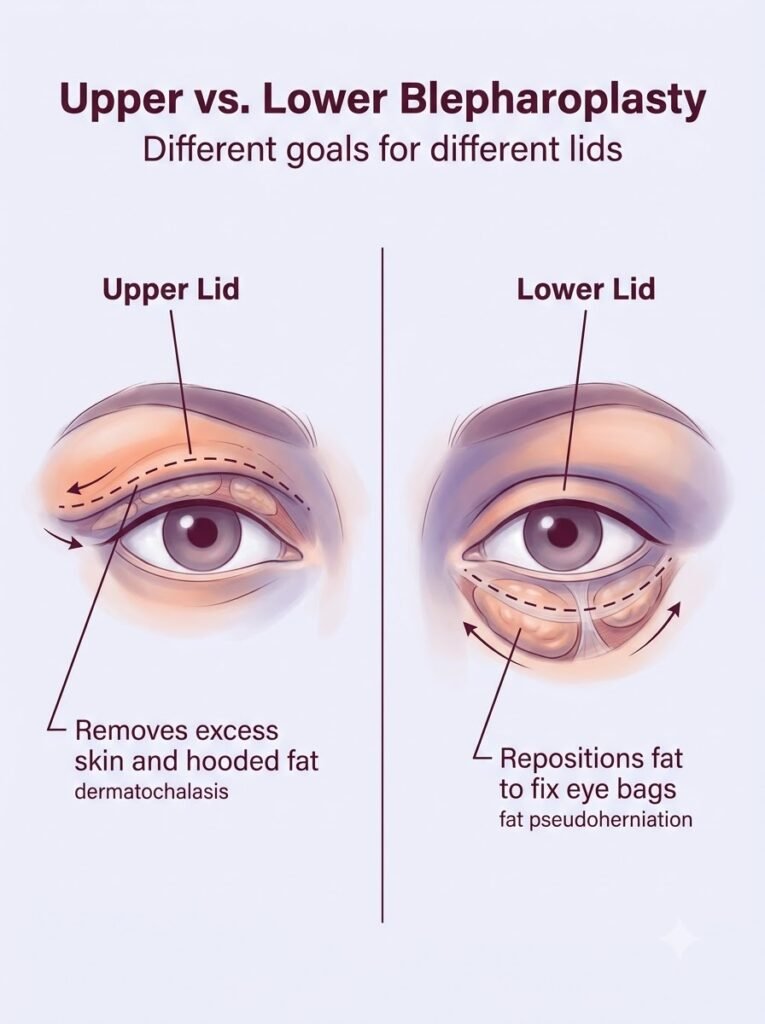
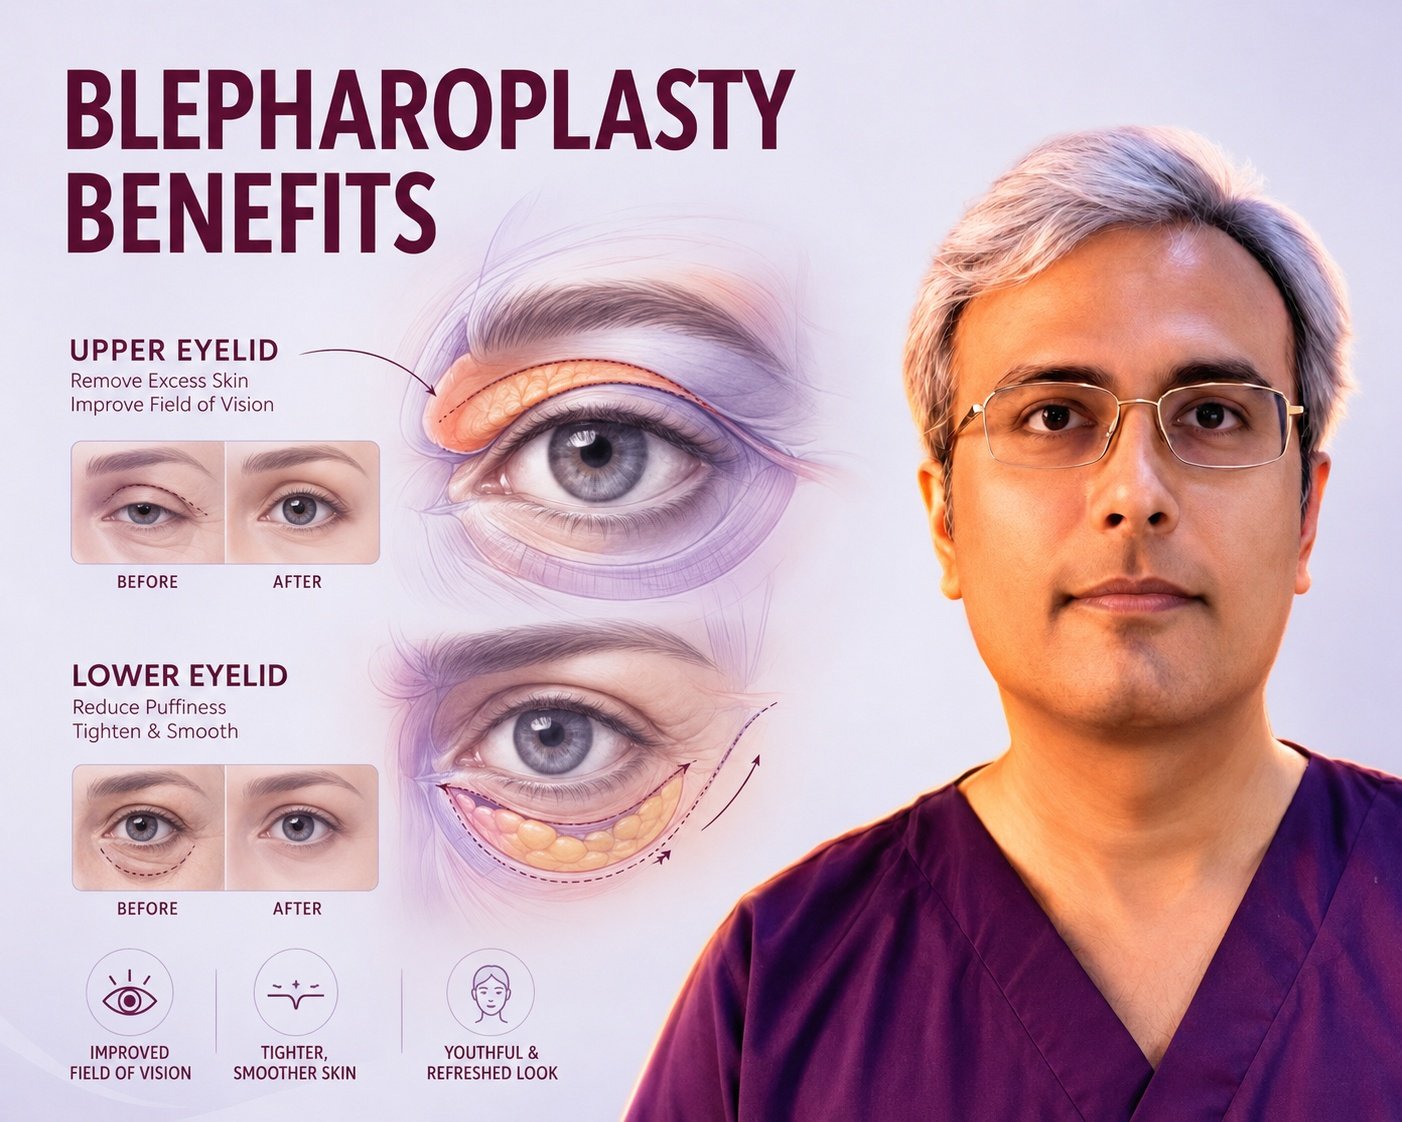
Upper and Lower Blepharoplasty Are Two Different Operations
People often say “eyelid surgery” as though it were one procedure. It is not. The upper and lower lids have different anatomy, different problems, different recovery timelines, and different risk profiles. Confusing the two is the source of most unrealistic expectations.
Upper blepharoplasty
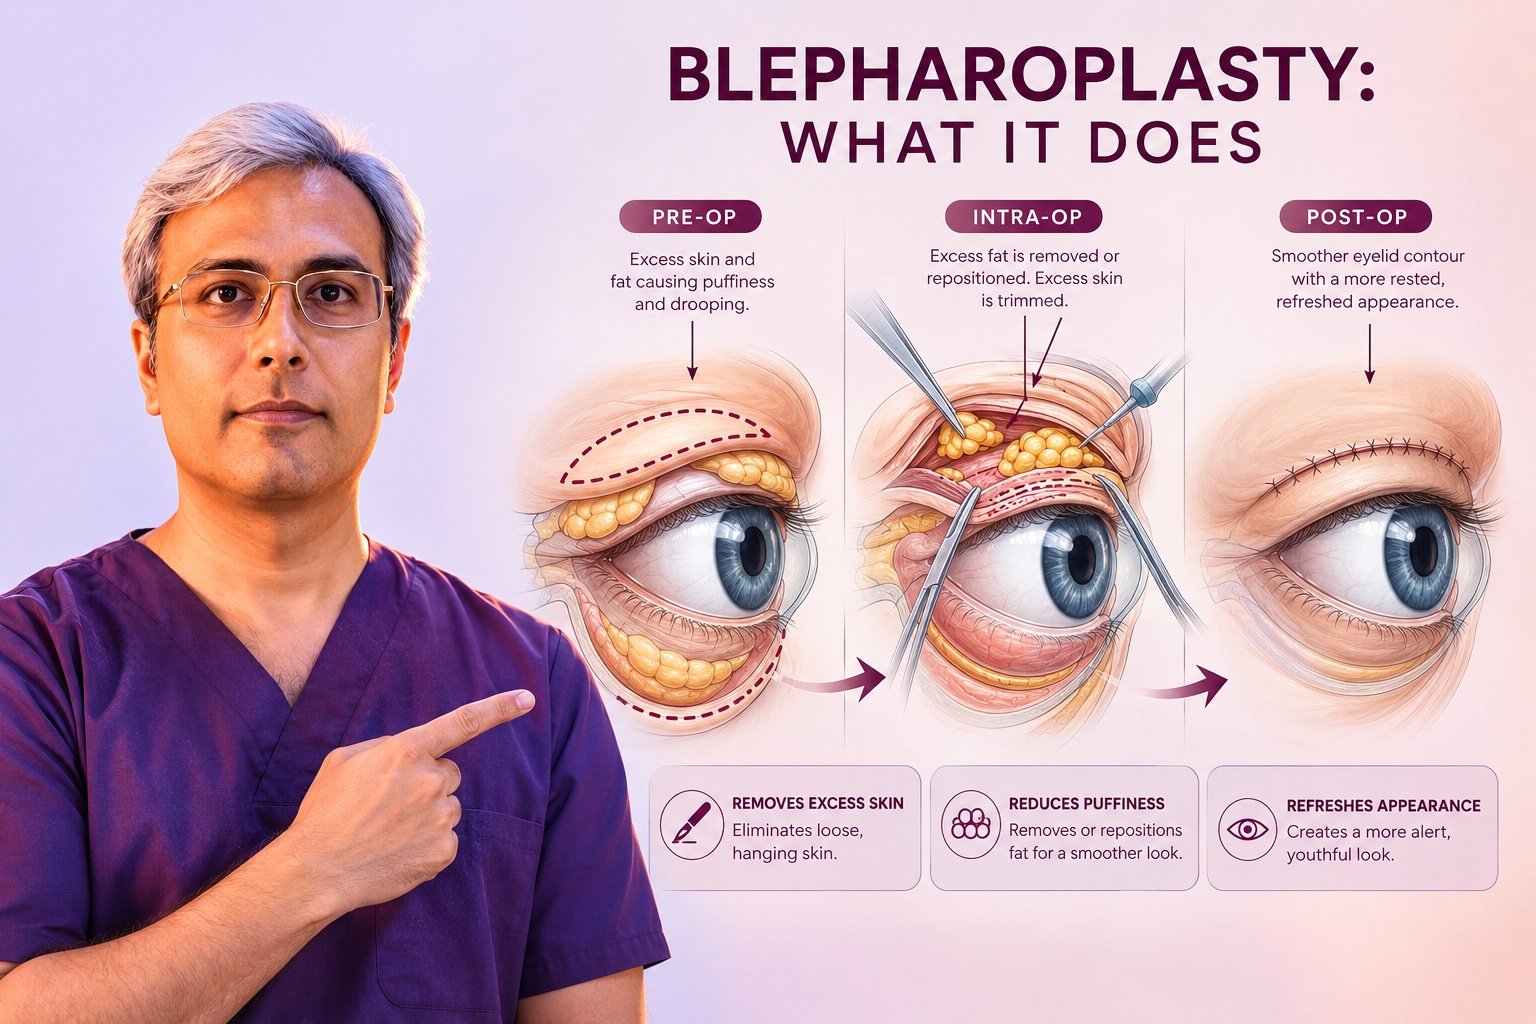
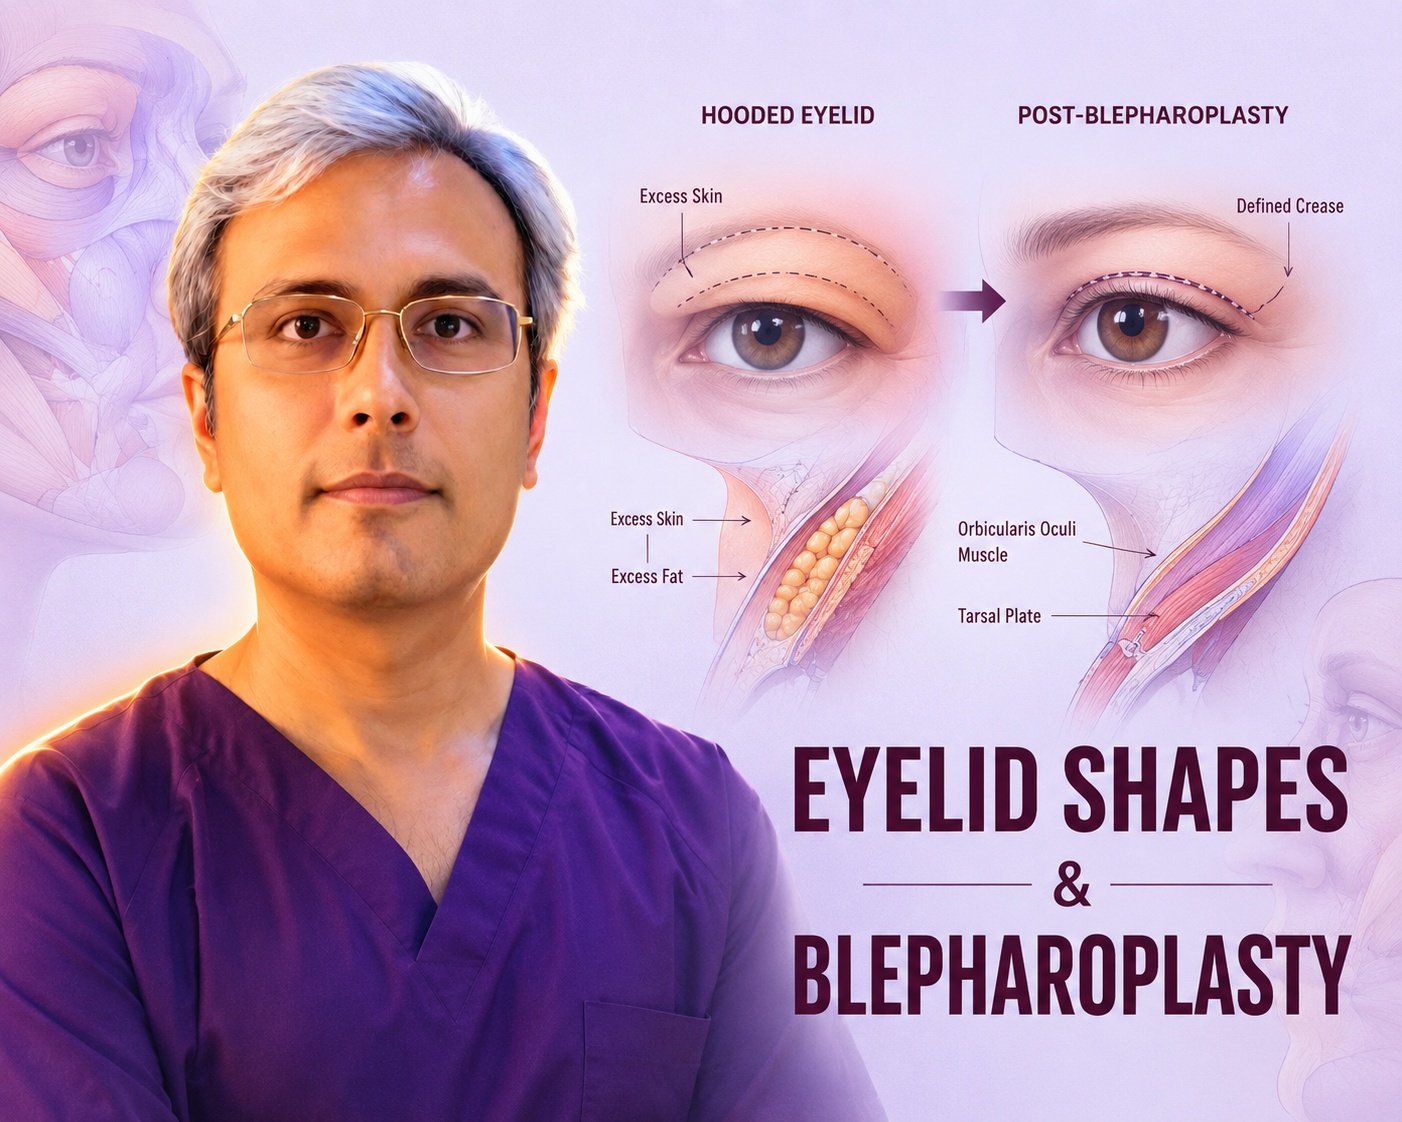
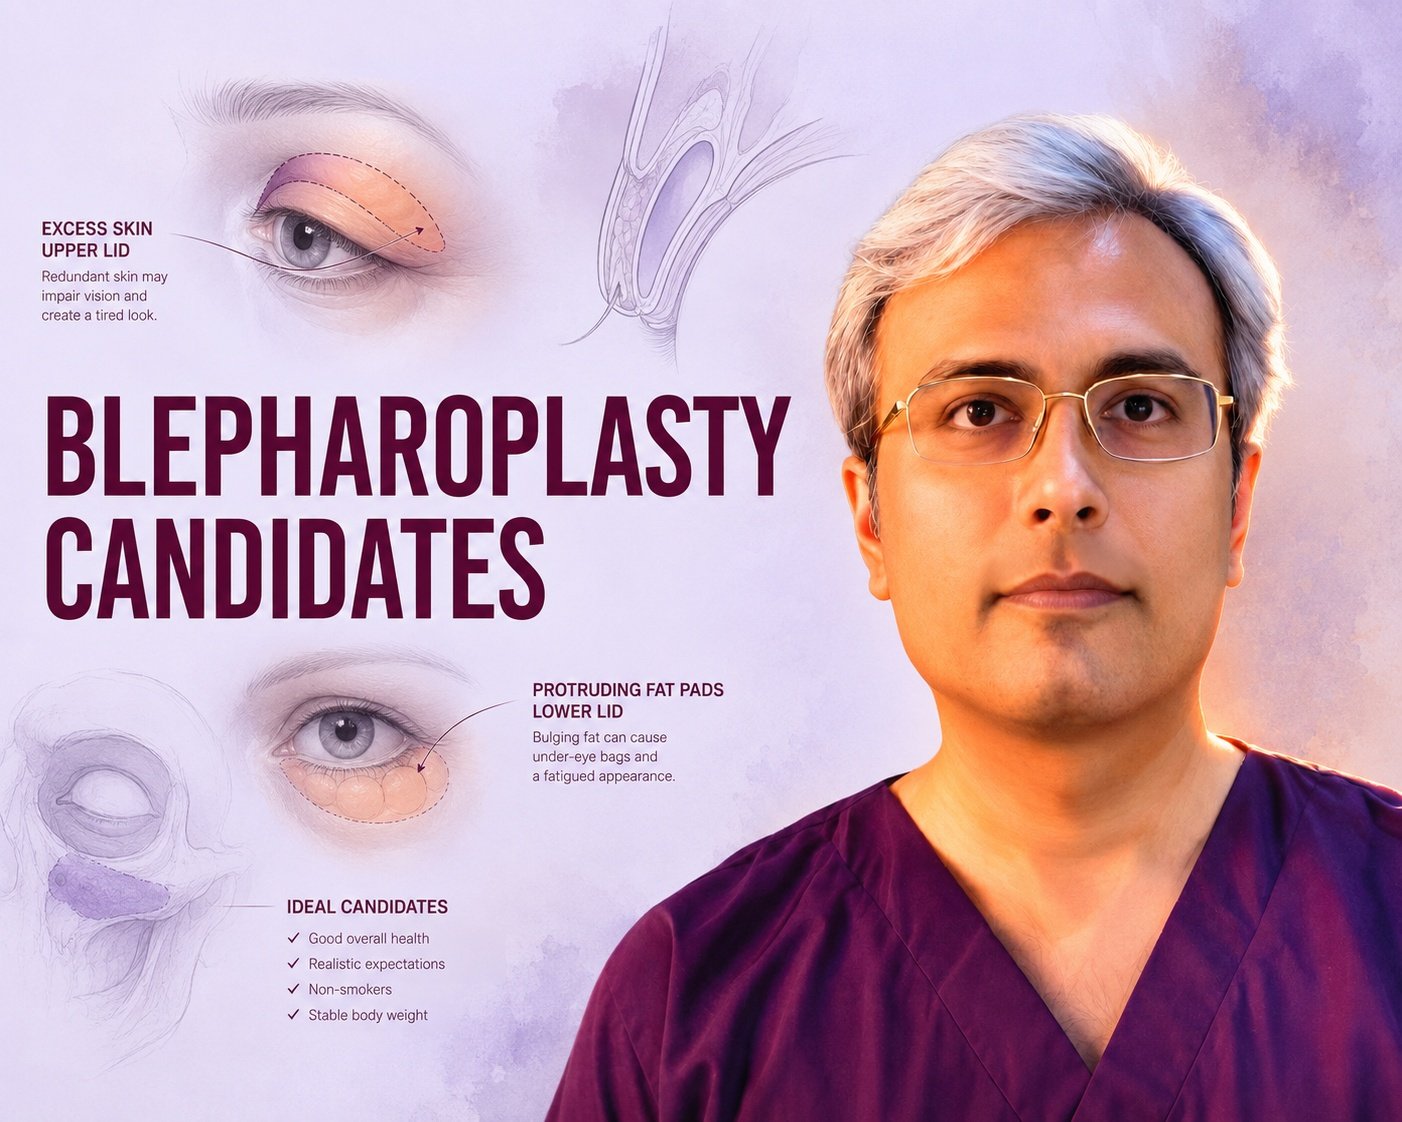
The upper lid problem is usually dermatochalasis — an excess of skin, sometimes with a bulge of prolapsed orbital fat at the inner corner. Skin gathers over the natural crease, the lid looks hooded, and in more advanced cases the excess skin encroaches on the upper field of vision.
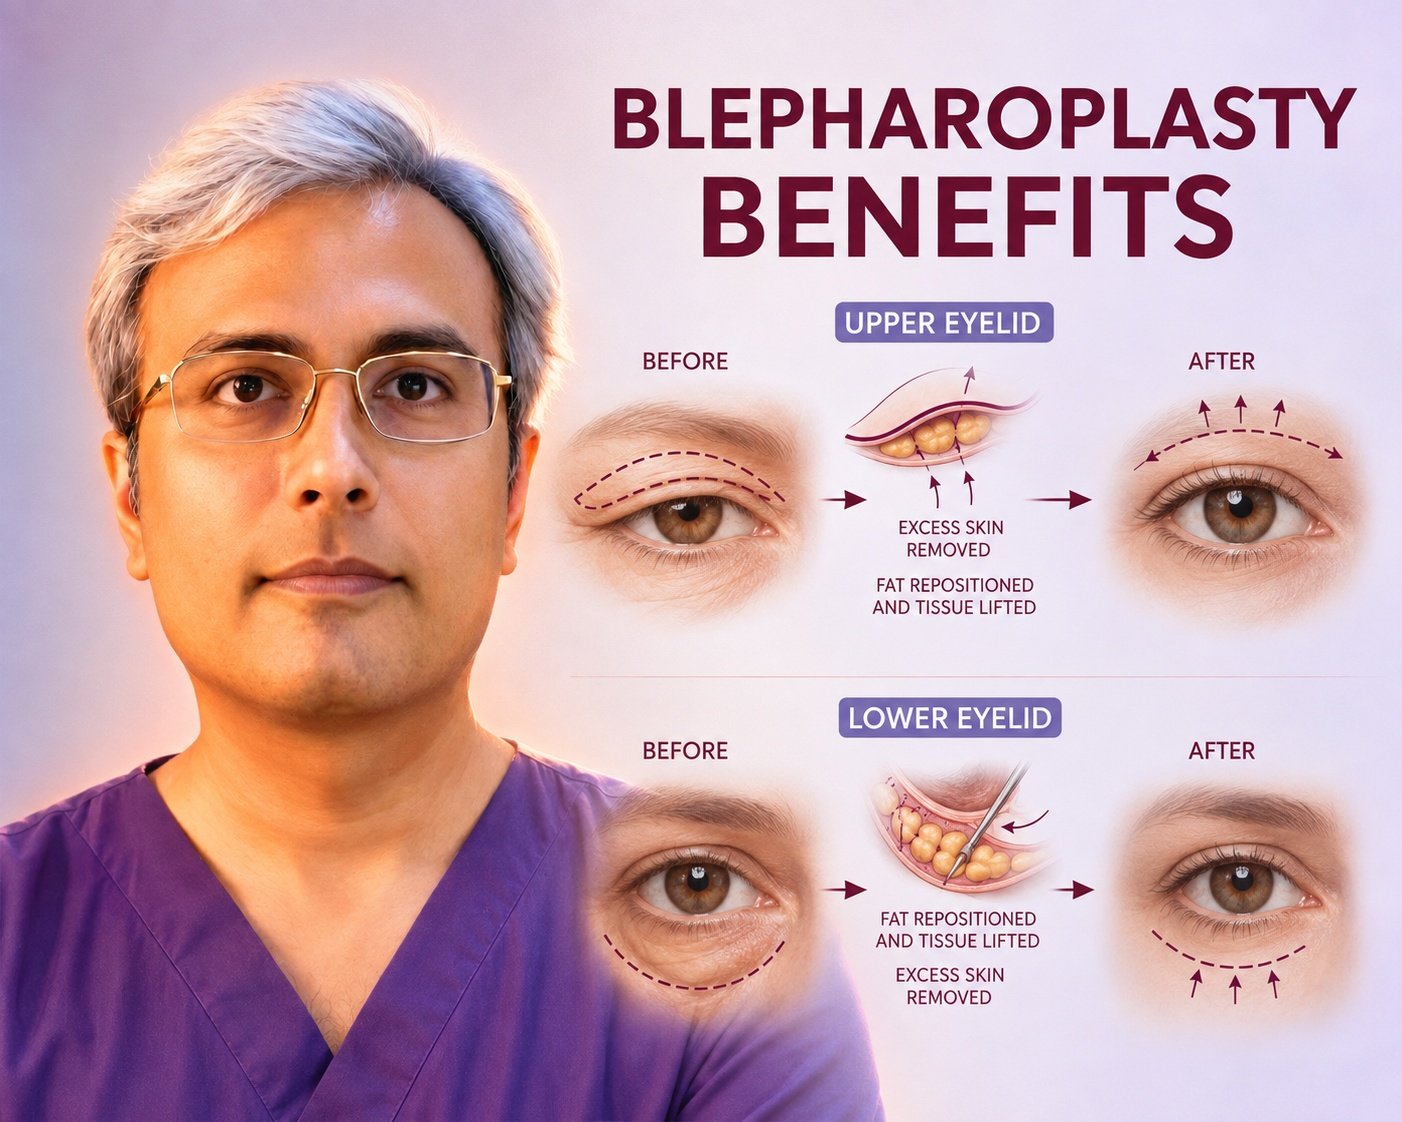
Upper blepharoplasty removes a measured strip of that excess skin, occasionally a sliver of orbicularis muscle, and repositions or reduces herniated fat. The incision sits in the natural crease of the lid.
What it delivers: a cleaner, more defined lid crease, less hooding, an eye that looks open rather than heavy. In many patients, a genuine improvement in the superior visual field.
Lower blepharoplasty
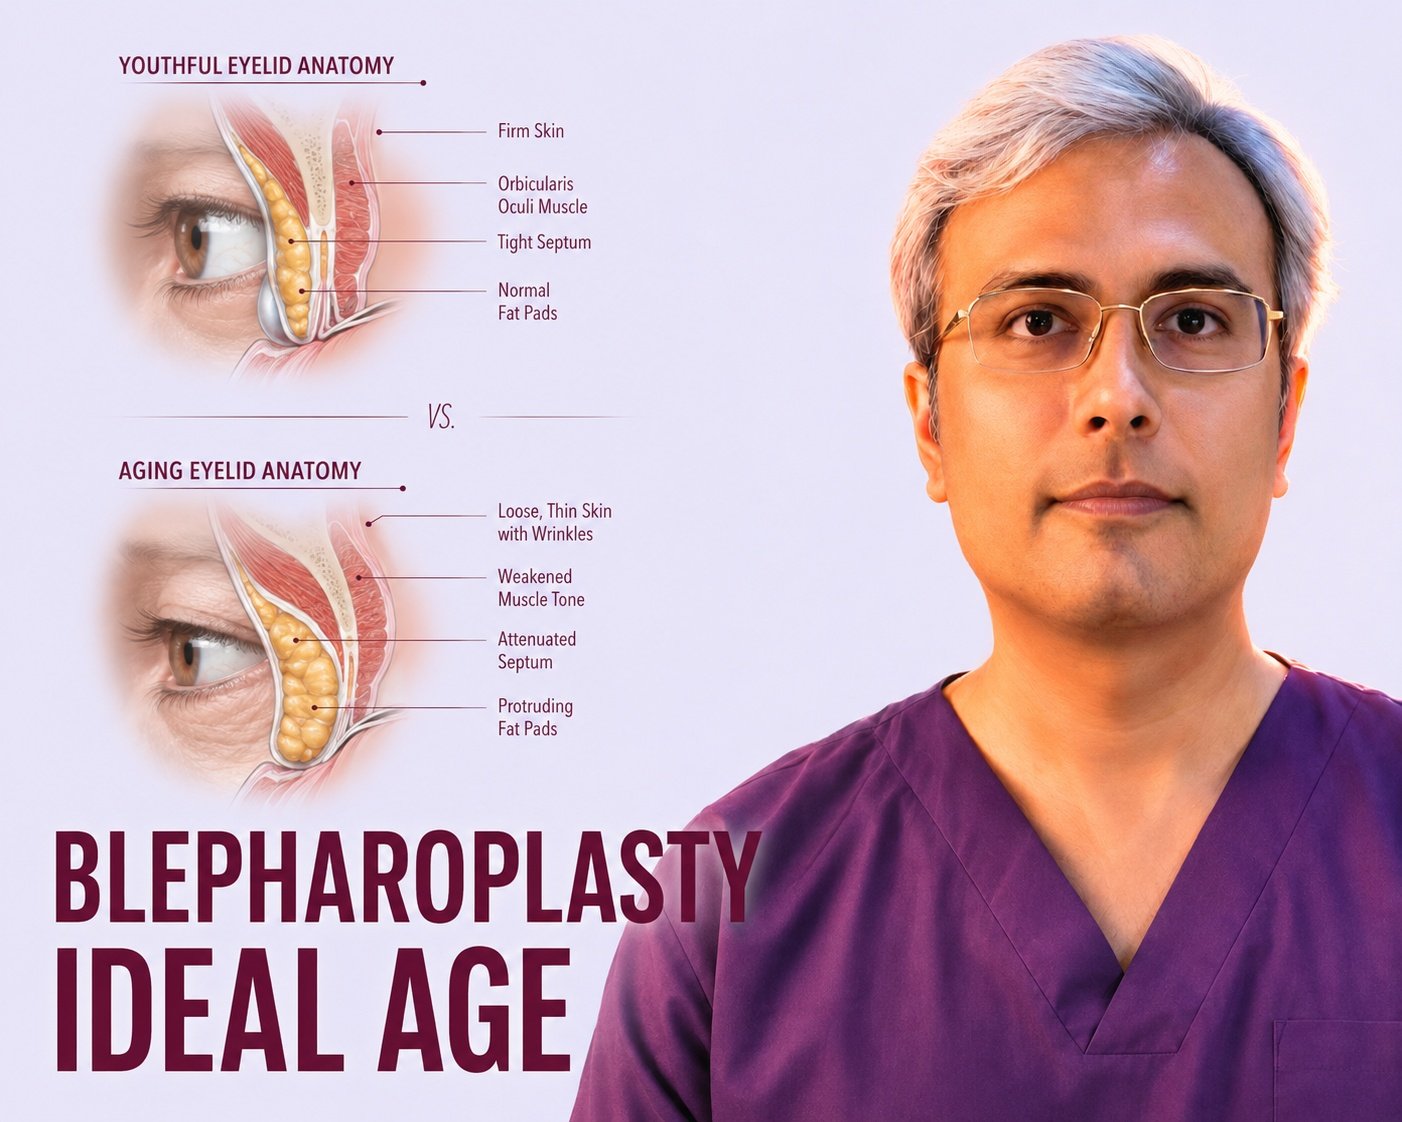
The lower lid problem is usually fat pseudoherniation — the fat pads that cushion the eye push forward against a weakening septum, producing the bulge people call “eye bags.” This is often combined with skin laxity and a hollow at the tear trough.
Modern lower lid surgery increasingly favours repositioning fat over removing it. Fat is released and draped over the orbital rim to soften the step-off between the bag and the hollow below it. Removing fat aggressively is what produces the sunken, skeletal look you have probably seen and disliked.
The approach also varies: a transconjunctival incision hidden inside the lid when the problem is purely fat, or a subciliary incision just under the lash line when skin needs to come out as well.
What Blepharoplasty Cannot Do
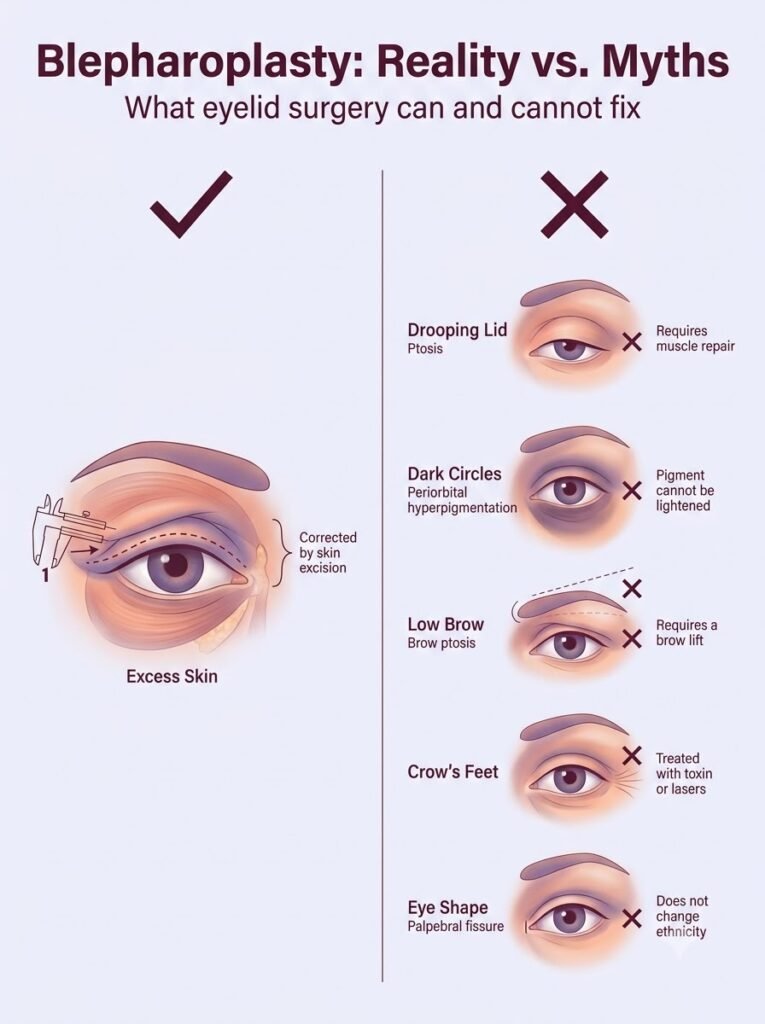
This is the section most articles omit. Each of the following is a common reason for a consultation, and none of them is fixed by eyelid surgery alone.
It does not lift a drooping eyelid caused by ptosis. This is the most important distinction in the whole field. True ptosis — where the lid margin itself sits low over the pupil — is a problem of the levator muscle or its aponeurosis, not of excess skin. It is corrected by levator advancement or a Müller’s muscle–conjunctival resection. A patient with ptosis who receives skin excision alone will have a tidier upper lid and an eye that is still half-closed. The two operations are frequently combined, but they are not the same operation, and the difference is established by measuring lid margin position and levator function at consultation.
It does not fix dark circles. Under-eye darkness is often pigmentation, thin skin showing underlying vasculature, or shadow cast by contour. Surgery can flatten the contour that casts the shadow. It cannot lighten pigment. Patients with true periorbital hyperpigmentation may see very little change.
It does not fix brow ptosis. A descended brow pushes skin down onto the upper lid and mimics eyelid hooding. Operating on the lid in this situation removes skin that was holding the brow up, can worsen the brow position, and produces an unsatisfying result. If the brow is the primary problem, a brow lift is the correct answer — alone or in combination.
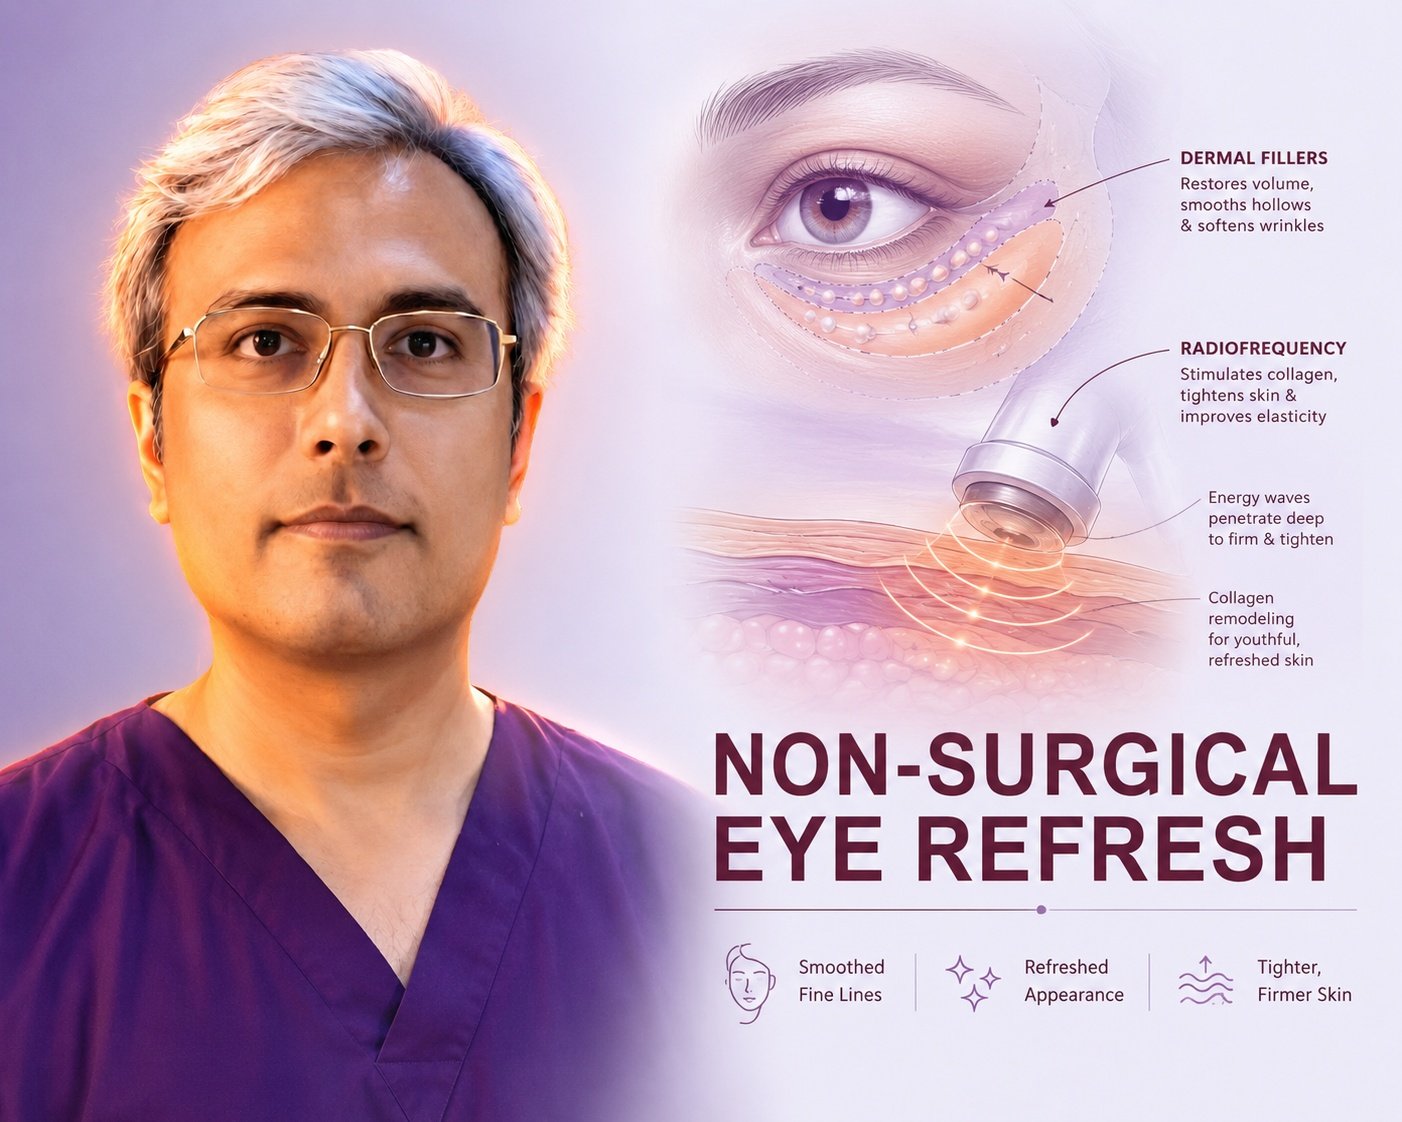
It does not remove crow’s feet or fine wrinkling. Those are dynamic lines from orbicularis activity and skin quality. They are the territory of botulinum toxin, resurfacing, or energy-based treatment.
It does not fully correct festoons or malar mounds. The soft, boggy swellings that sit over the cheekbone, below the orbital rim, are a separate entity with a separate and considerably more difficult treatment. Standard lower blepharoplasty leaves them largely untouched and can occasionally make them more noticeable.
It does not stop ageing. It resets a position. Tissue continues to age from the new starting point.
It does not change eye shape or ethnicity. Altering the palpebral fissure shape or constructing a crease where none exists is a different operation with different aims — and altering a defining feature of a face is a decision that deserves its own separate discussion, not a casual add-on.
Functional Benefits: Real, but Specific
Upper blepharoplasty genuinely improves vision in a specific subgroup: patients whose excess upper lid skin obstructs the superior visual field, demonstrable on formal visual field testing with the lid taped and untaped. Those patients often describe reduced brow-ache too, because they have been unconsciously recruiting the frontalis muscle to lift the lid all day.
If your lids are heavy but your visual field is unobstructed, expect an aesthetic result, not a functional one. Be cautious of any claim that eyelid surgery treats general eye strain, headaches, or fatigue — those have many causes, and the evidence does not support that promise.
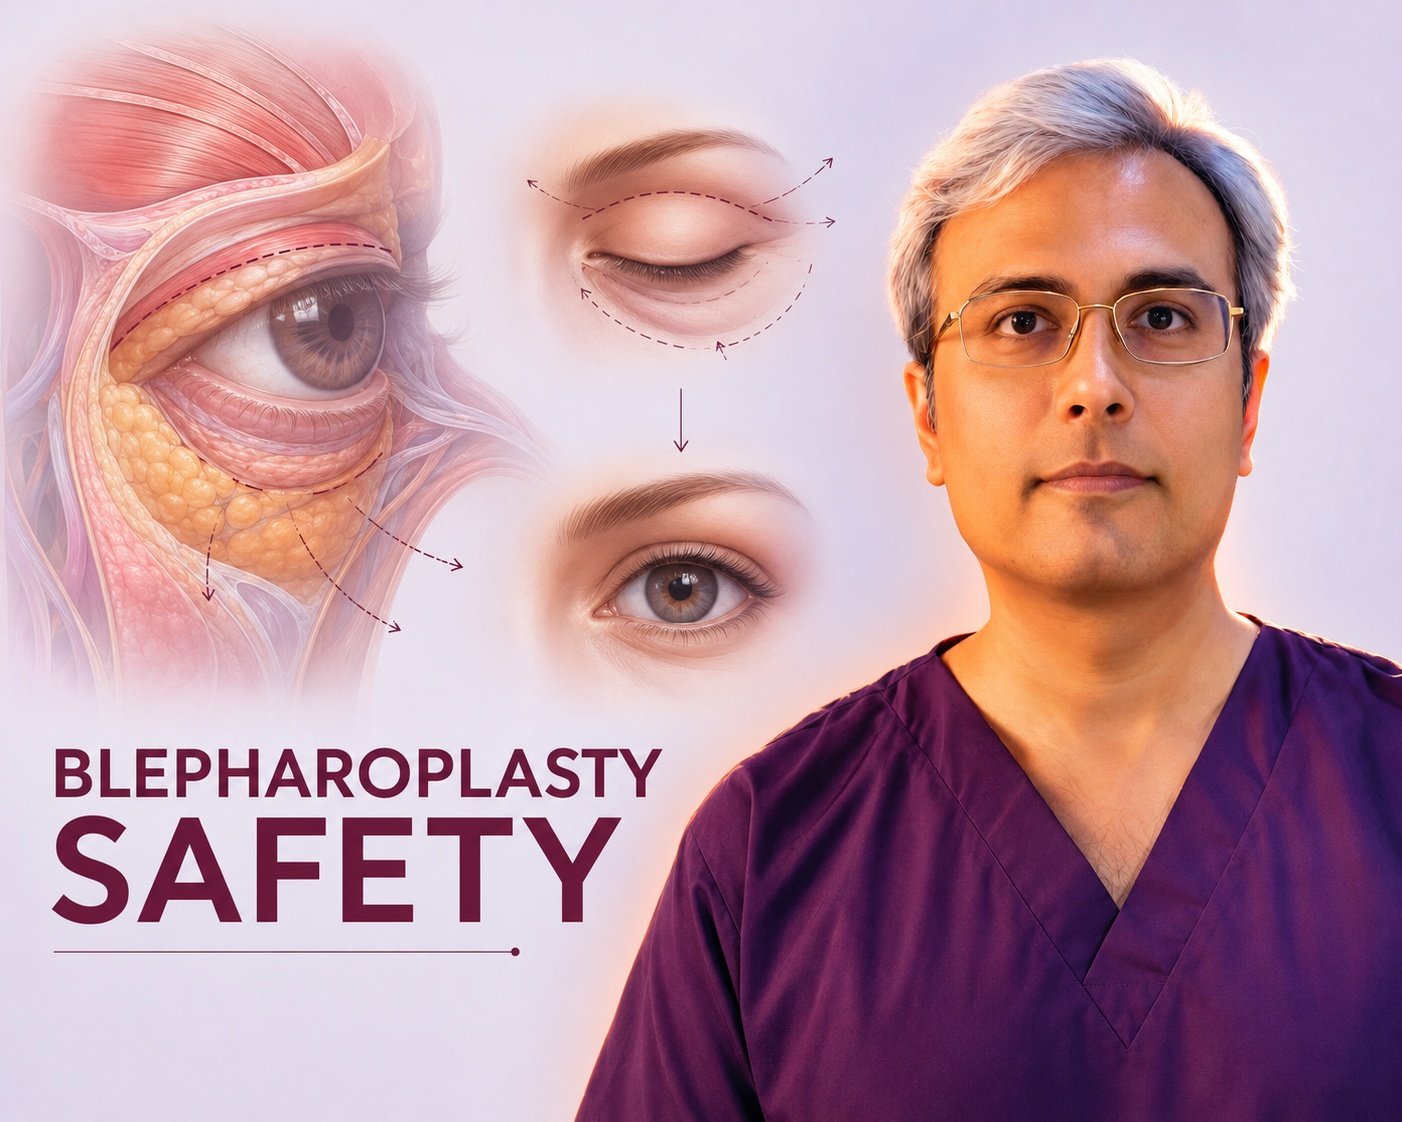
Risks and Complications
No honest article about expectations can omit these. The overall complication rate is low in appropriately selected patients, but the risks are real and should be discussed before, not after, surgery.
Common and usually temporary: bruising, swelling, tightness, blurred vision from ointment, watering, and light sensitivity in the first week.
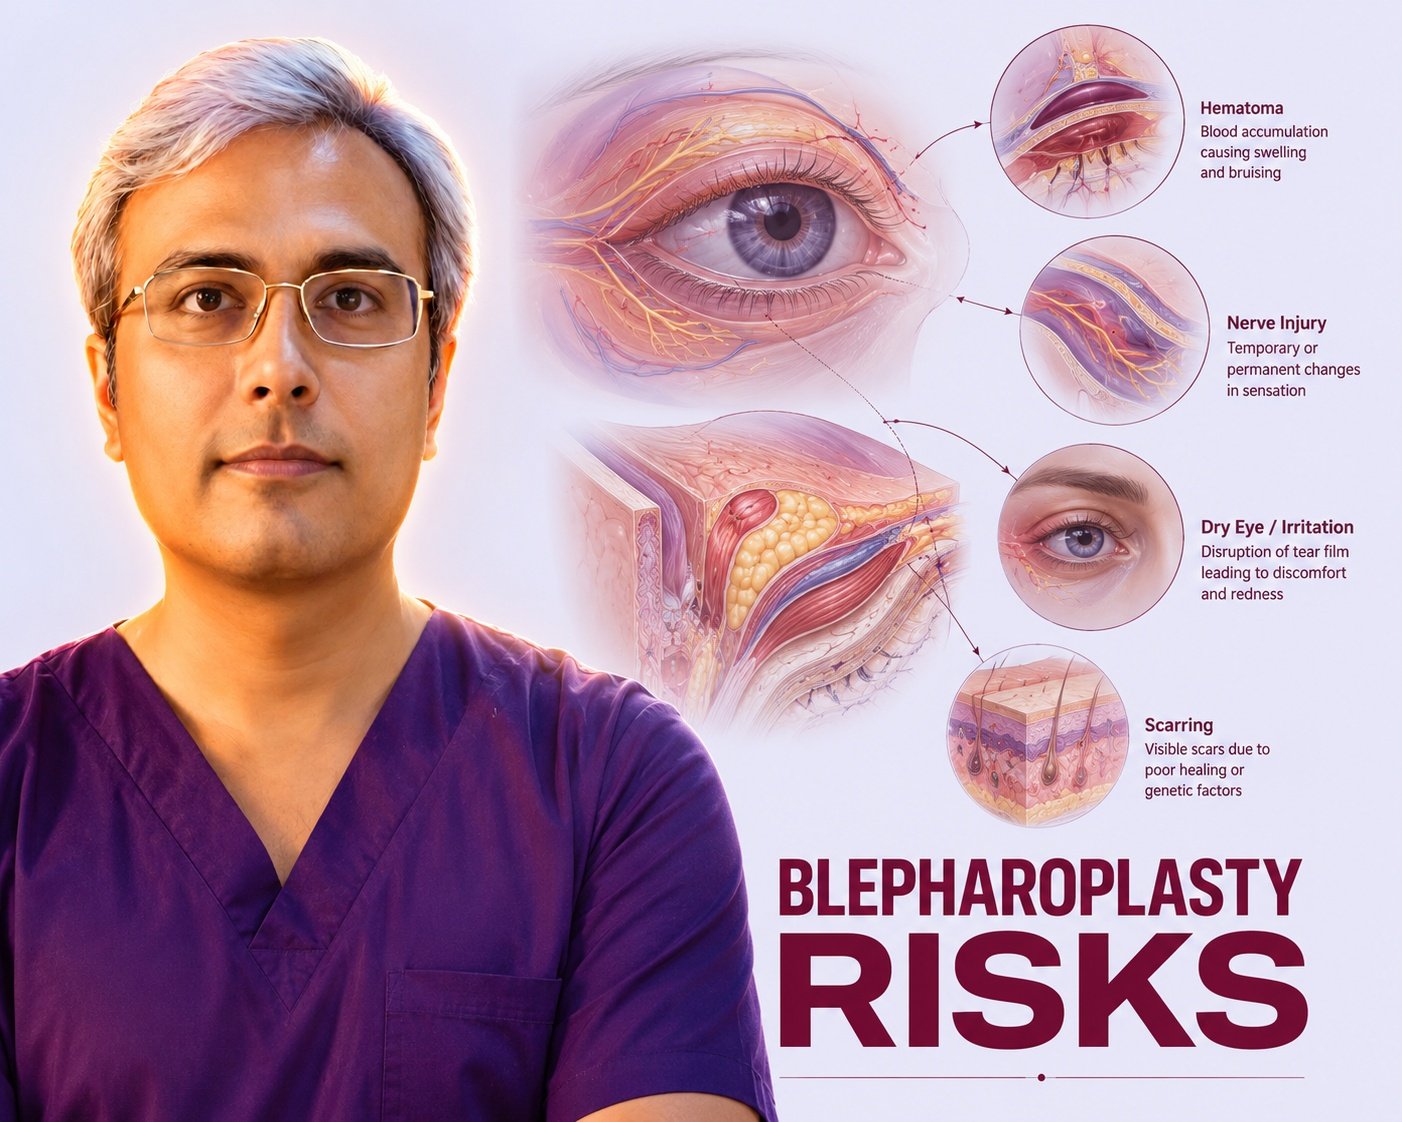
Dry eye. The most common troublesome complication. Surgery can precipitate dry eye symptoms or worsen existing ones, sometimes for several months. Pre-existing dry eye must be identified and treated before any decision to operate.
Lagophthalmos. Incomplete eyelid closure, usually mild and temporary, occasionally persistent if too much skin has been removed.
Lower lid malposition. Rounding of the lid corner, scleral show, retraction, or frank ectropion. More likely in patients with poor lower lid tone or a negative-vector midface, and one of the main reasons lower blepharoplasty demands careful assessment and often a canthal support procedure.
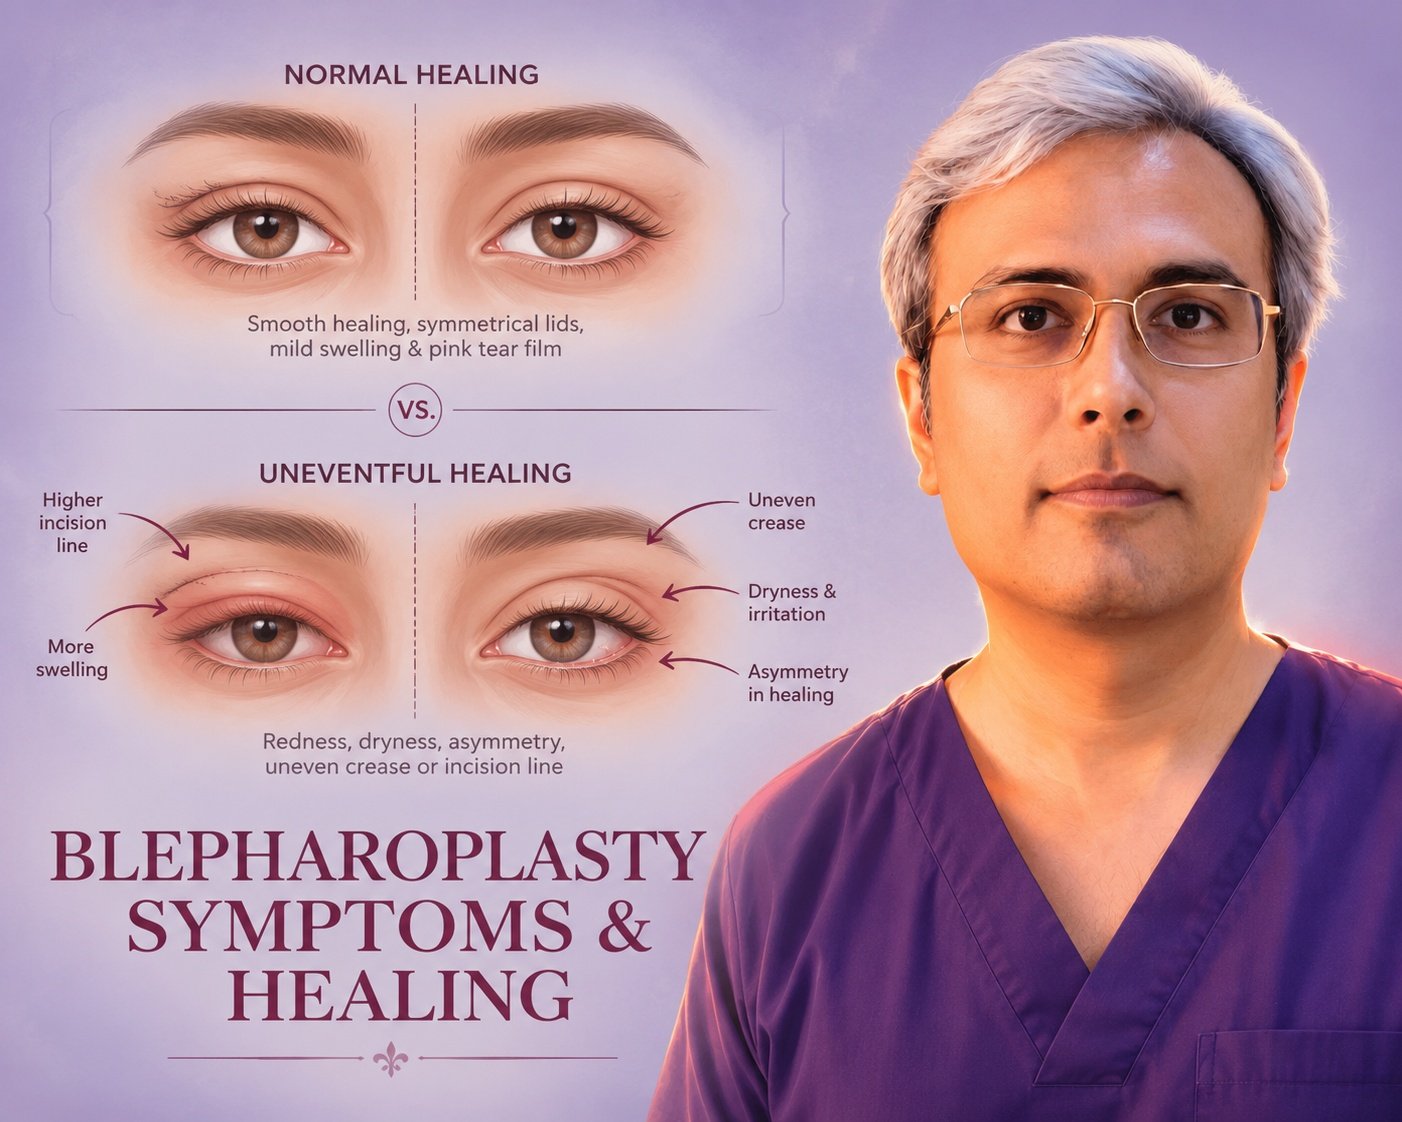
Asymmetry. The two sides start asymmetric and heal at different rates. Minor asymmetry is common; a revision rate in the region of a few percent is realistic across most published series.
Scarring. Incisions are hidden in the crease and beneath the lash line and usually mature to near-invisibility, but hypertrophic or slow-fading scars occur, and pale scars can be more conspicuous on some skin types than others. Milia along the incision are common and easily treated.
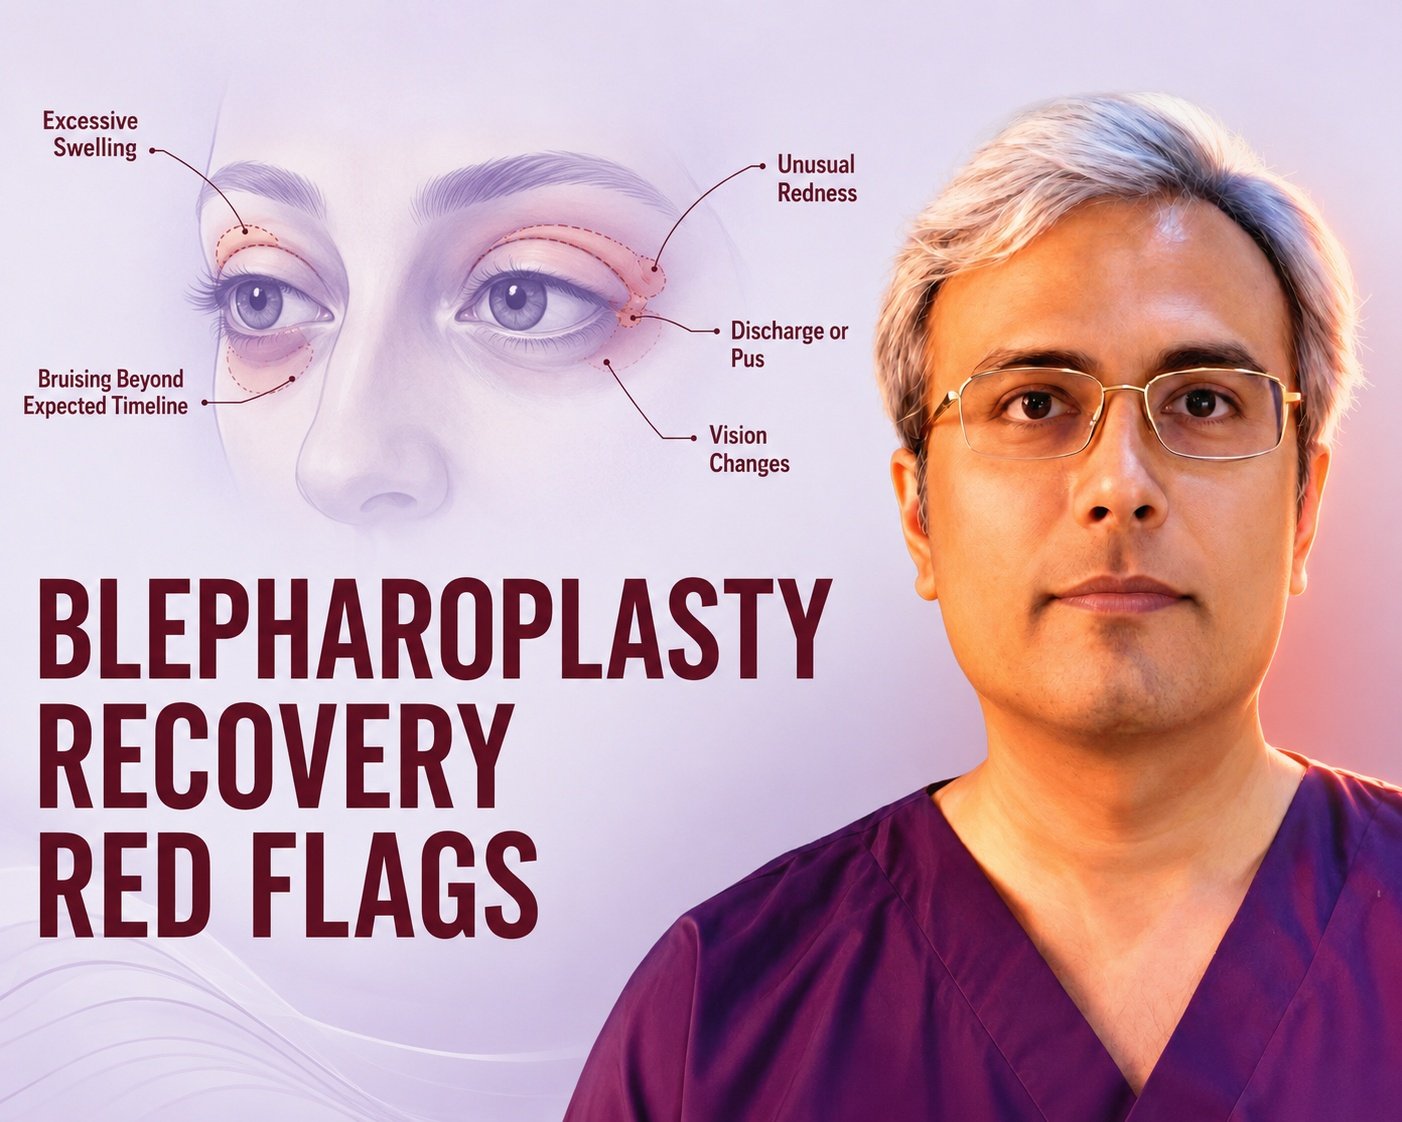
Retrobulbar haemorrhage. Very rare — roughly on the order of one in several thousand cases — but the one true emergency, because it can threaten sight. It is why we screen for anticoagulants, uncontrolled hypertension and bleeding tendency, and why sudden severe pain with vision change after surgery requires immediate contact, not a wait-and-see.
Who Is a Suitable Candidate
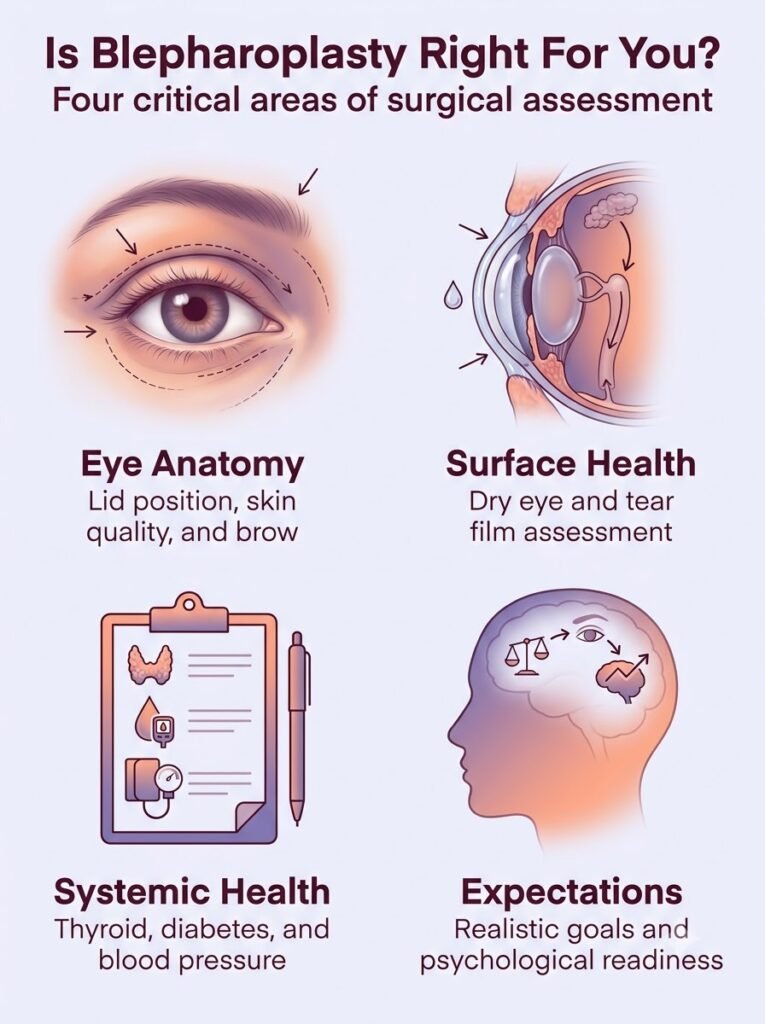
Suitability is a set of specific findings, not a formality. At consultation, the following are assessed directly.
Anatomy that matches the complaint. Lid margin position and levator function to distinguish ptosis from dermatochalasis. Brow position. Skin quality and quantity. Lower lid tone by snap-back and distraction testing. Orbital rim position and midface vector.
Ocular surface health. Symptoms and signs of dry eye, tear film assessment, any history of LASIK, blepharitis, or contact lens intolerance.
Systemic factors. Thyroid eye disease must be excluded or stabilised — operating on active thyroid orbitopathy is a well-recognised route to a poor result. Glaucoma, uncontrolled diabetes, uncontrolled hypertension, bleeding disorders, and anticoagulant or antiplatelet therapy all change the plan. Smoking impairs healing and should stop several weeks before and after.
Expectations. A patient who arrives with a photograph of a different face, who is focused on a barely perceptible asymmetry, or who shows features of body dysmorphic disorder is not helped by an operation. Declining to operate is sometimes the correct clinical decision.
Recovery: A Realistic Timeline
The operation is usually performed under local anaesthesia with sedation as a day-care procedure, and takes roughly 45 to 90 minutes depending on whether one or both lids are addressed.
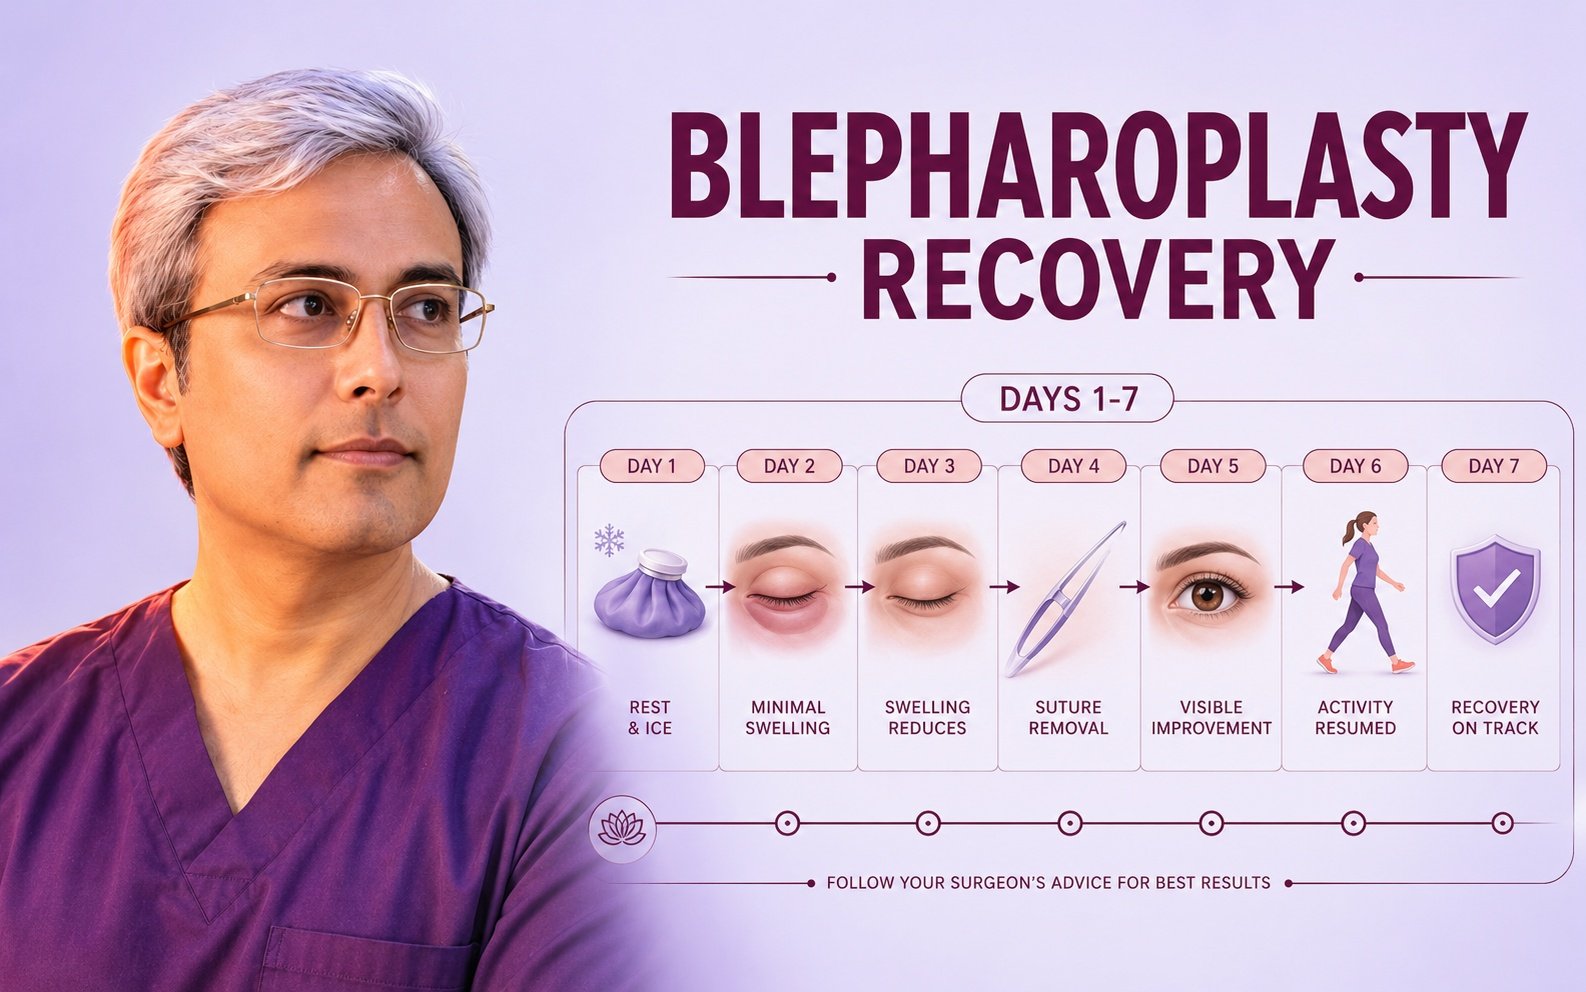
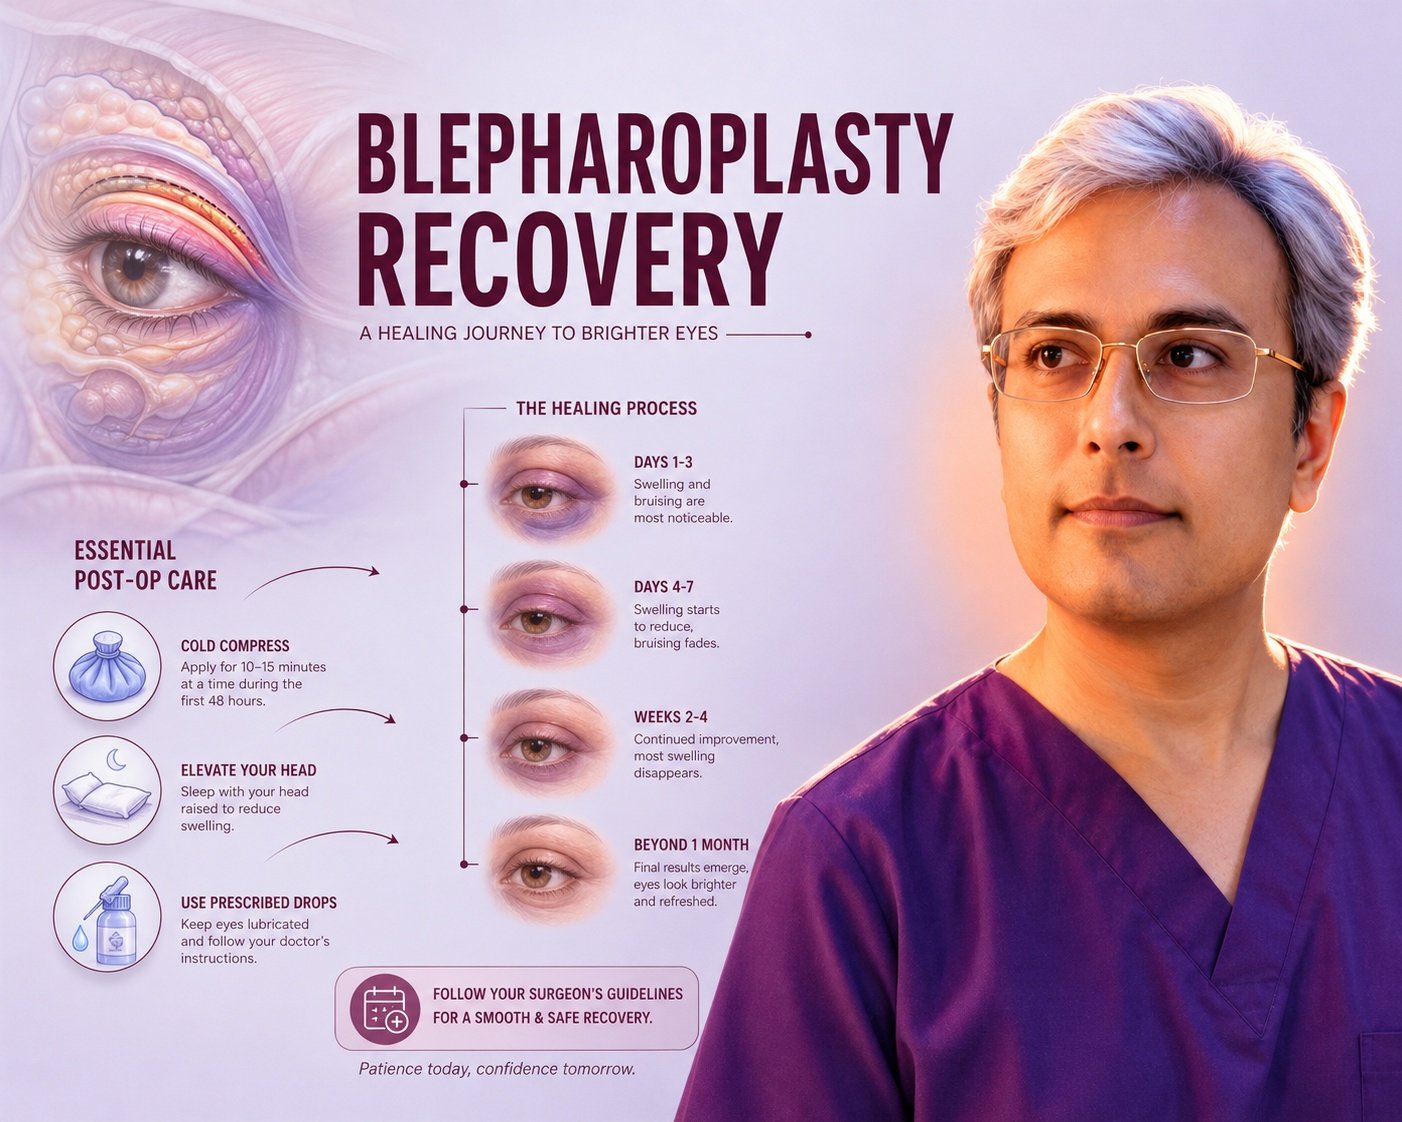
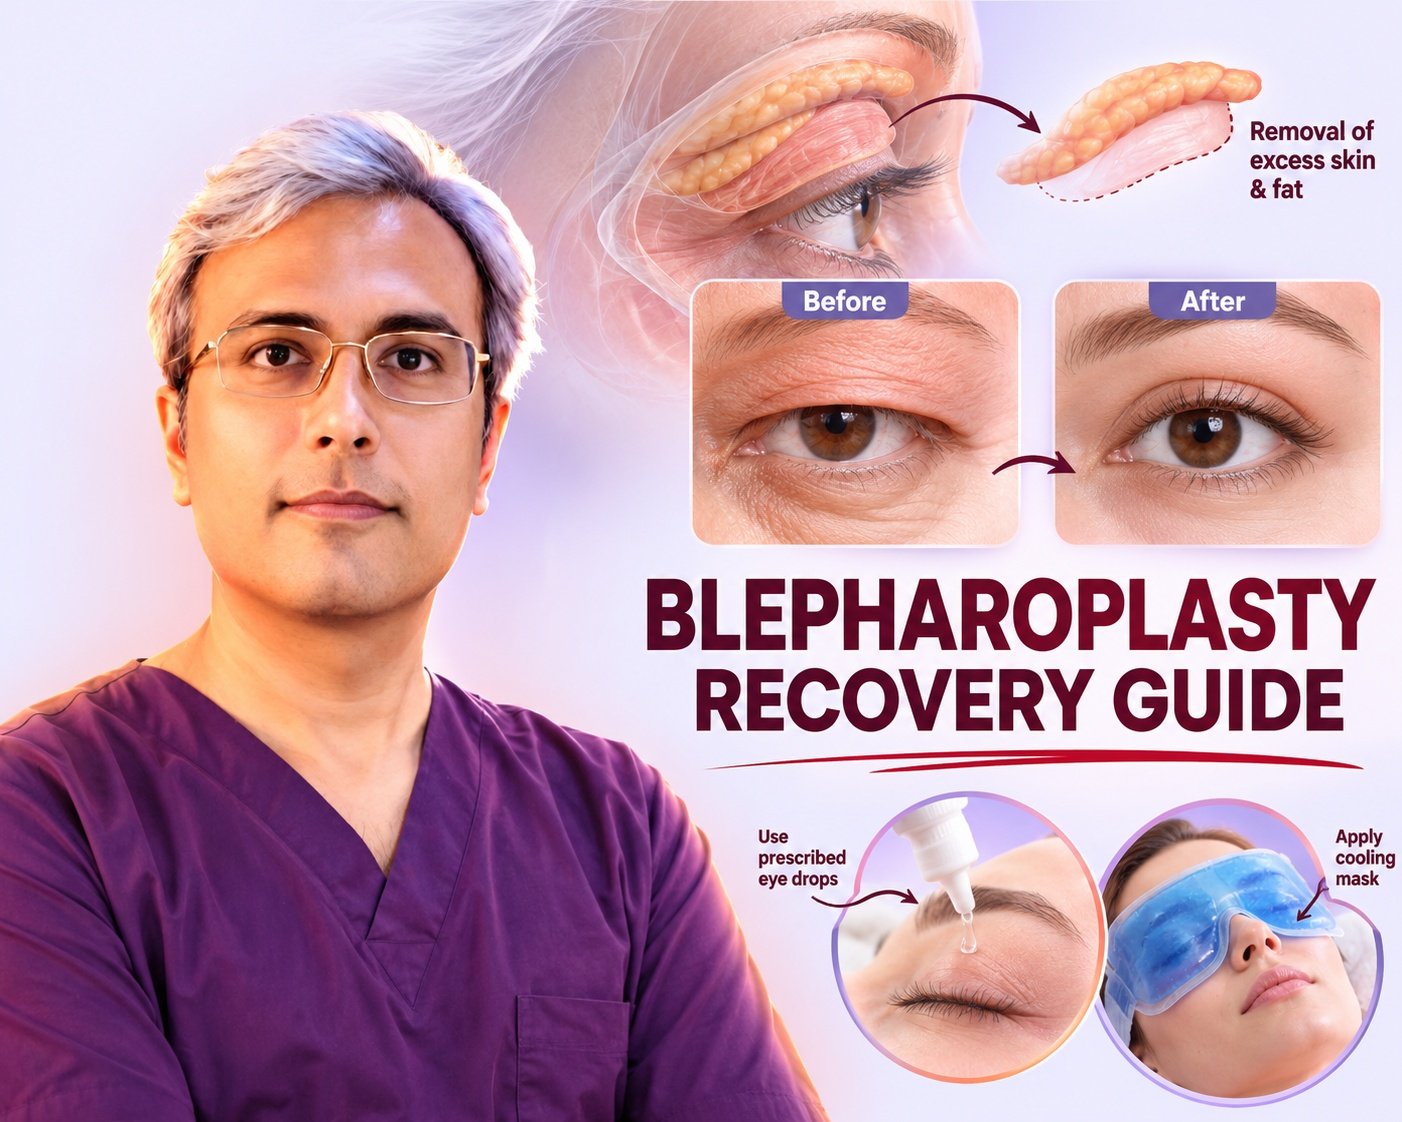
Days 1–3. Peak swelling and bruising. Cold compresses, head elevated, no bending or lifting. Vision may be blurred from ointment. Discomfort is generally mild and controlled with simple analgesia.
Days 5–7. Sutures removed for upper lids. Swelling is visibly settling. Bruising begins to change colour.
Days 7–10. Most patients are comfortable returning to desk work. Bruising can usually be camouflaged with makeup from around day 10, once incisions are sealed.
Weeks 2–4. Residual bruising resolves. The lids look presentable but not final — a degree of firmness, tightness and mild asymmetry is normal and expected at this stage.
Months 2–3. Upper lid results approach their final form. The crease settles, and residual swelling that only you can see continues to resolve.
Months 3–6. Lower lid results settle, which takes longer than most patients expect. Persistent lumpiness or unevenness at three months is usually swelling, not the final result.
Up to 12 months. Scar maturation completes. Incision lines soften and fade progressively across the first year.
Practical restrictions: no contact lenses for around two weeks, no eye makeup until incisions are fully healed, no strenuous exercise or swimming for three to four weeks, and rigorous sun protection over the scars for several months.
How Long Results Last
Honest answers differ for the two lids.
Upper blepharoplasty typically holds well for somewhere in the region of 7 to 10 years or longer, but this is not permanent. Skin laxity recurs with continued ageing, sun exposure and brow descent. A proportion of patients seek a second procedure eventually; many never do.
Lower blepharoplasty results tend to be more durable where fat has been repositioned, because the herniated fat is unlikely to recur in the same way. Skin quality and lower lid tone, however, continue to age normally.
What no eyelid operation does is stop the clock. It moves you to an earlier point on the same curve. Sun protection, not smoking, and good skincare influence how quickly you travel along it — considerably more than any surgical detail does.
Frequently Asked Questions
How do I know whether I have ptosis or just excess skin?
To determine if you have ptosis (muscle weakness) or dermatochalasis (excess skin), a clinical evaluation by a board-certified surgeon is required. Ptosis means the eyelid margin itself droops over the pupil, while excess skin hangs over a normally positioned eyelid. Dr. Vishal Purohit evaluates these specific anatomical differences at his Jaipur clinic to ensure you receive the correct surgical correction, whether that is ptosis repair or an upper blepharoplasty.
Will blepharoplasty surgery get rid of my dark circles?
Blepharoplasty does not cure dark circles caused by skin pigmentation, but it eliminates the dark shadowing caused by bulging under-eye fat bags. During lower eyelid surgery in Jaipur, Dr. Vishal Purohit removes or repositions these fat pads to create a smooth contour. If your dark circles are caused by shadows from prominent bags, blepharoplasty will make you look significantly brighter and more rested.
When can I return to work after blepharoplasty?
Patients typically return to office work 7 to 10 days after blepharoplasty with Dr. Vishal Purohit in Jaipur. You can resume reading and computer work within 2 to 3 days, but visible swelling and bruising are usually present for the first week. Strenuous exercise and heavy lifting must be avoided for at least three weeks to prevent spikes in blood pressure and minimize swelling.
Will the blepharoplasty scars be visible?
Blepharoplasty scars are exceptionally well-hidden and become virtually invisible once fully healed. For upper eyelids, Dr. Vishal Purohit places the incision exactly within the natural crease. For lower eyelids, incisions are made just below the lash line or inside the lid itself (transconjunctival approach). Because eyelid skin is the thinnest on the body, it heals faster and more seamlessly than anywhere else.
Can upper and lower lids be done at the same time?
Yes, upper and lower blepharoplasty can be safely performed at the same time to achieve complete eye rejuvenation. Dr. Vishal Purohit frequently combines these surgeries at his Jaipur clinic so patients only have to go through one 7-to-10 day recovery period. This combined approach ensures a balanced, natural-looking result across the entire eye area without needing multiple surgical sessions.
Is cosmetic eyelid surgery painful?
Cosmetic eyelid surgery is not highly painful; most patients describe the recovery as mildly uncomfortable with a feeling of tightness. The procedure is performed under anesthesia, so you feel nothing during surgery. Afterward, Dr. Vishal Purohit recommends cold compresses, lubricating eye drops, and mild over-the-counter pain medication, which easily manage the temporary soreness and dry eyes experienced in the first few days.
At what age should blepharoplasty be done?
There is no specific right age for blepharoplasty; the procedure is customized based on your anatomy rather than your birth year. While most of Dr. Vishal Purohit’s cosmetic patients in Jaipur are over 35 addressing age-related skin laxity and drooping, younger patients frequently undergo the surgery to remove genetic, heavy under-eye bags. The best time for surgery is when functional visual obstruction or cosmetic concerns arise.
Reviewed by Dr. Vishal Purohit, plastic and cosmetic surgeon, Kalpana Aesthetics, Jaipur. Last updated 26 July 2026. This article is general information and is not a substitute for individual medical assessment.
To discuss whether blepharoplasty is appropriate for you — including the possibility that it is not — contact Kalpana Aesthetics, Jaipur, at +91-7718183535.



 English
 Hindi