
In short
- Most flap wounds heal on time with a simple drain. Only a small share need extra help.
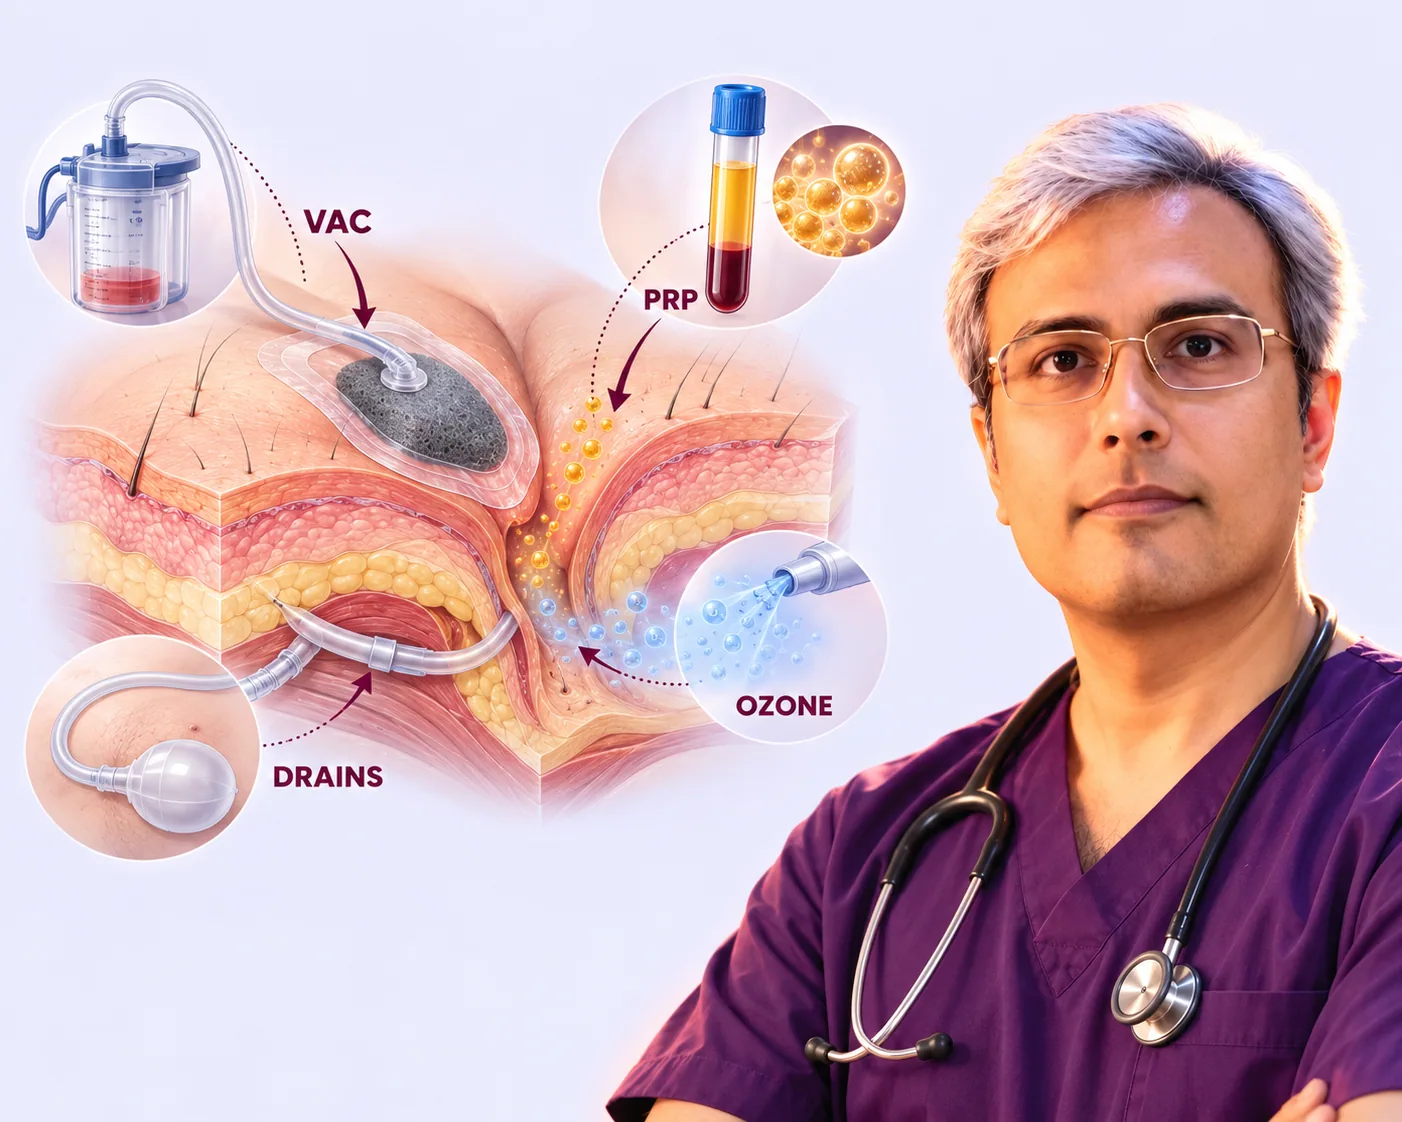
- Drains stop fluid build-up; VAC dressings restart open or stalled wounds; PRP, oxygen, and ozone only support healing.
- No adjunct cures the sinus itself — the tract and pits still need flap surgery.
Who needs extra wound help
Most Limberg and Karydakis flap wounds heal in a straight line: drain out in days, stitches settle in weeks. Extra help enters only when healing stalls.
Candidates include:
- Large dead space — wide flaps where fluid can pool under the skin join
- Revision wounds — scarred tissue after failed earlier surgery
- Open or separated edges — wounds healing from the base instead of a closed line
- Slow hosts — diabetes, smoking, or weak immunity that delay repair
A wound that shrinks week by week needs patience, not gadgets. A wound that stalls for 2 to 3 weeks despite clean dressings needs re-mapping first — for retained hair, a hidden pocket, or edge tension — and only then an adjunct.
Red flags that push review earlier include rising pain after steady improvement, new foul odour, or an edge that opens after looking closed. These signs point to trapped fluid or a missed side tract, and both are fixed by examination — not by adding another dressing type on top.
Drains under the flap: what they do
A closed-suction drain (a soft tube to a squeezed bulb) is routine under flaps. It keeps the lifted skin pressed to its bed so serum cannot collect and lift it. Without it, fluid pockets can seed infection and split the wound.
Home drain care in four steps:
- Keep the bulb flat. Press it down after each emptying so suction holds.
- Empty and measure. Pour fluid into a cup once or twice daily and write down the amount.
- Keep the exit clean. A simple cover at the small skin exit; watch for spreading redness.
- Track the trend. Output should fall and thin over days; the drain comes out once 24-hour fluid is low, often below about 10 to 20 mL.
Early fluid looks red and thin, then turns straw-coloured as healing sets in. A sudden return to bright red, or thick cloudy fluid with odour, breaks the pattern and deserves a same-day call. The removal visit is short: the tube slides out in seconds, a small cover goes on, and the exit usually seals within a day or two.
Call the clinic at once for these
- Sudden bright-red blood filling the bulb
- Abruptly stopped output with new swelling under the flap (possible blockage)
- Fever, foul cloudy fluid, or fast-spreading redness
VAC dressings for open or stalled wounds
VAC (vacuum-assisted closure, also called negative pressure wound therapy or NPWT) suits open wounds with a clean base. A sealed foam dressing applies gentle suction through a small pump.
It helps in three ways:
- Pulls fluid out — infected fluid and swelling drain continuously
- Shrinks edge swelling — less puffiness lets edges draw inward
- Coaxes new tissue — the foam’s light pull builds grainy red base tissue over 1 to 3 weeks
Foam is changed every few days in clinic. VAC is not for every wound: closed flap lines, dry scabs, and bleeding wounds stay on simple dressings. For the right open wound it can shorten the path to closure or to a smaller second procedure — which is why it sits in every non-healing wound repair plan.
A typical VAC course runs 1 to 3 weeks, with the surgeon judging the base at each foam change. A beefy red base that bleeds lightly on touch signals readiness — for natural edge closure or a smaller repair. A pale, flat, or smelly base signals a deeper problem, and the plan pivots back to re-mapping rather than more suction weeks.
PRP, oxygen, and ozone: what to expect
These regenerative adjuncts appear in wound literature and are sometimes asked about. Each has a narrow, honest role.
- PRP (platelet-rich plasma) — the patient’s own concentrated platelets injected or dressed onto a sluggish wound base to nudge repair. Evidence in pilonidal wounds is thin; it is a helper, not a cure.
- Hyperbaric oxygen — breathing pure oxygen in a pressure chamber to raise tissue oxygen in stalled wounds. Described in published series for problem wounds, used only beside proper surgery.
- Ozonated dressings — oxygen-rich topical care for surface cleansing. Supportive hygiene, not tract treatment.
None of these removes the sinus lining or the pits. Any plan that offers an adjunct instead of removing the disease leaves the cause in place. The week-by-week recovery timeline after flap surgery shows where adjuncts fit — and where simple dressings suffice.
Honest counselling also covers cost and time. Chamber sessions and repeat PRP sittings add visits and expense without changing the core operation, so they are reserved for wounds that truly stall. A surgeon who offers an adjunct should name the stop point: what improvement is expected, by which week, and what happens if it never comes.
What Dr. Vishal Purohit does in Jaipur
Dr. Vishal Purohit, an M.Ch plastic surgeon, places a closed-suction drain in every Limberg and Karydakis flap in Jaipur and removes it on measured output, not guesswork. Reviews at weeks 1, 3, and 6 catch stalled healing early.
For open or breakdown wounds the clinic steps up in order: re-mapping for retained hair or pockets, VAC dressings for suitable open bases, and referral discussion for chamber-based oxygen only where truly indicated. PRP and ozone are presented as published-literature context, not clinic cures. The clinic performs only Limberg and Karydakis flap surgery plus abscess drainage — no laser, phenol, or endoscopic shortcuts.
Smokers are asked to stop before and after surgery, and diabetic patients get tighter sugar targets during healing weeks, because blood supply decides more than any device. Dressing burden is kept realistic: most families manage home drain and gauze care after one supervised teaching session, with the clinic a phone call away for anything off-pattern.
Every wound patient leaves with written drain and dressing notes plus a direct contact path for warning signs. This is educational information, not medical advice.